Pleurectomy in primary pneumothorax: is extensive pleurectomy necessary?
Related Experiment Video
Updated: Oct 10, 2026

Local Anesthetic Thoracoscopy for Undiagnosed Pleural Effusion
Published on: November 10, 2023
F Leo1, U Pastorino, P Goldstraw
1Department of Thoracic Surgery, European Institute of Oncology, Milano, Italy. fleo@ieo.it

Background:
The aim of the study was to evaluate the results of parietal pleurectomy in patients with primary spontaneous pneumothorax comparing extensive pleurectomy performed by thoracotomy versus more limited pleurectomy performed by VATS.
Methods:
Records of the patients operated on for primary pneumothorax at Royal Brompton Hospital from January 1994 to April 1997 were retrospectively reviewed. A follow-up questionnaire was sent to patients asking about further pneumothorax and the presence of long-term chest problems on the operated side. A statistical uni- and multivariate analysis was performed searching predictors for postoperative complications, recurrence and chronic chest problems.
Results:
Thirty-six patients underwent extensive pleurectomy through a limited postero-lateral thoracotomy (40%, group A), 54 patients had a limited pleurectomy (60%, group B), 50 by VATS and 4 by axillary thoracotomy. Overall, 11 patients had postoperative complications (12.2%). In group A, 4 patients (11.1%) had complications (2 reoperation, 2 air leak >7 days). In group B, 7 patients (12.9%) had complications (1 reoperation, air leak >7 days, 1 wound infection). Two patients experienced recurrent ipsilateral pneumothorax after surgery, both belonging to group B (overall recurrence rate 2.5%, group B 4.1%). Thirteen patients in both groups (respectively 41.9% in group A and 27% in group B) admitted chest problems on the operated side. From statistical analysis, "indication" resulted a predictor of complications (p=0.03) and "thoracotomy" a predictor of long-term chest problems (p=0.03).
Conclusions:
Many theoretical advantages of limited VATS pleurectomy have still to be confirmed and it is reasonable to use it in uncomplicated primary pneumothorax. The superb exposure obtained with thoracotomy and the superiority of extensive pleurectomy in terms of recurrence indicate this approach in case of complicated pneumothorax or when long-term security is of paramount importance.
More Related Videos
 11:17
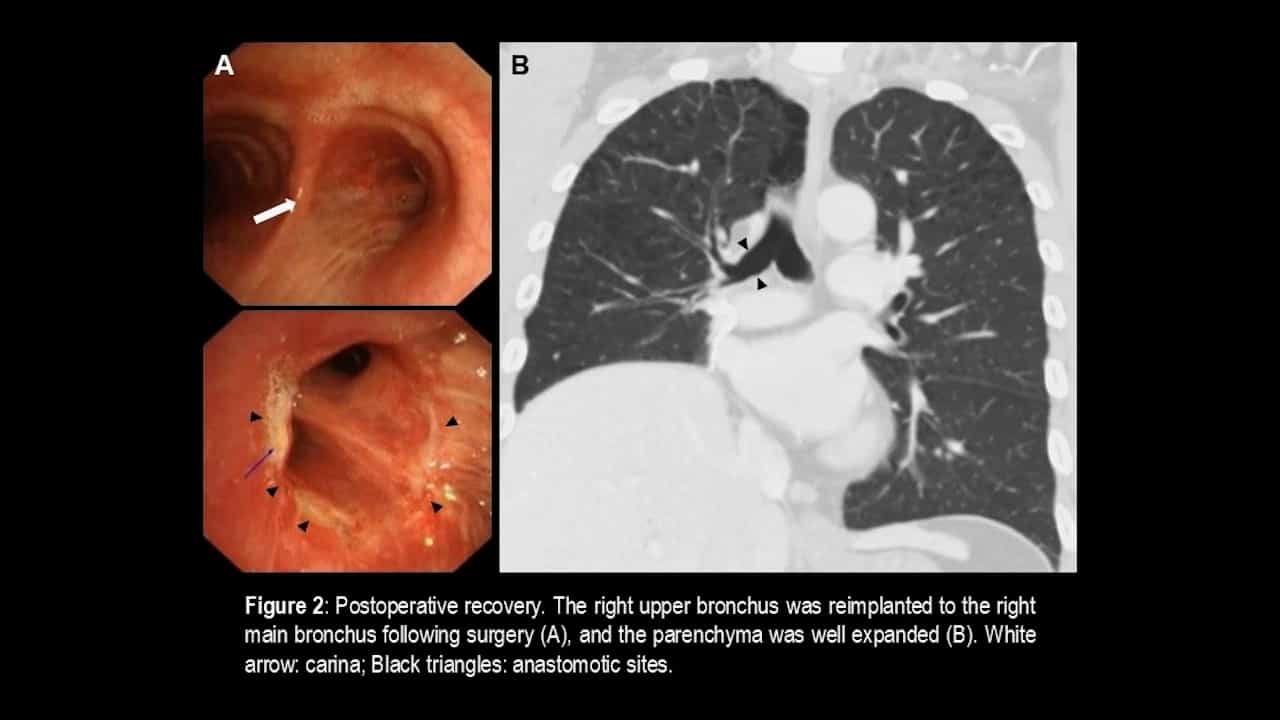
Thoracoscopic Extended Right Middle Plus Lower Sleeve Lobectomy for Non-Small-Cell Lung Cancer
Published on: February 27, 2026
 05:50
International Expert Consensus and Recommendations for Neonatal Pneumothorax Ultrasound Diagnosis and Ultrasound-guided Thoracentesis Procedure
Published on: March 12, 2020
Related Concept Videos
 01:27
Pneumothorax-II
Clinical Manifestations:
 01:13
Pleura of the Lungs
 01:08
Pneumothorax II: Pathophysiology
 01:26
Pneumothorax-I
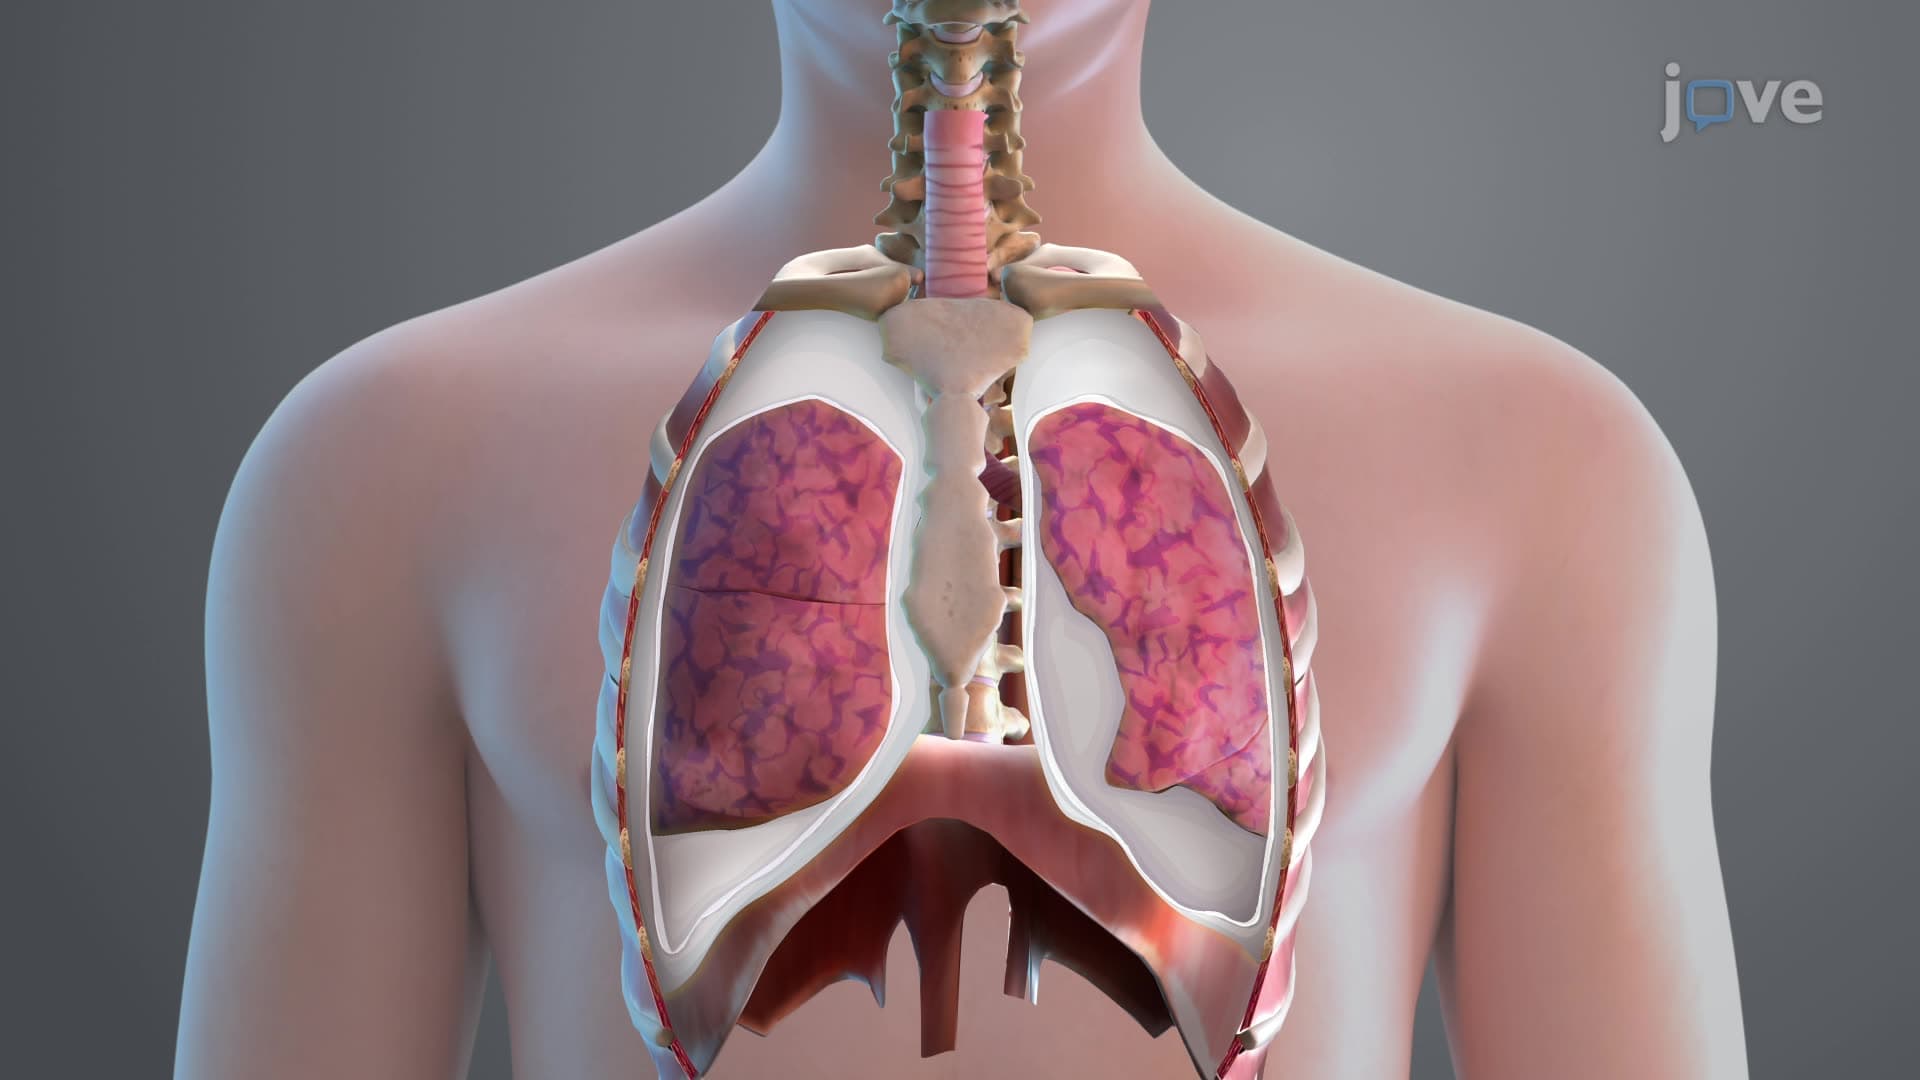
Pneumothorax can be even further classified as spontaneous, traumatic, and tension pneumothorax.
 01:28
Pleural Effusion II: Symptoms and Management
A pleural effusion is the abnormal collection of fluid between the parietal and visceral pleura layers of tissue that form the lining of the lungs and chest cavity. It can occur independently or due to surrounding parenchymal diseases, such as infection, malignancy, or inflammatory conditions.
Clinical Manifestations:
 01:26
Flail Chest-II
Assessment:
1. Clinical Evaluation:
History: