Related Experiment Video
Updated: Oct 10, 2026

Quantitating Iron Transport Across the Mouse Placenta In Vivo Using Nonradioactive Iron Isotopes
Published on: May 10, 2022
Urinary excretion of lead during pregnancy and postpartum
B L Gulson1, K J Mizon, J M Palmer
1Graduate School of the Environment, Macquarie University, Sydney, NSW, Australia. bgulson@gse.mq.edu.au

Abstract:
We have compared lead isotopic ratios and lead concentrations in 53 spot urine and 59 24-h urine samples from 13 subjects covering the interval from pre-pregnancy through 180 days postpartum to estimate the amount of lead excreted in urine and renal clearance relative to blood. The total amount of lead excreted in 24-h urine samples ranges from 0.8 to 5.9 microg Pb with an arithmetic mean of 2.2+/-1.1 microg (geometric mean 1.90 microg). This compares with amounts of 0.9-10 microg of extra lead per day estimated to be released into blood from the skeleton during pregnancy and postpartum. There were no differences in excretion rates during the trimesters of pregnancy and between pregnancy and postpartum time periods. The renal clearance relative to blood ranged from 0.8 to 10 g/h (arithmetic mean 3.2+/-1.9; geometric mean 2.7). Renal clearance relative to blood was somewhat higher in trimesters 2 and 3 compared with postpartum 150-180 days (P = 0.004, 0.006, respectively). Reassessment of earlier published blood and dietary data for Australian pregnant controls indicates there is no increased gastrointestinal absorption of lead during pregnancy and postpartum. This differs from calcium, which shows increased absorption during late pregnancy. In light of the inconvenience of sampling and potential contamination at the low levels of lead found in most of these subjects, we do not consider the 24 h urines to provide sufficient useful information.


Related Concept Videos
 01:26
Enhanced Elimination of Poison
Antidotes serve a crucial role in counteracting the effects of poison by inhibiting enzymes responsible for producing harmful drug metabolites. In some cases, these toxic metabolites can be neutralized by endogenous cosubstrates, which are maintained at specific concentrations to prevent interaction with cellular macromolecules and subsequent cell death.
Renal excretion is the...
 01:33
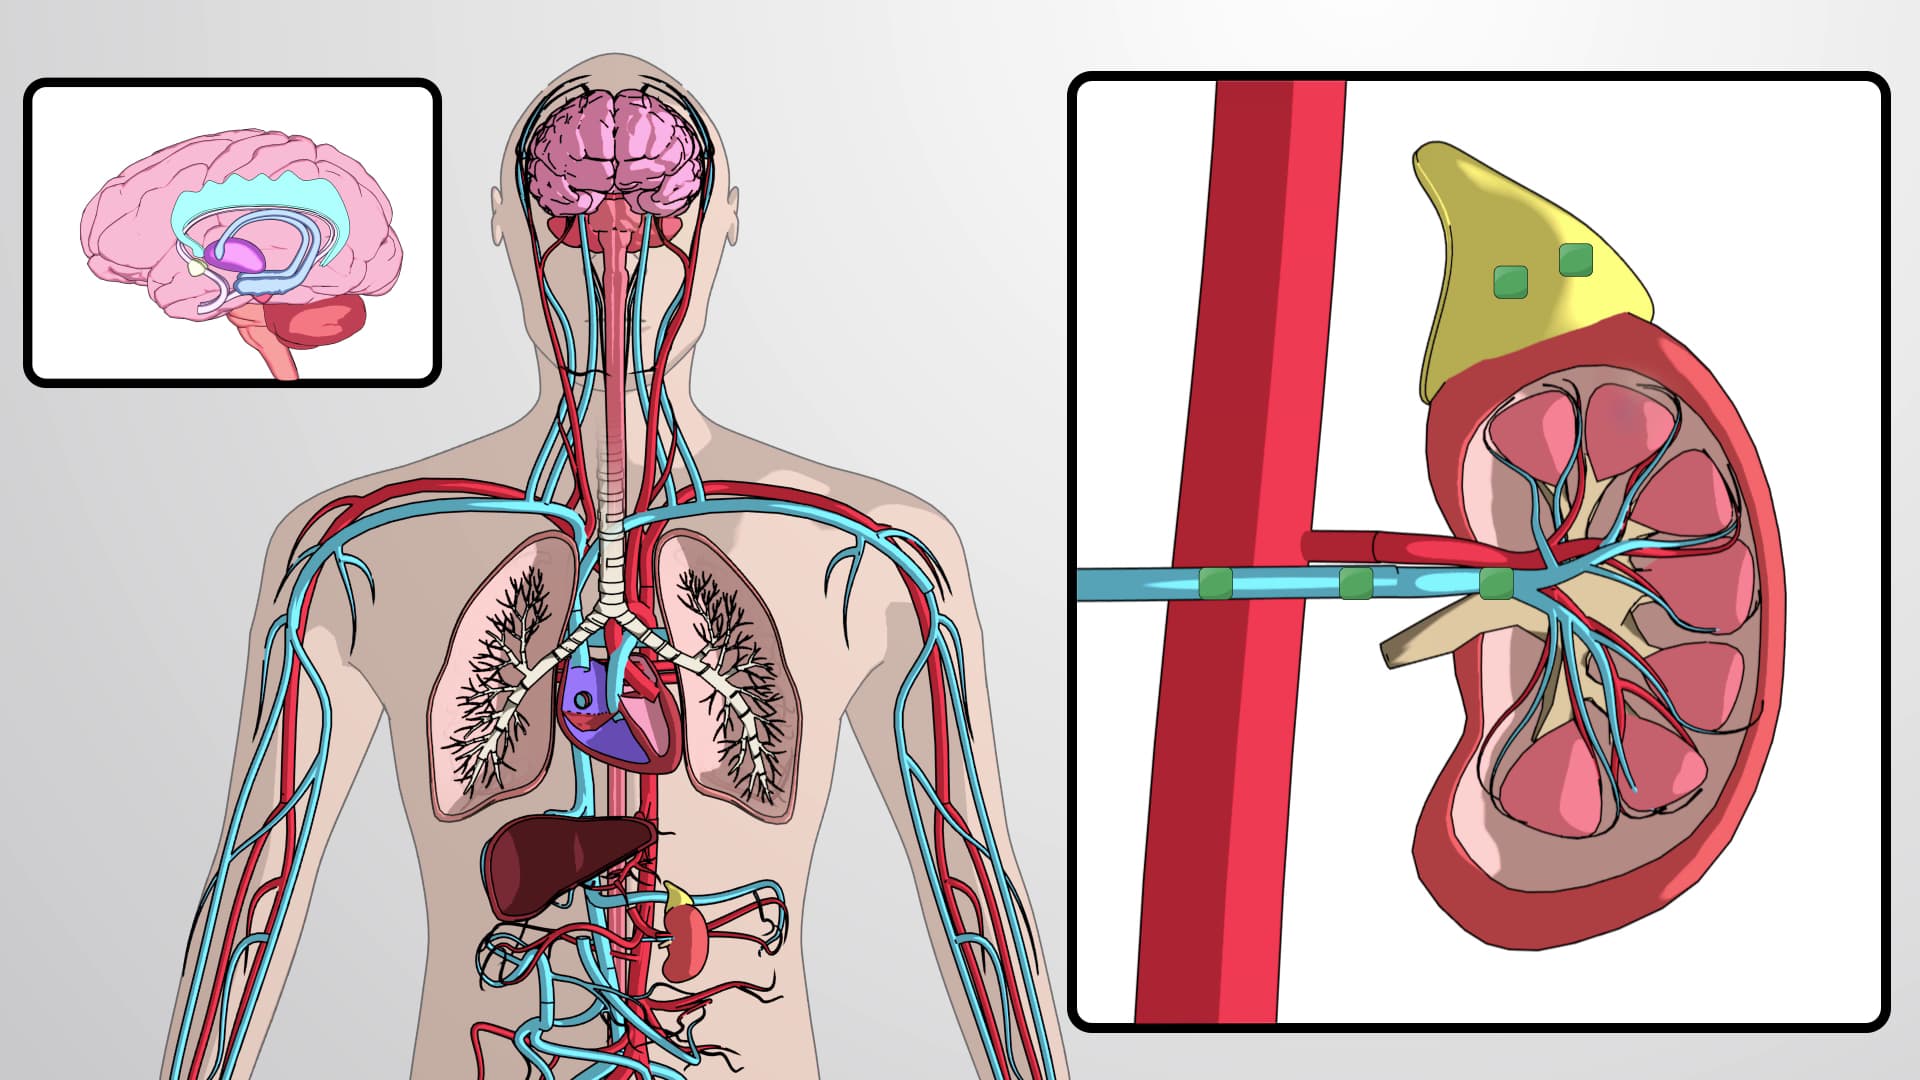
Hormonal Regulation
 01:26
Pharmacokinetics in Pediatric Patients: Drug Excretion
 01:07
Teratogenicity
 01:22
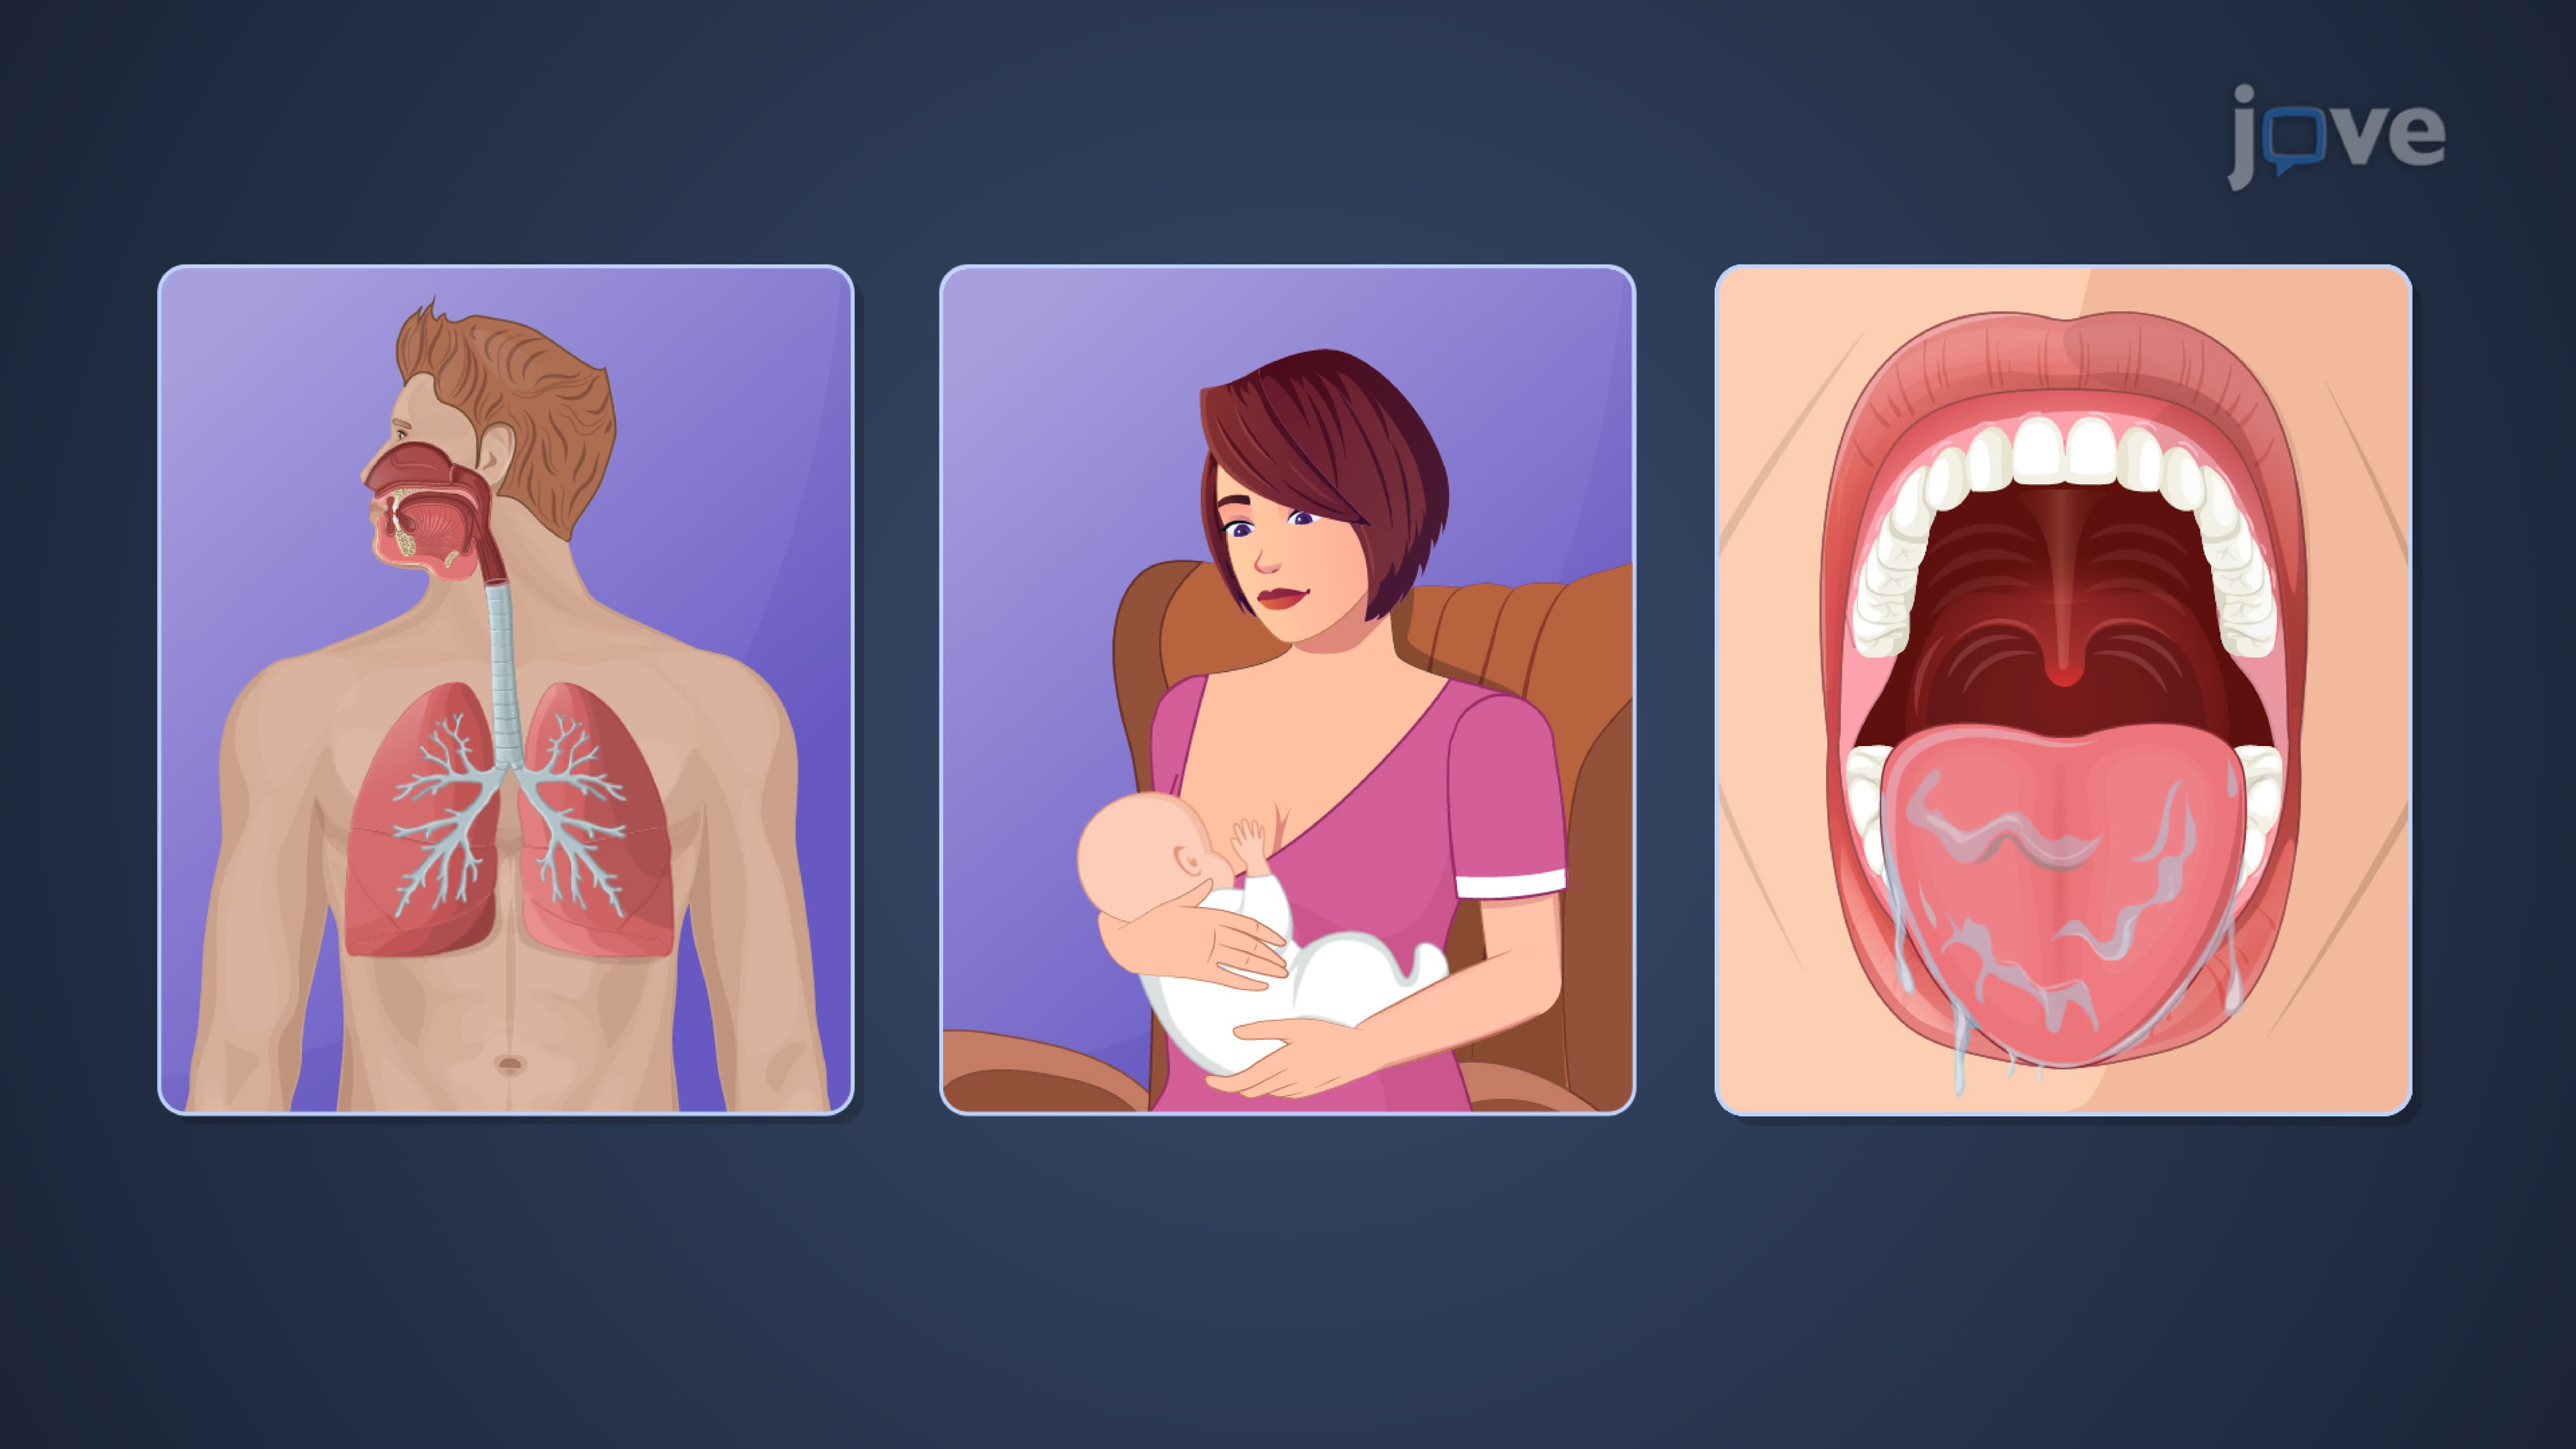
Drug Excretion: Pulmonary and Glandular Routes
Drugs can also be excreted in breast milk, which is crucial for breastfeeding infants. The process...
 01:22
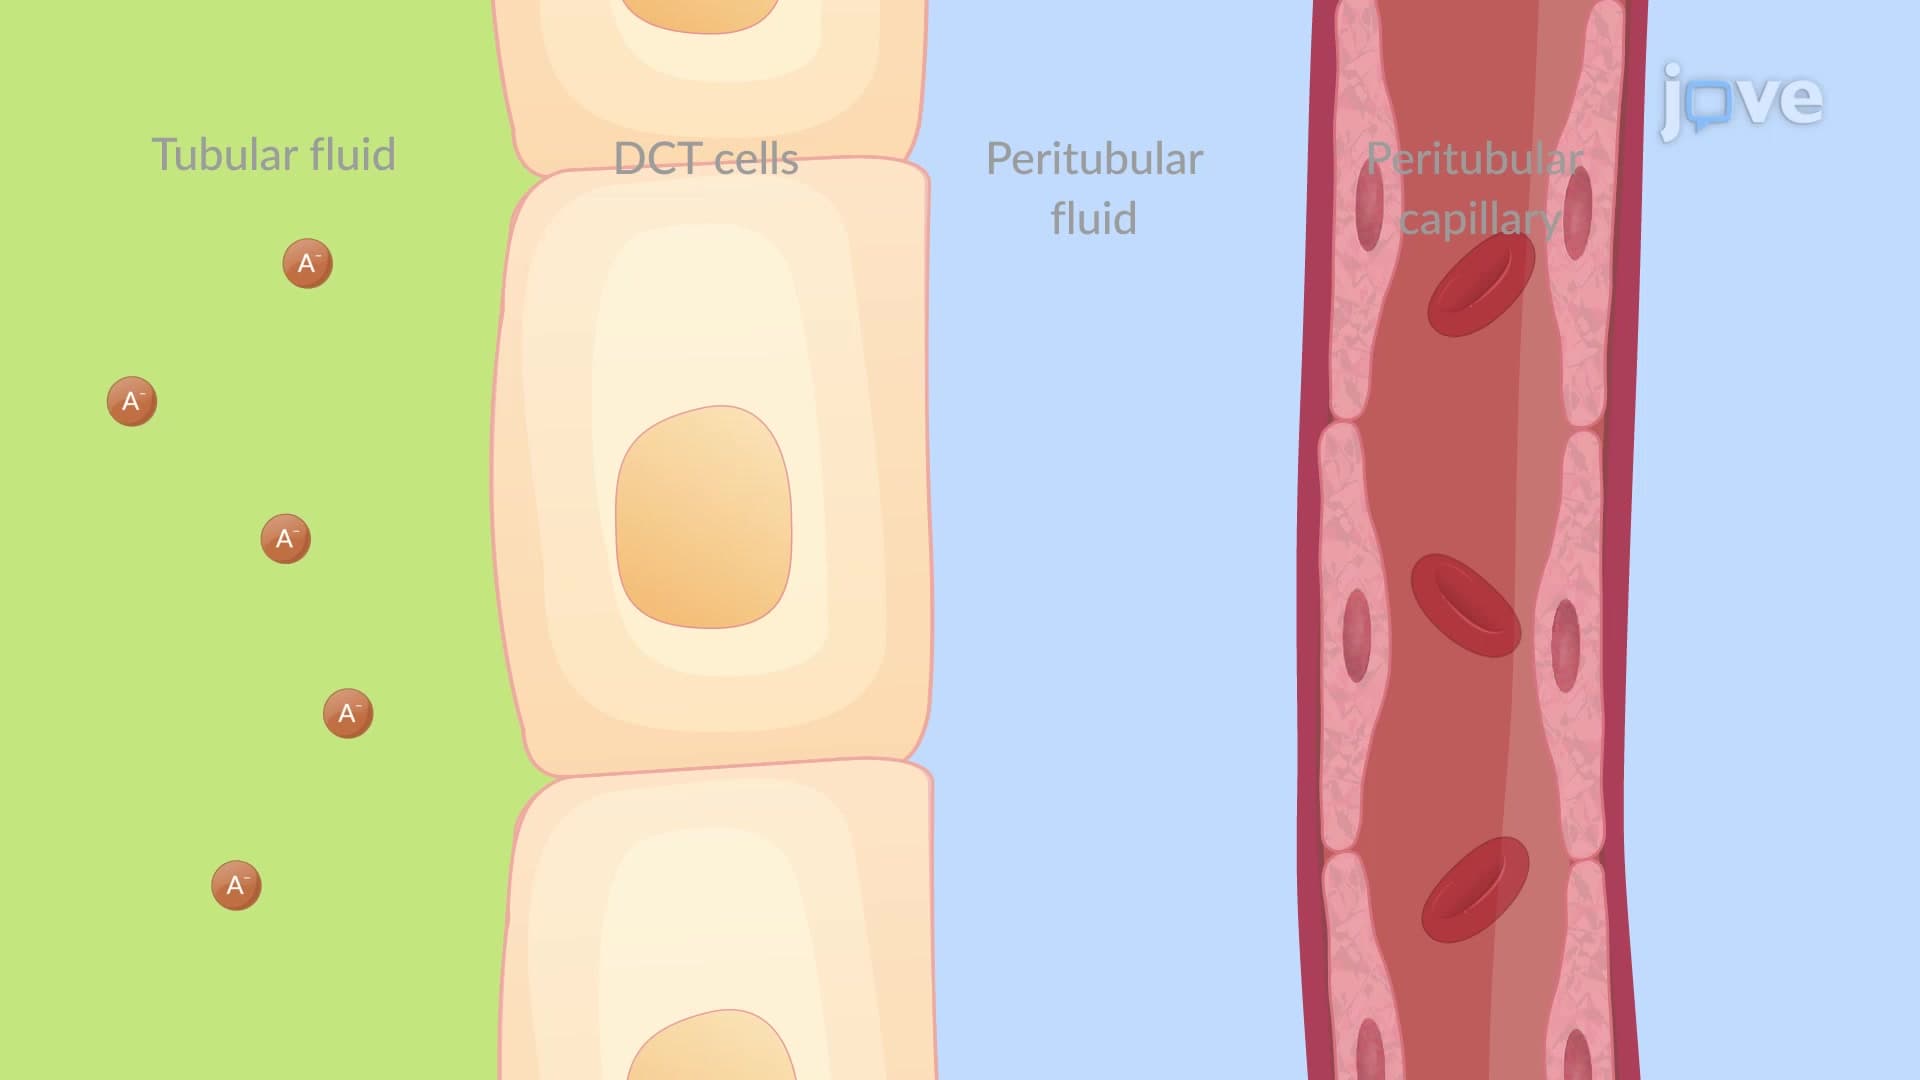
Drug Elimination by Renal Route: Tubular Reabsorption