Related Experiment Video
Updated: Oct 10, 2026
Cardiac Response to β-Adrenergic Stimulation Determined by Pressure-Volume Loop Analysis
Published on: May 19, 2021
[Density of beta-adrenergic receptors and left ventricular mass in patients with primary essential hypertension]

Insights
Beta-adrenergic receptor density remained unchanged in hypertensive patients and did not correlate with left ventricular mass. However, elevated blood pressure showed a strong correlation with left ventricular mass in stage II hypertension.
Area of Science:
- Cardiology
- Hypertension Research
- Molecular Cardiology
Background:
- Left ventricular hypertrophy (LVH) is a significant risk factor for sudden cardiac death.
- Hypertension is a primary driver of LVH, with the sympathetic nervous system potentially playing a key role.
- Understanding the relationship between neurohumoral mechanisms and cardiac remodeling is crucial in managing hypertension.
Purpose of the Study:
- To investigate the density of beta-adrenergic receptors in hypertensive patients.
- To examine the relationship between beta-adrenergic receptor density and left ventricular mass index (LVMI).
- To explore the correlation between blood pressure levels and LVMI in hypertensive individuals.
Main Methods:
- Recruited 63 patients with primary hypertension (Stage I and II) and 26 healthy controls.
- Assessed beta-adrenergic receptor density using the 125I-cyanopindolol radioligand labeling method.
- Measured left ventricular dimensions via echocardiography to calculate LVMI; analyzed correlations between variables.
Main Results:
- Hypertensive patients exhibited significantly higher systolic and diastolic blood pressure and LVMI compared to controls.
- No significant difference was found in beta-adrenergic receptor density between hypertensive patients and controls.
- Beta-adrenergic receptor density did not correlate with LVMI in the hypertensive group.
- A significant positive correlation was observed between LVMI and both systolic and diastolic blood pressure, particularly in Stage II hypertension.
Conclusions:
- Beta-adrenergic receptor density is not altered in hypertension and does not correlate with LVMI.
- A strong positive correlation exists between blood pressure and LVMI, specifically in patients with Stage II hypertension.
Unlabelled:
Left ventricular hypertrophy (LVH) is one of the more important risk factors for sudden death. There are multiple factors for development of LVH in patients with hypertension. Sympathetic nervous system may play a key role causing afterload increase and neurohumoral mechanisms activation. The aim of the study was to determine beta-adrenergic receptors density and its relations to left ventricular mass in hypertensive subjects. The study was carried out in 63 patients (23 women and 40 men), mean age 43.3 +/- 11.6 yrs with primary hypertension: stage I--42 pts and stage II--21 pts. The control group consisted of 26 healthy persons matched for age and sex. We evaluated the density of beta-adrenergic receptors using 125I-cyanopindolol radioligand labeling method. Left ventricular dimensions were assessed by echocardiography (Hewlett-Packard 77010 CF) and left ventricular mass index (LVMI) was calculated. Systolic and diastolic blood pressure and LVMI was significantly higher in hypertension group 156.7 +/- 12.5 vs. 119.8 +/- 8.8 mmHg, p < 0.0001, 95.9/5.5 vs. 78.8 +/- 6.5 mmHg, p < 0.0001, 126.5 +/- 41.9 vs. 93.1 +/- 19.9 g/m2, p < 0.001 respectively. Beta-adrenergic receptors density was 40.7 +/- 29.9 fmol/ml in the hypertensive vs. 37.2 +/- 17.8 fmol/ml in control group (p = NS). There was no correlation between beta-adrenergic receptors density and LVMI. There was a statistically significant positive correlation between LVMI and systolic and diastolic blood pressure (r = 0.44, p < 0.05; r = 0.60, p < 0.01 respectively).
Conclusions:
1. Beta-adrenergic receptors density was unchanged in patients with hypertension and did not correlate with LVMI. 2. A high positive correlation between blood pressure values and LVMI, but only in stage II hypertension was revealed.

Related Concept Videos
 01:17
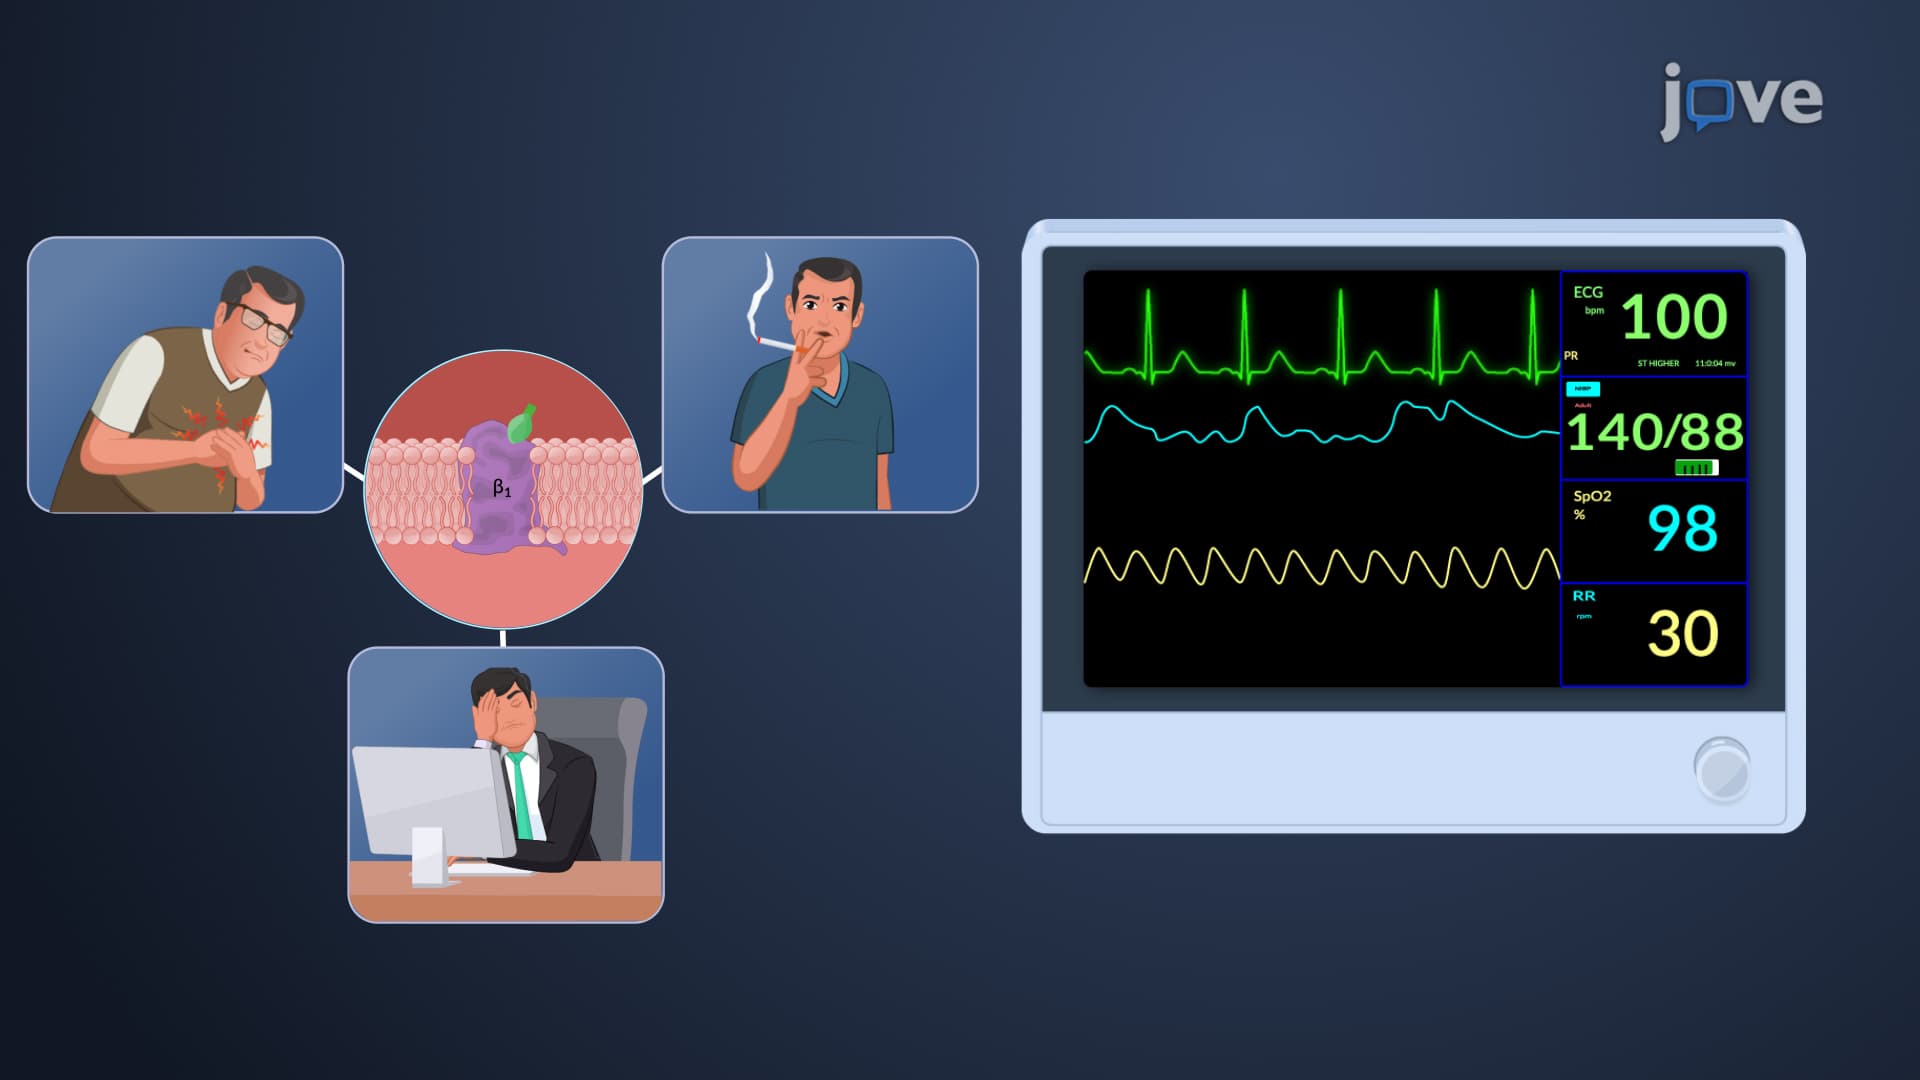
Antihypertensive Drugs: Action of β1 Blockers
 01:26
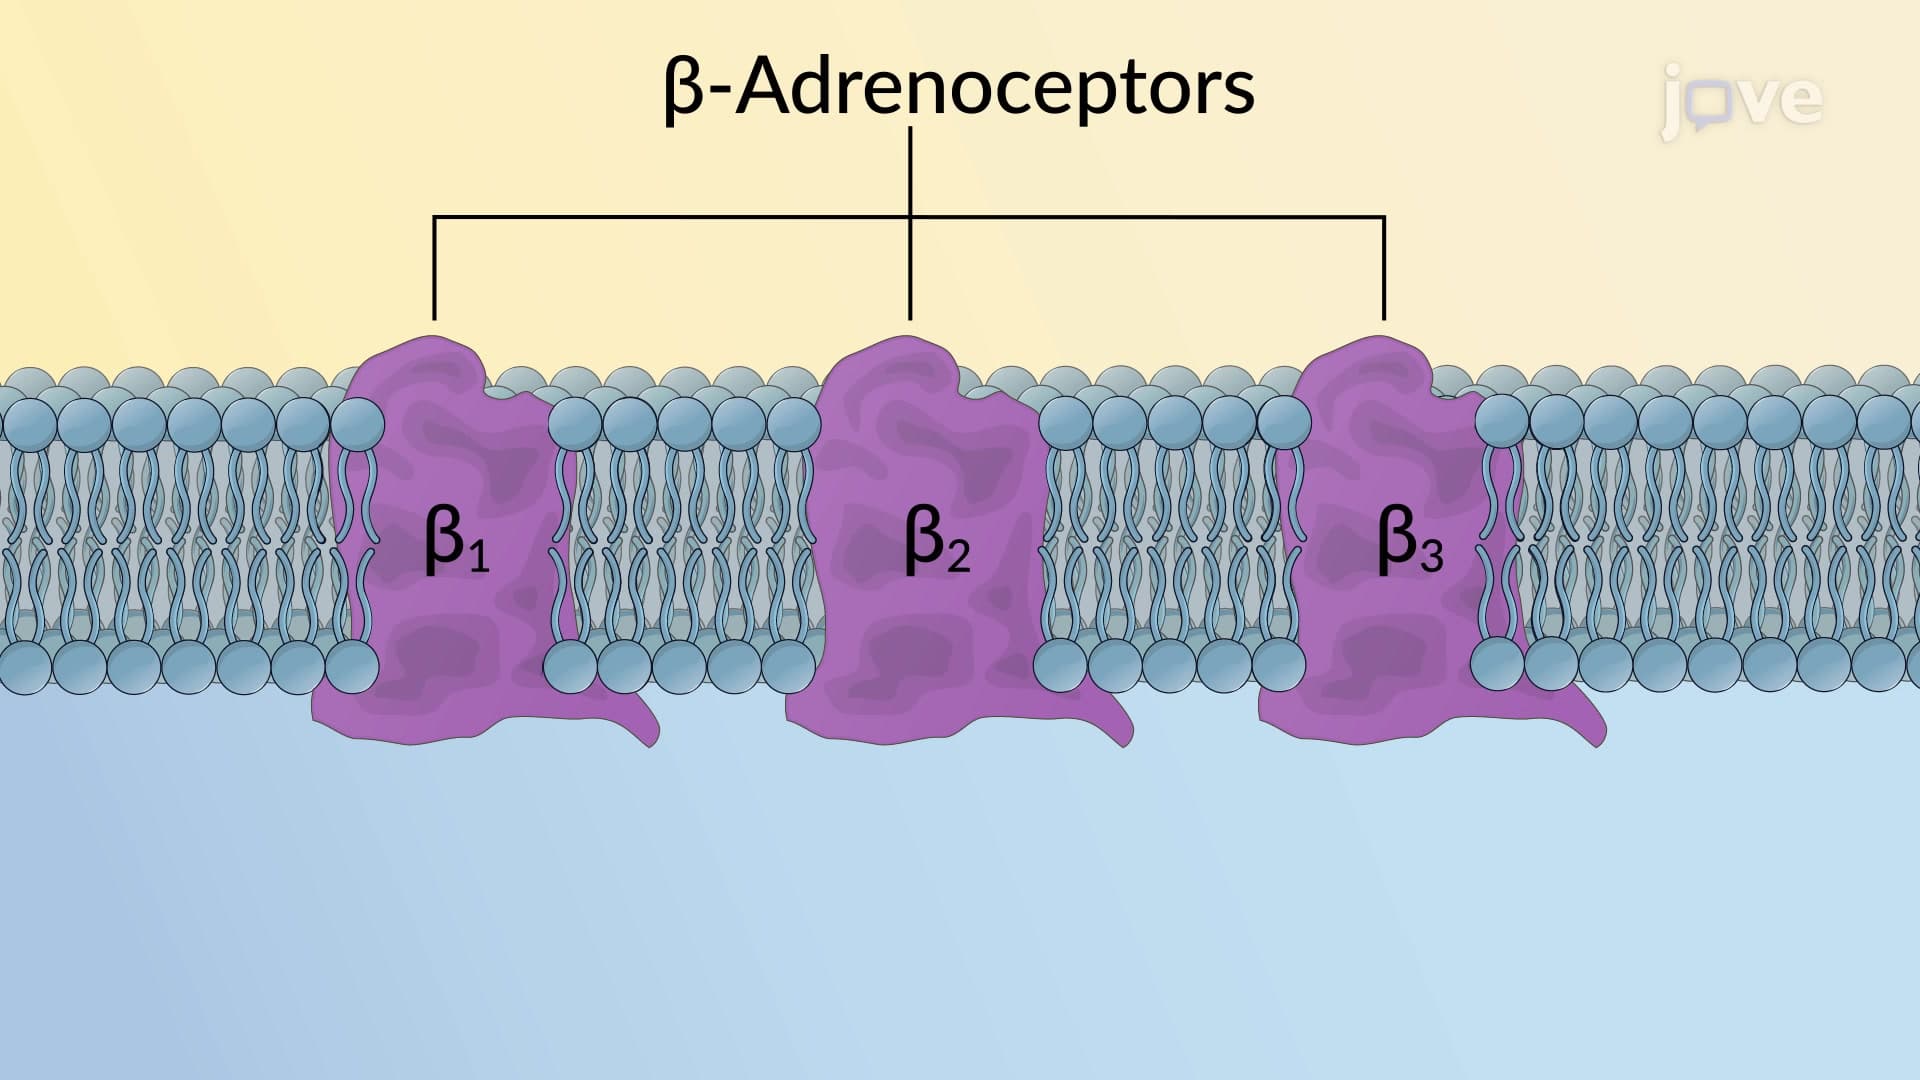
Adrenergic Receptors: β Subtype
Isoprenaline > Adrenaline > Noradrenaline
Neurotransmitter binding to these receptors causes activation of adenylyl cyclase resulting in increased concentrations of cAMP and modulation of calcium ion channels within the cell. They are further classified into β1, β2, and β3 subtypes.
β1-adrenoceptors: β1-adrenoceptors have equal affinities for...
 01:28
Antihypertensive Drugs: Types of β-Blockers
 01:29
Heart Failure II: Pathophysiology
 01:18
Hypertension and Regulation of Blood Pressure
 01:22
Heart Failure Drugs: β-Blockers