Related Experiment Video
Updated: Oct 10, 2026
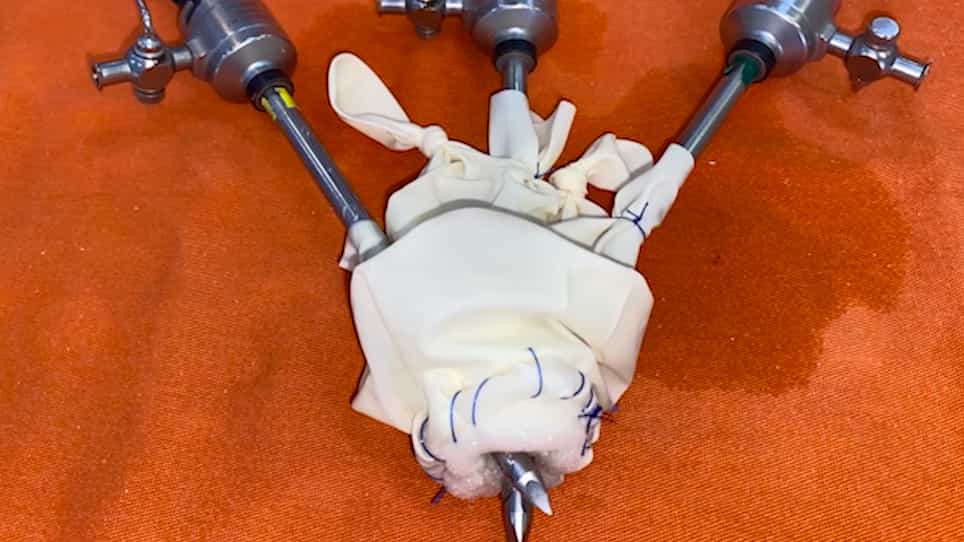
Low-Cost Single-Port (LoCoSP) Device for a Transcervical Approach in Minimally Invasive Transhiatal Esophagectomy
Published on: September 11, 2021
Injury to the major airways during subtotal esophagectomy: incidence, management, and sequelae
J B Hulscher1, E ter Hofstede, J Kloek
1Departments of Surgery, Cardio-pulmonary Surgery, and Anesthesiology, Academic Medical Center at the University of Amsterdam, Amsterdam, The Netherlands. J.B.Hulscher@AMC.UVA.NL

Objective:
The objective of this study was to gain insight into the incidence and sequelae of injury to the major airways during subtotal esophagectomy.
Methods:
We performed an analysis of 383 consecutive patients undergoing this procedure between 1993 and 1999. Indications were adenocarcinoma (220), squamous cell carcinoma (121), and other (42). Transhiatal resection was done in 269 (70%) patients and transthoracic resection in 114 (30%).
Results:
There were 4 men and 2 women (median age 57 years; range 45 to 68 years) with injury to the major airways, recognized during surgery in 5 patients and on the first postoperative day in the other. Five lesions occurred during transhiatal resection (5 of 269 = 1.8%) and 1 during transthoracic resection (1 of 114 = 0.8%; P =.67). The injury occurred proximal to the carina in 5 patients and in the left main bronchus in the other. All injuries could be closed primarily. The defect was covered with pericardium in 1 patient and with pleura in 2 patients. In all cases the gastric tube was placed over the defect. Pulmonary complications developed in 4 patients. Patients with tracheal injury required artificial ventilation for a longer period (median 6 days vs 1 day; P =.02) and stayed longer in the intensive care unit (median 11 vs 3 days; P <.01) than patients without such injury, although hospital time was not significantly prolonged (median 23 vs 16 days; P =.09). There was no associated mortality.
Conclusion:
Tracheobronchial injury is a rare complication of subtotal esophagectomy. It can be managed effectively by primary closure and apposition of vital tissue (gastric tube) to the defect. It is associated with pulmonary complications, leading to prolonged assisted ventilation and stay in the intensive care unit, but mortality is rare.

Related Concept Videos
 01:28
Esophageal Perforation-II: Clinical Manifestations and Management
Clinical Manifestations:
 01:22
Esophageal Perforation-I: Introduction
The location of esophageal perforation can vary, occurring anywhere along the esophagus.
 01:30
Esophageal Strictures-I: Introduction
Etiology
The primary cause of esophageal strictures is long-standing gastroesophageal reflux disease (GERD), accounting for about 70 to 80% of adult cases. Chronic acid reflux can lead to injury and scarring of the esophageal lining, culminating in...
 01:17
Endotracheal Intubation II: Nursing Management
1. Nursing Care of Patients Before Intubation
Before the endotracheal intubation procedure, nurses play an essential role in ensuring the process goes smoothly. The nurses must be familiar with intubation...
 01:24
Endotracheal Tube Extubation
Procedure
Extubation removes the endotracheal tube (ETT) from the patient on mechanical ventilation. It requires a well-coordinated, multidisciplinary approach involving physicians, nurses, respiratory therapists, and other healthcare professionals.
 01:26
Esophageal Strictures-II: Clinical Features and Management
Healthcare providers should gather a comprehensive medical history and conduct a physical examination for diagnosis. If esophageal stricture is...