Related Experiment Video
Updated: Oct 10, 2026
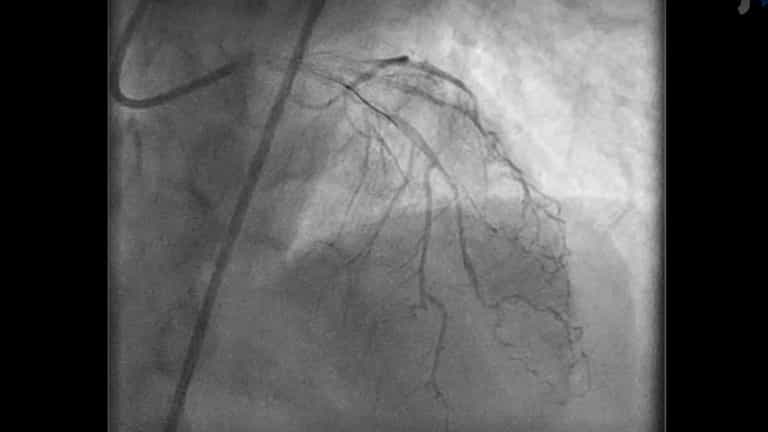
Acetylcholine Re-Challenge After Intracoronary Nitroglycerine Administration
Published on: April 4, 2022
First line drugs in chronic stable effort angina--the case for newer, longer-acting calcium channel blocking agents
1Heart Research Unit and Hatter Institute, Cape Heart Center, University of Cape Town, South Africa. opie@capeheart.uct.ac.za

Insights
New evidence suggests calcium channel blockers (CCBs) may be a viable alternative to beta-blockers for managing chronic stable angina, especially newer, longer-acting formulations. Verapamil shows particular promise for safety and efficacy.
Area of Science:
- Cardiology
- Pharmacology
Background:
- Current guidelines recommend beta-adrenergic blocking agents as first-line treatment for chronic stable effort angina.
- This recommendation is based on established evidence, but newer data may warrant a reassessment.
Purpose of the Study:
- To critically re-examine the evidence for calcium channel blocking agents (CCBs) in managing chronic stable angina.
- To evaluate safety, side-effects, tolerability, and mortality data, particularly for newer CCB generations.
Main Methods:
- Review of newly available and potentially overlooked evidence not cited by current guidelines.
- Inclusion of recent clinical trials and a meta-analysis of placebo-controlled trials on long-acting CCBs.
- Evaluation of safety, tolerability, and mortality data.
Main Results:
- Newer, longer-acting, second-generation CCBs demonstrate good tolerability and benefits in hypertension.
- Verapamil, an older CCB, is highlighted for its safety and efficacy.
- Dihydropyridine CCBs and beta-blockers show similar effectiveness in angina associated with hypertension, particularly in the elderly.
- Beta-blockers can have undesirable side effects like impotence and reduced exercise capacity.
Conclusions:
- The current recommendation for first-line beta-blockers for chronic stable angina may need reconsideration.
- CCBs, especially newer formulations and verapamil, present a strong alternative with favorable safety and efficacy profiles.
- Individual patient needs and pathophysiology should guide the choice between beta-blockers and CCBs.
Abstract:
The American College of Cardiology-American Heart Association Committee recommends first line beta-adrenergic blocking agents for chronic stable effort angina. This article reassesses some critical evidence that is new or could have been neglected by the Committee. In particular, the putative role of calcium channel blocking agents (CCBs) is reexamined. Additional evidence is culled from articles not cited by the Committee, together with added reference to recent trials. Safety, side-effects and tolerability are issues that are evaluated. Mortality data are reviewed with the aid of a meta-analysis of all placebo-controlled trials on long acting CCBs. The advice of the committee may need to be reconsidered in view of recent evidence on the tolerability and benefits in hypertension of newer, longer-acting, second-generation CCBs. Of the older agents, verapamil has been shown to be the best with regard to safety and efficacy. Especially in the elderly, angina is often associated with hypertension, with evidence showing dihydropyridine CCBs and beta-adrenergic blocking agents to be similarly effective. Beta-blockers may have undesirable side effects such impotence and impaired exercise ability, despite their proven protective effects in postinfarct patients and in heart failure. The choice of drug should be keyed to the needs and the pathophysiology of the individual patient.

Related Concept Videos
 01:25
Antianginal Drugs: Calcium Channel Blockers and Ranolazine
CCBs, a diverse class that includes dihydropyridines (nifedipine) and diphenylalkylamines (verapamil and diltiazem), exert their effect by blocking calcium channels in cardiac and smooth muscle cells. This...
 01:16
Antianginal Drugs: Nitrates and β-Blockers
Organic nitrates, such as nitroglycerin, play a pivotal role. Once metabolized, they liberate nitric oxide, a molecular marvel. Nitric oxide triggers guanylyl cyclase and augments cGMP production. This biochemical cascade orchestrates the relaxation of vascular smooth muscles, ushering in vasodilation and enhancing coronary blood flow. Administered...
 01:26
Angina IV: Management
 01:27
Coronary Artery Disease V: Interprofessional Care
 01:18
Antihypertensive Drugs: Action of Calcium Channel Blockers
 01:20
Antiarrhythmic Drugs: Class IV Agents as Calcium Channel Blockers
Verapamil, a calcium channel blocker, inhibits calcium movement across myocardial cell membranes and vascular smooth muscle. This results in the dilation of coronary and...