Related Experiment Video
Updated: Jul 31, 2026


A Thrombotic Stroke Model Based On Transient Cerebral Hypoxia-ischemia
Published on: August 18, 2015
Acute Ischemic Stroke
1Stanford Stroke Center, 701 Welch Road, Building B, Suite 325, Palo Alto, CA 94304-1705, USA.

Insights
Rapid evaluation and treatment are crucial for acute ischemic stroke patients. Intravenous t-PA within 3 hours is recommended for eligible patients, with careful risk-benefit assessment. Aspirin is an alternative for non-eligible individuals.
Area of Science:
- Neurology
- Emergency Medicine
- Cardiovascular Research
Background:
- Acute ischemic stroke requires immediate medical attention for optimal outcomes.
- Timely administration of thrombolytic therapy can significantly improve patient prognosis.
- Established guidelines exist for the use of thrombolytics and anticoagulants in stroke management.
Purpose of the Study:
- To outline the recommended evaluation and treatment protocols for acute ischemic stroke patients.
- To emphasize the importance of adhering to established treatment guidelines for t-PA administration.
- To provide guidance on alternative therapies and supportive care for stroke patients.
Main Methods:
- Review of current clinical guidelines and research findings on acute ischemic stroke management.
- Analysis of eligibility criteria and risk-benefit considerations for intravenous thrombolysis (t-PA).
- Assessment of alternative pharmacological interventions, including aspirin and heparin, for stroke patients.
Main Results:
- Intravenous t-PA within 3 hours of symptom onset is the primary recommended treatment for eligible acute ischemic stroke patients.
- Informed consent regarding the risk of symptomatic cerebral hemorrhage is essential prior to t-PA administration.
- Aspirin is recommended for patients ineligible for t-PA, while heparin has specific indications and is not a standard treatment.
- Low-dose subcutaneous heparin is advised for deep vein thrombosis prophylaxis in immobilized patients.
- Management by a dedicated stroke team facilitates prompt diagnosis, treatment, and rehabilitation initiation.
Conclusions:
- Prompt transport and evaluation are critical for acute ischemic stroke patients.
- Strict adherence to the NINDS study protocol for t-PA optimizes the risk-benefit ratio.
- A multidisciplinary approach and collaboration with stroke centers enhance patient care and outcomes.
Abstract:
Patients with acute ischemic stroke should be immediately transported to the nearest hospital for rapid evaluation and treatment. Intravenous t-PA within 3 hours of symptom onset is the recommended treatment for patients who meet the National Institute of Neurological Disorders and Stroke (NINDS) study eligibility criteria. Patients should be informed of the risk of symptomatic cerebral hemorrhage, and strict adherence to the NINDS study protocol is strongly recommended to optimize the risk-benefit ratio. Ischemic stroke patients who are not eligible for t-PA therapy should usually be started on aspirin. Intravenous heparin is not recommended as a standard treatment but may be considered for specific patient subgroups. Low-dose subcutaneous heparin is recommended for prophylaxis of deep vein thrombosis in immobilized patients. Management of stroke patients by a designated stroke team is recommended to facilitate prompt diagnosis and treatment and early initiation of rehabilitation therapy. We also recommend that physicians who manage patients with acute stroke maintain contact with local or regional stroke centers to facilitate referral of appropriate patients for intensive care or specialized diagnostic tests or therapies.
Related Concept Videos
 01:29
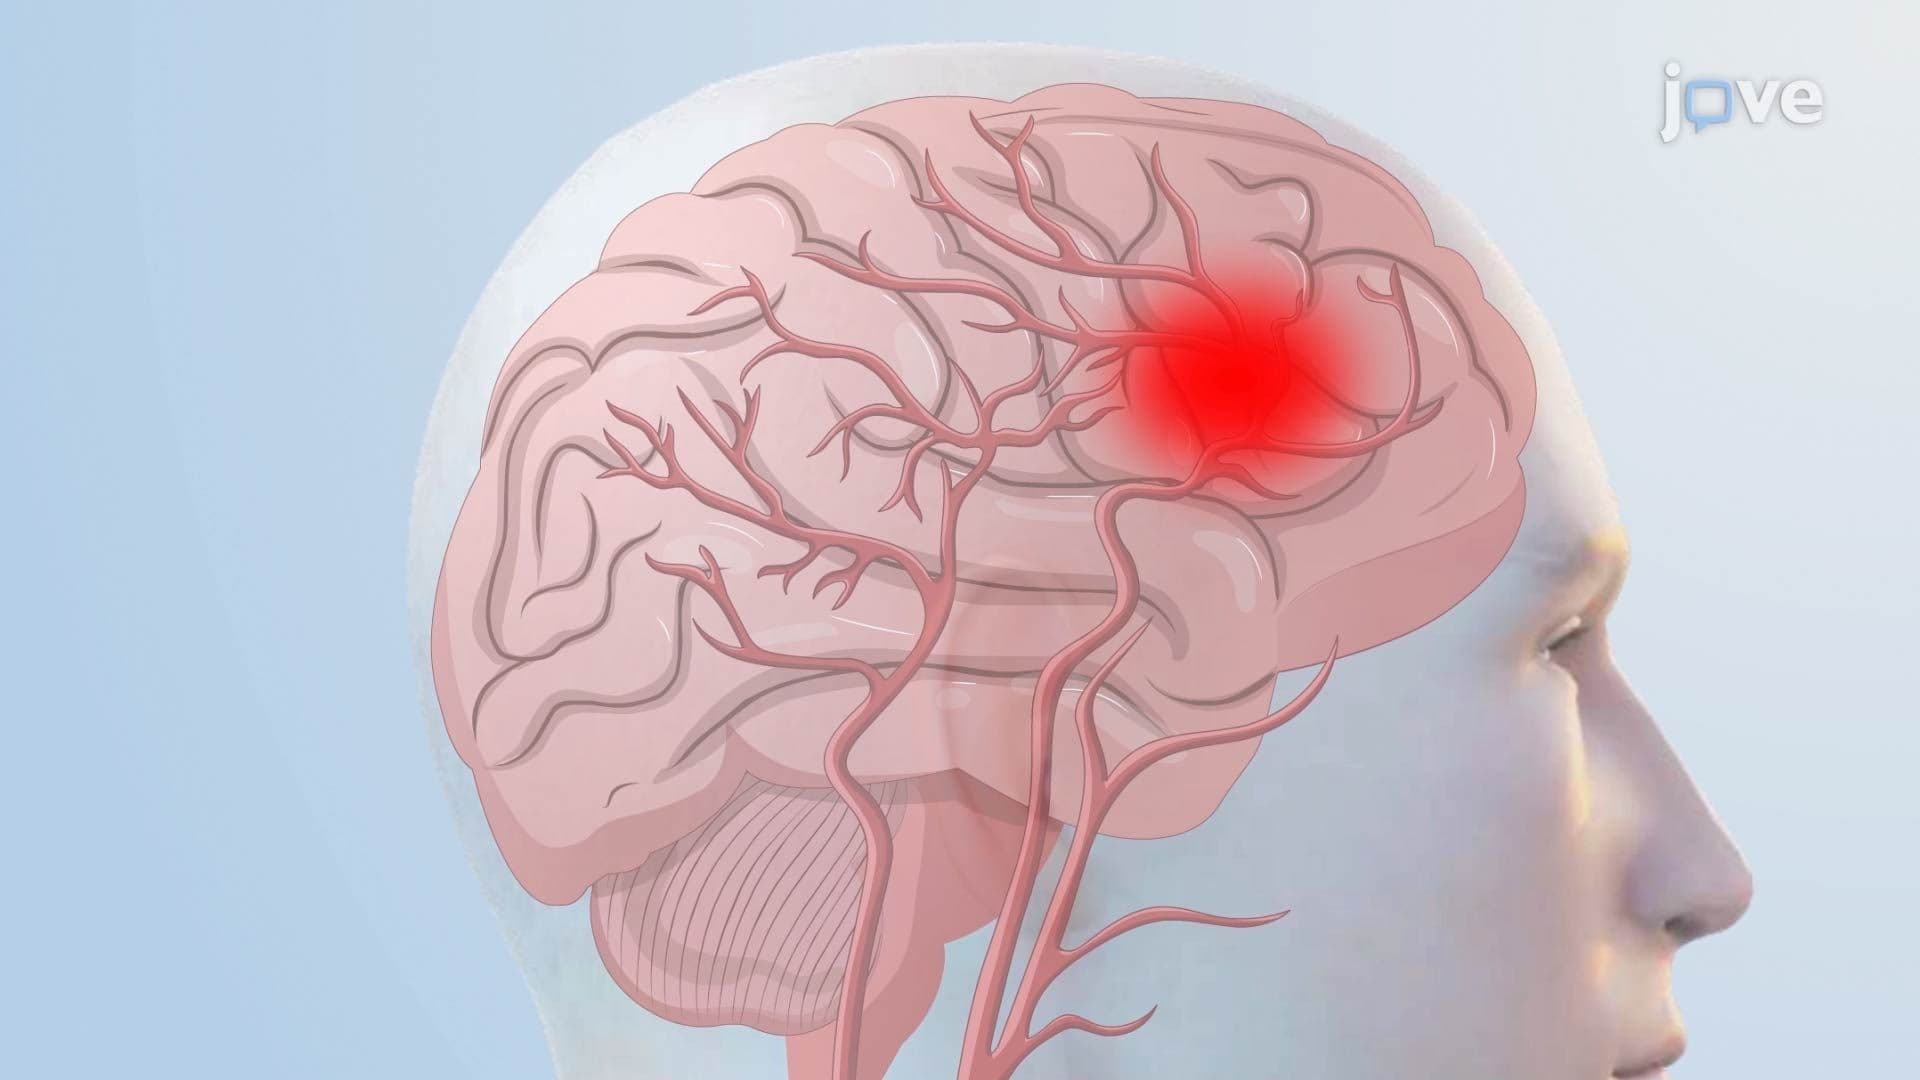
Stroke: Introduction and Types
 01:15
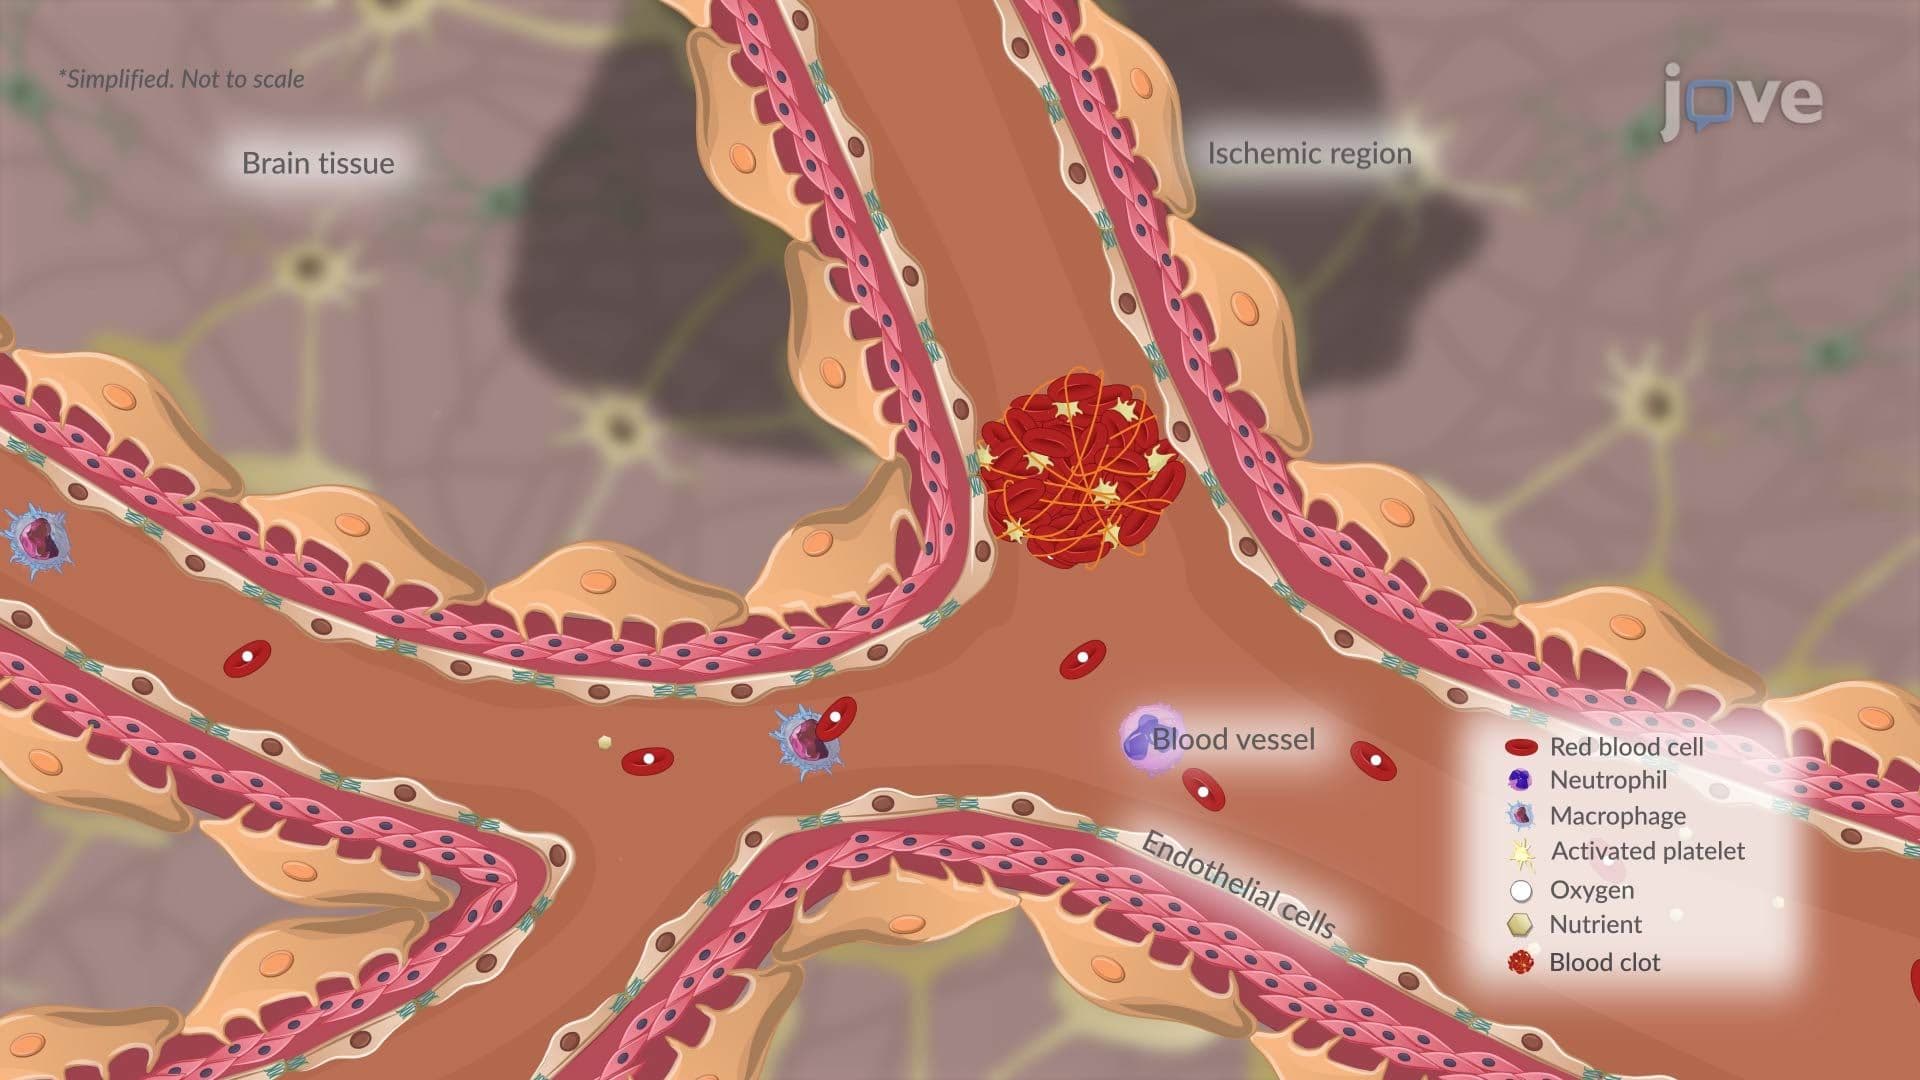
Ischemic Stroke l: Introduction
 01:15
Ischemic Stroke ll: Pathophysiology
 01:17
Hemorrhagic Stroke l: Introduction
 01:29
Hemorrhagic Stroke ll: Pathophysiology
 01:26
Transient Ischemic Attack l: Introduction