Related Experiment Video
Updated: Aug 3, 2026

Invasive Hemodynamic Characterization of the Portal-hypertensive Syndrome in Cirrhotic Rats
Published on: August 1, 2018
Update on peripheral arterial vasodilation, ascites and hepatorenal syndrome in cirrhosis
M Knotek1, B Rogachev, R W Schrier
1University of Colorado Health Sciences Center, Denver 80262, USA.

Abstract:
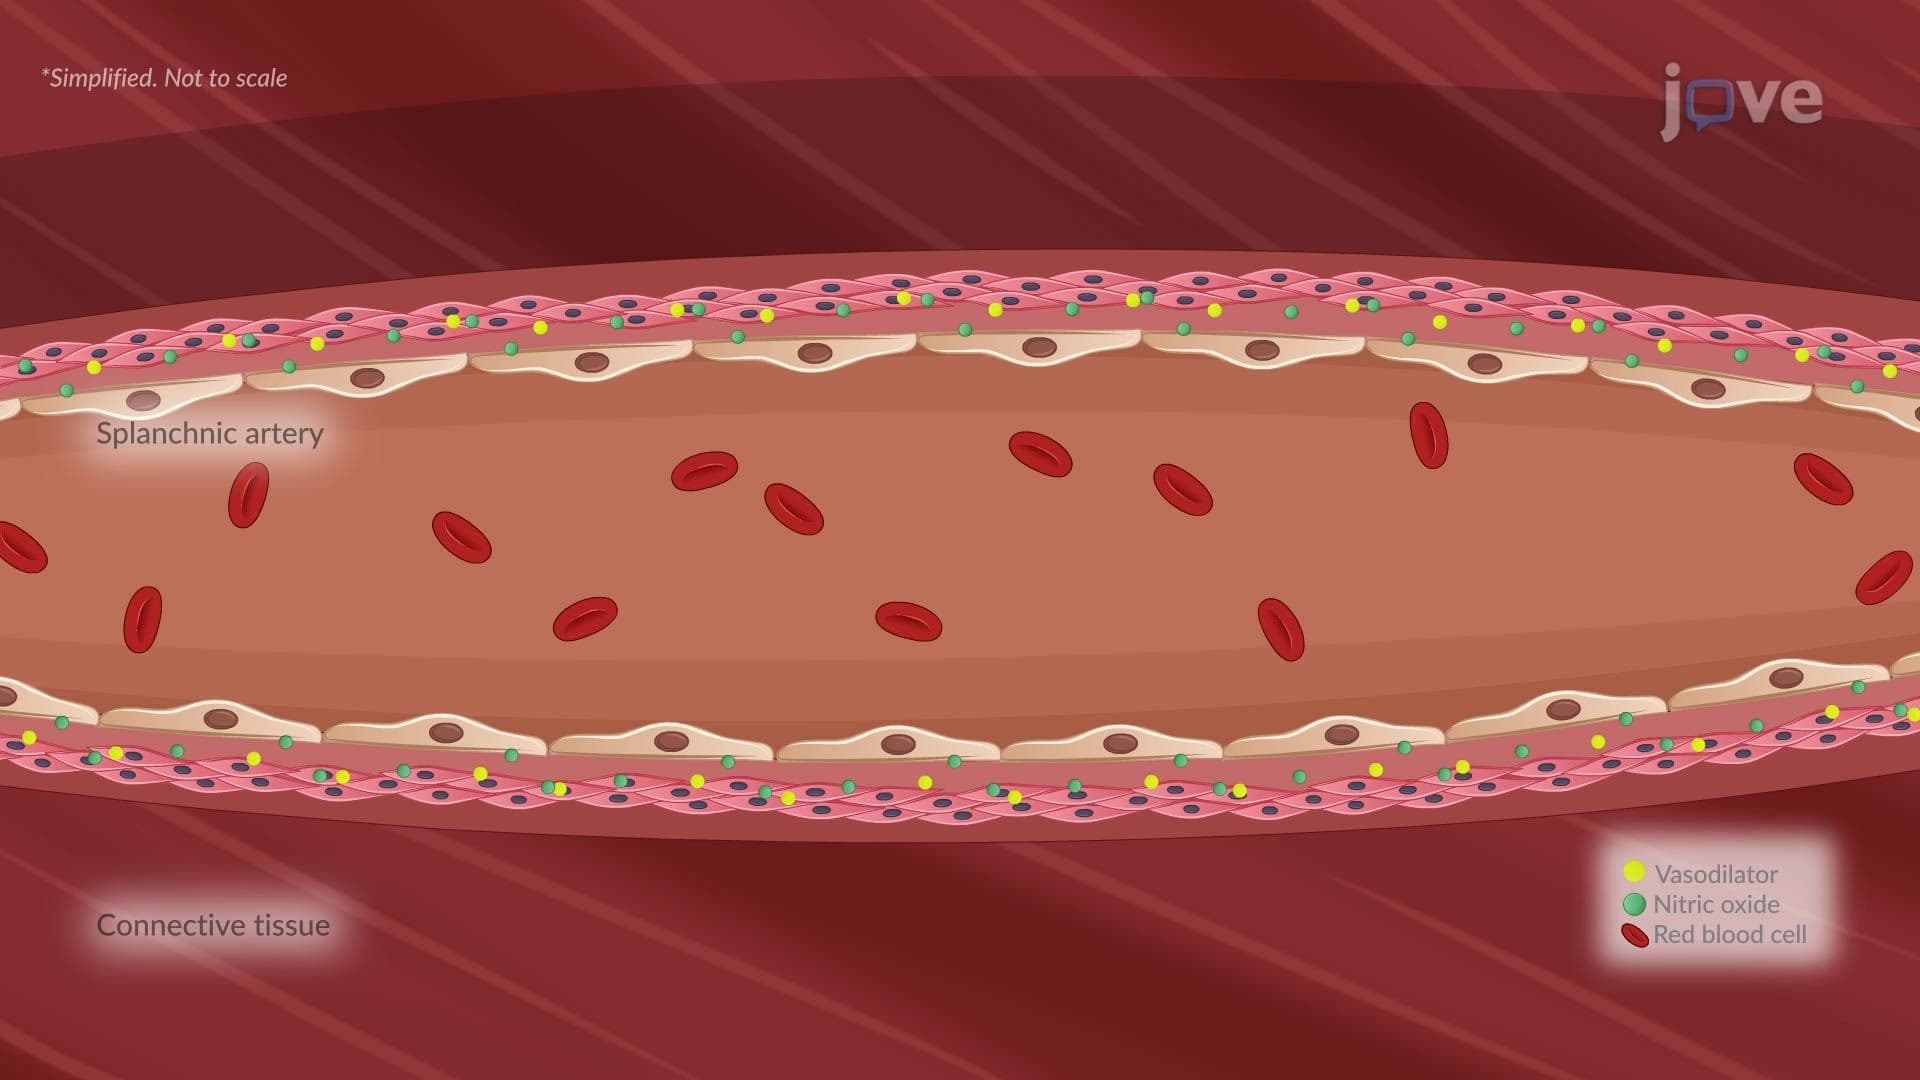
In cirrhosis of the liver, according to the peripheral arterial vasodilation hypothesis, relative underfilling of the arterial tree triggers a neurohumoral response (activation of renin-angiotensin-aldosterone system, sympathetic nervous system, nonosmotic release of vasopressin) aimed at restoring circulatory integrity by promoting renal sodium and water retention. Evidence has accumulated for a major role of increased vascular production of nitric oxide as the primary cause of arterial vasodilation in cirrhosis. Ascites is a common complication in cirrhosis. Treatment of ascites consists of a low salt diet with diuretics, and paracentesis together with plasma volume expanders in diuretic-resistant patients. Progression of cirrhosis may result in hepatorenal syndrome, a state of functional renal failure that carries an ominous prognosis. Orthotopic liver transplantation has remained the only curative treatment for patients with advanced liver disease; other modalities such as transjugular intrahepatic portosystemic shunt or vasopressin analogues may serve as a bridge to transplantation. Another complication of decompensated cirrhosis is spontaneous bacterial peritonitis, the incidence of which can be reduced by primary or secondary antibiotic prophylaxis by using orally active antibiotics.
More Related Videos


Related Concept Videos
 01:26
Effect of Hepatic Disease on Pharmacokinetics: Drug Dosing and Hepatic Blood Flow
 01:21
Peripheral Arterial Disease II: Clinical Manifestations and Diagnostic Evaluation
 01:23
Peripheral Artery Disease V: Postoperative Nursing Management
 01:24
Cirrhosis II: Pathophysiology
 01:22
Portal Hypertension
 01:19
Ascites