Related Experiment Video
Updated: Jul 1, 2026
Biochemical Measurement of Neonatal Hypoxia
Published on: August 24, 2011
Hypothyroxinemia of prematurity: rite of passage or therapeutic necessity?
1Department of Pediatrics, Scott & White Memorial Hospital and Clinic, Scott, Sherwood and Brindley Foundation, Texas A&M University System Health Science Center College of Medicine, Temple, Tex., USA.

Insights
Thyroid hormone supplementation may harm premature infants over 27 weeks gestation but could benefit those born earlier. Careful consideration is needed for treating hypothyroxinemia in preterm neonates.
Area of Science:
- Neonatal endocrinology
- Pediatric thyroid disorders
Background:
- Hypothyroxinemia is common in premature infants due to immature thyroid axis.
- This condition is often considered physiologic and self-resolving.
- True hypothyroidism requires aggressive investigation and treatment.
Purpose of the Study:
- To evaluate the necessity and impact of thyroid hormone supplementation in premature infants.
- To differentiate between physiologic hypothyroxinemia and true hypothyroidism.
- To determine optimal management strategies for thyroid dysfunction in preterm neonates.
Main Methods:
- Review of current studies on premature infants with hypothyroxinemia.
- Analysis of outcomes based on gestational age.
- Comparison of infants receiving and not receiving thyroid hormone supplementation.
Main Results:
- Infants born after 27 weeks gestation may experience harm from thyroid hormone supplementation.
- Short-term supplementation may reduce morbidity and improve neurodevelopment in infants born before 27 weeks.
- Dynamic thyroid function tests in premature infants are typically normal.
Conclusions:
- Thyroid hormone supplementation is not universally required for premature infants.
- Gestational age is a critical factor in deciding on thyroid hormone supplementation.
- Targeted supplementation for very preterm infants may improve outcomes.
Abstract:
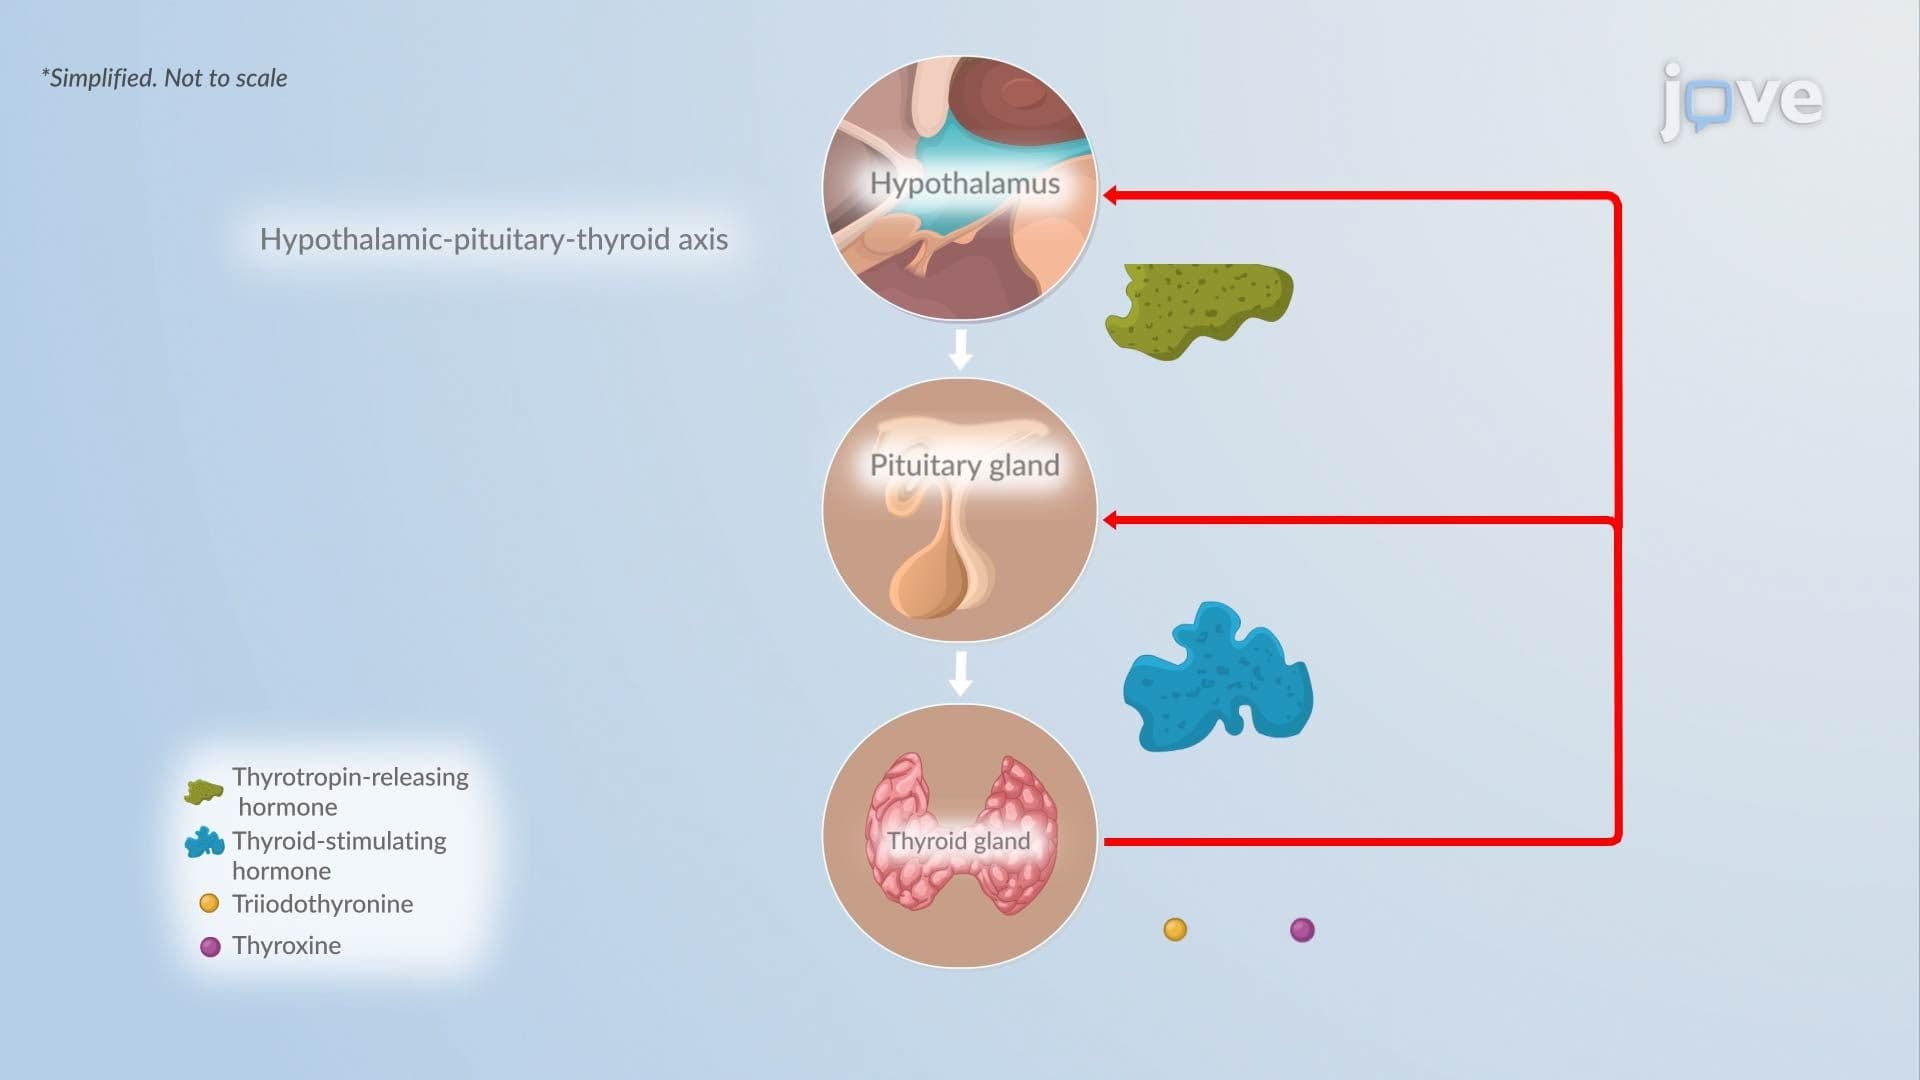
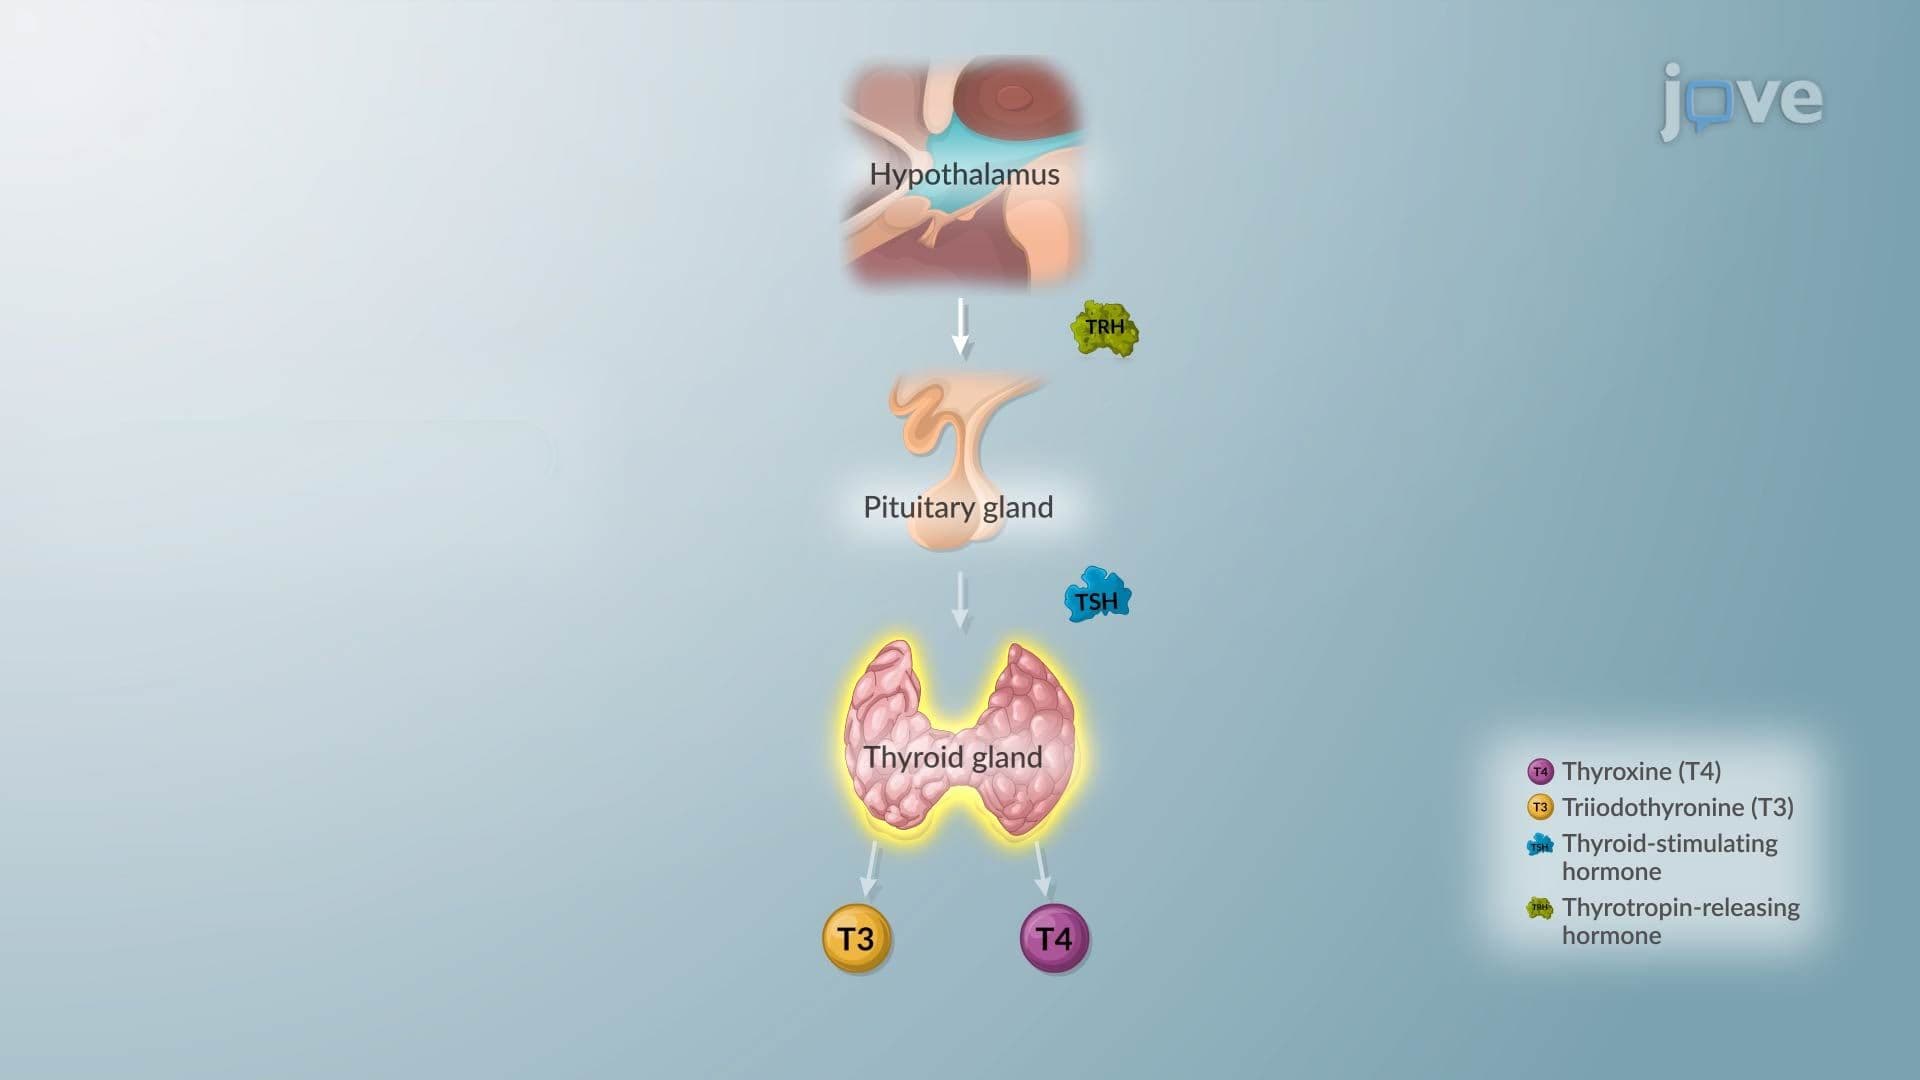
Hypothyroxinemia is a common finding in premature infants, presumably resulting from an immature hypothalamic-pituitary-thyroid axis. Because dynamic studies of thyroid function in premature infants are normal and the condition resolves spontaneously, HOP has been considered physiologic rather than pathologic. Thus, thyroid hormone supplementation has been assumed to be not required in premature infants. True hypothyroidism of hypothalamic pituitary or thyroid origin, however, does occur in premature as well as in term infants and should be investigated aggressively and treated appropriately. Current studies in premature infants with hypothyroxinemia suggest the following: infants with more than 27 weeks of gestation do not appear to benefit and may, in fact, be harmed by thyroid hormone supplementation; and short-term thyroid hormone supplementation in infants born before 27 weeks of gestation may be important to diminish morbidity and to improve neurodevelopmental outcome.


Related Concept Videos
 01:20
Synthesis and Regulation of Thyroid Hormones
Upon reaching the thyroid gland, TSH stimulates the follicular cells' active uptake of iodide ions from the blood. The ions diffuse to the apical surface of the cells and are oxidized to iodine. The iodine is then...
 01:18
Functions of Thyroid Hormones
TH is indispensable for the normal development and maturation of the skeletal, muscular, and nervous systems during fetal and childhood growth. It facilitates bone mineral turnover and regulates protein synthesis in developing tissues, contributing significantly to overall growth and...
 01:25
Hyperthyroidism I: Introduction
 01:27
Hyperthyroidism II: Pathophysiology
 01:24
Graves Disease II: Pathophysiology
 01:23
Hypothyroidism II: Pathophysiology