Related Experiment Video
Updated: Oct 10, 2026

Cell-free Biochemical Fluorometric Enzymatic Assay for High-throughput Measurement of Lipid Peroxidation in High Density Lipoprotein
Published on: October 12, 2017
Differences in HDL-cholesterol:apoA-I + apoA-II ratio and apoE phenotype with albuminuric status in Type I diabetic
S S Soedamah-Muthu1, H M Colhoun, M R Taskinen
1EURODIAB, Royal Free and UCL Medical School, London, UK.

Aims/Hypothesis:
To examine whether the HDL-cholesterol:apoA-I + apoA-II ratio and the epsilon2 allele are related to albuminuria at baseline and whether they are risk factors for progression of albuminuria in a cohort study of patients with Type I (insulin-dependent) diabetes mellitus.
Methods:
At baseline, the study cohort comprised 617 patients, aged 15-60 years, from seven European diabetic centres of the EURODIAB study. Albumin excretion rate, measured in a central laboratory, was categorised as normoalbuminuria at 20 microg/min or less, microalbuminuria between 20 and 200 microg/min or macroalbuminuria at 200 microg/min or over. Of the 250 patients who were normoalbuminuric at baseline and had follow-up albuminuria measurements, 34 patients were defined as early progressors.
Results:
At baseline, the mean HDL-cholesterol:apoA-I + apoA-II ratio was lower in macroalbuminuric patients (0.79, 95 % CI:0.74-0.83) compared with normoalbuminuric (0.88, 95 % CI:0.87-0.90) patients (p = 0.0002, adjusted for age and sex). At follow-up, 34 patients who progressed from normoalbuminuria to microalbuminuria or macroalbuminuria also had a slightly lower baseline ratio (0.85, 95% CI:0.80-0.89) than those 216 who remained normoalbuminuric (0.89, 95 % CI:0.87-0.92) (adjusted p = 0.08). Neither of these relations were independent of LDL-cholesterol or fasting triglyceride. There was no association of the epsilon2 allele with albuminuria either at baseline (OR = 1.4, 95% CI:0.7-2.8) or with progression of albuminuria (OR = 0.4, 95 % CI:0.1-3.5).
Conclusion/Interpretation:
There is an inverse relation of HDL-cholesterol:apoA-I + apoA-II ratio with albuminuria at baseline. This lower ratio in microalbuminuric or macroalbuminuric patients could contribute to the increased risk of cardiovascular disease associated with nephropathy. There is weak evidence that HDL-composition is a risk factor for progression of albuminuria and no association of the epsilon2 allele with diabetic nephropathy.
Related Concept Videos
 01:19
Type I Diabetes III: Clinical Manifestations
 01:26
Type I Diabetes II: Pathophysiology
 01:24
Type II Diabetes II: Pathophysiology
 01:29
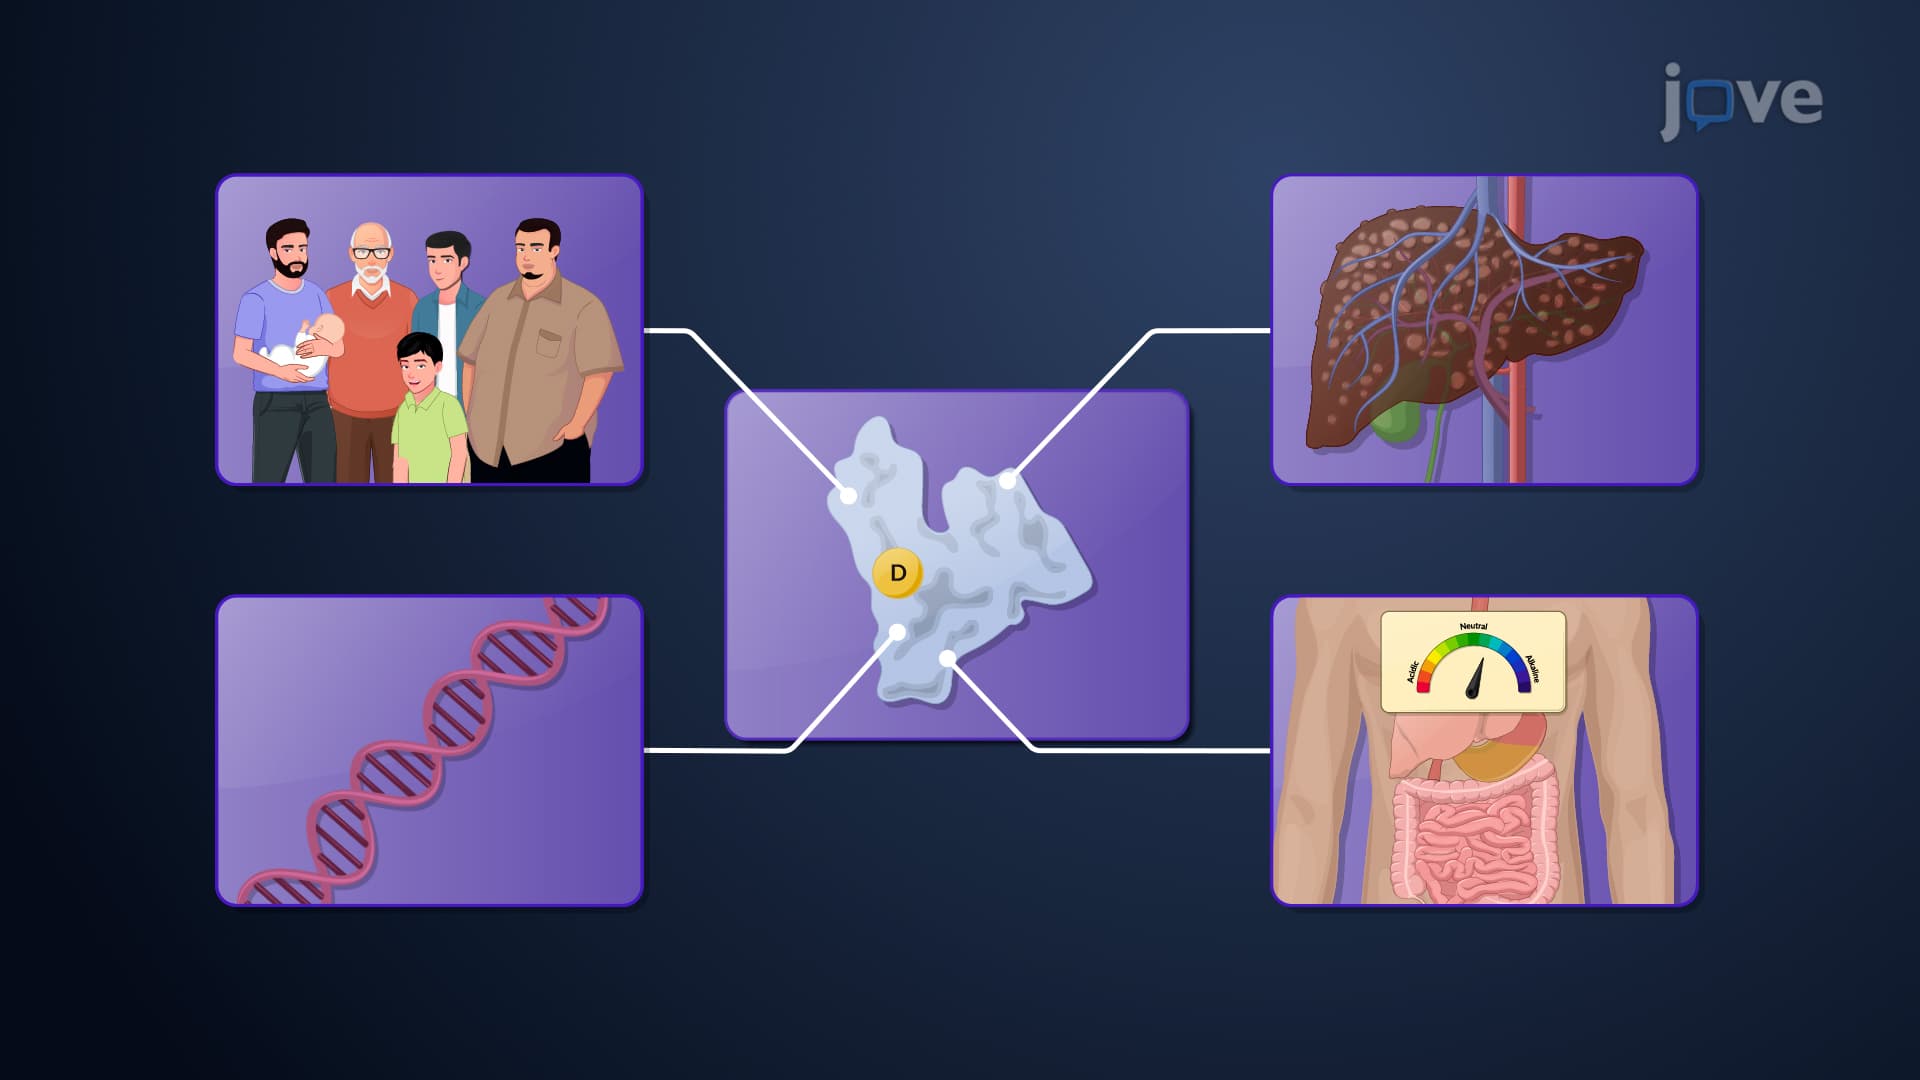
Factors Affecting Protein-Drug Binding: Patient-Related Factors
Age stands as a key determinant in protein-drug binding. Neonates, characterized by low albumin content, experience heightened concentrations of unbound drugs such as phenytoin and...
 01:26
Atherosclerosis III: Management
 01:26
Type II Diabetes I: Introduction