Related Experiment Video
Updated: Oct 10, 2026
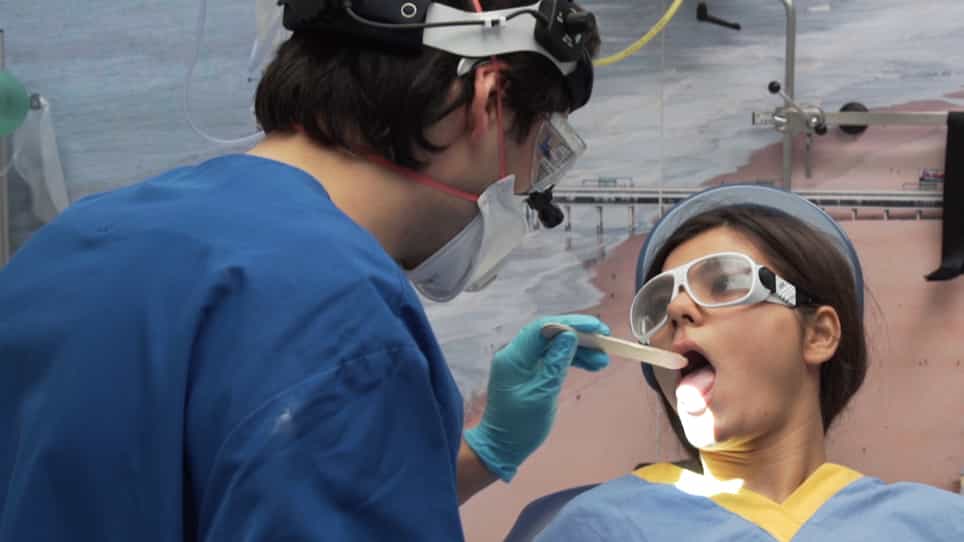

CO2-Lasertonsillotomy Under Local Anesthesia in Adults
Published on: November 6, 2019
Evaluating the effects of oral prednisolone on recovery after tonsillectomy: a prospective, double-blind, randomized
C E Palme1, P Tomasevic, D V Pohl
1Department of Otolaryngolgy Head and Neck Surgery, St. George Hospital, Kogarah, Sydney, Australia.

Objectives:
To investigate the role of a 7-day course of oral prednisolone on recovery from tonsillectomy.
Study Design:
Double-blind, randomized, placebo-controlled trial of 50 consecutive patients, aged 5 years and older, who had no previous or known contraindications to steroid therapy.
Methods:
The patients were randomized at the time of surgery to either a 7-day course of daily placebo or prednisolone (dosage: 10 mg per day in patients aged 5-11 y, 0.5 mg/kg in those aged 12 and older). Age, sex, weight, diagnosis, tonsil size (in cm2), additional adenoidectomy, performing surgeon, method of dissection, length of procedure, total blood loss, intraoperative fluid requirement, and length of hospitalization were documented for each patient. During the first postoperative day, morning pain score, paracetamol use, oral fluid intake, temperature, presence of nausea and vomiting, level of activity (low, moderate, or normal), and type of diet (liquid, soft, or normal) were recorded.
Results:
The steroid group consisted of a greater number of diathermy dissection cases and had significantly less intraoperative blood loss (P value = .022 and .017, respectively). On postoperative days 4 to 7, the steroid group experienced less nausea and vomiting (P value = .01, .04, .04, and .04, respectively). Paracetamol use was less in the steroid group on days 2, 7, and 8 (P value = .03, .02, and .02, respectively). There was no difference between the two groups for the other data measured.
Conclusion:
A 7-day course of corticosteroids may play a limited role in patients' recovery from tonsillectomy.
Related Concept Videos
 01:23
Chronic Pharyngitis
Etiology
It often arises from persistent viral or bacterial infections affecting sinuses and tonsils.
Additional contributing factors include inadequate dental hygiene, mouth breathing, recurring tonsillitis, allergic rhinitis, laryngopharyngeal reflux, and exposure to smoke, chemicals, and other environmental pollutants. Allergic reactions to pollen, mold, and pet dander, chronic cough, excessive voice usage,...
 01:26
Tonsillitis II: Management