Related Experiment Video
Updated: Oct 10, 2026
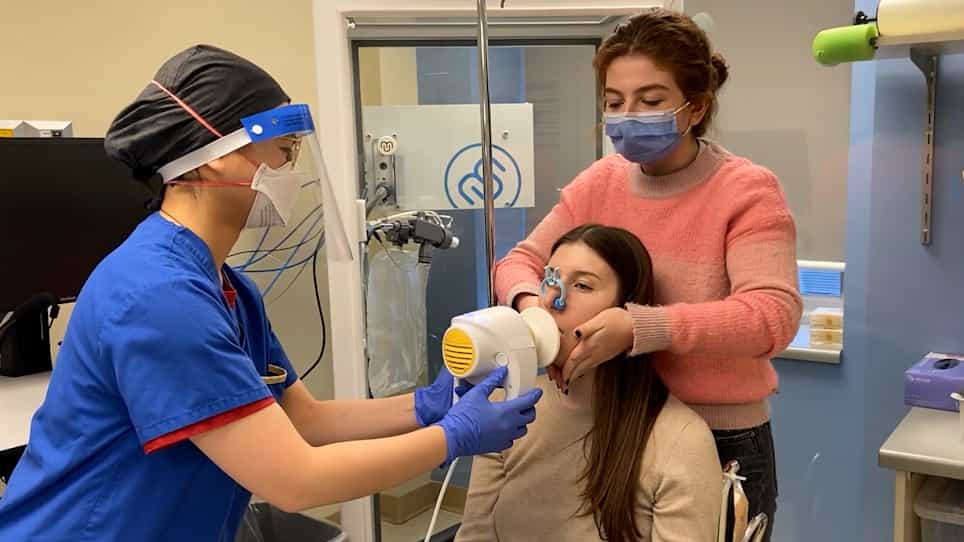
Conducting Respiratory Oscillometry in an Outpatient Setting
Published on: April 8, 2022
Clinical score and arterial oxygen saturation in children with wheezing associated respiratory illness (WARI)
S Sritippayawan1, J Deerojanawong, N Prapphal
1Department of Pediatrics, Faculty of Medicine, Chulalongkorn University, Bangkok 10330, Thailand.

Objectives:
To determine the correlation between clinical score (based on respiratory rate, chest wall retractions, air entry, wheezing, consciousness and audible wheezing) and arterial oxygen saturation (SaO2: measured by pulse oximetry) as well as the most appropriate total score for predicting hypoxemia (SaO2 < or = 95%) in children diagnosed to have wheezing associated respiratory illness (WARI).
Subjects:
70 children (1 month-5 years old) hospitalized in the Department of Pediatrics, Chulalongkorn Hospital with the diagnosis of WARI from January 1, 1996 to December 31, 1996 were studied. Half of them were diagnosed to have acute lower respiratory tract infection (LRI) with wheezing while the remainder had reactive airway disease (RAD).
Design:
Cross sectional, analytical study.
Methods:
In each group of patients, the clinical score and SaO2 were assessed by the same pediatrician throughout the study. The correlation between the clinical signs and SaO2 as well as the cut off point of total score for predicting hypoxemia were analyzed. The sensitivity, specificity and accuracy of that total score in predicting hypoxemia were also calculated.
Result:
In both groups of patients (acute LRI with wheezing and RAD group), the clinical signs correlated with SaO2 were wheezing (rs = -0.67 and -0.47 respectively) and chest wall retractions (rs = -0.57 and -0.59 respectively). Total score was also correlated with SaO2 (rs = -0.68 and -0.5 respectively). The cut off point of total score in predicting hypoxemia was 4 providing 80 per cent sensitivity in both groups with accuracy 74.3 per cent and 80 per cent respectively.
Conclusion:
This clinical score may be used to assess the severity of hypoxemia in WARI patients. Wheezing, chest wall retractions and total score correlated well with SaO2. The total score > 4 was most appropriate in predicting hypoxemia in both children with RAD and wheezing associated with LRI.
Related Concept Videos
 01:19
Special considerations while measuring oxygen saturation
Ensuring accuracy in vital sign recordings while prioritizing patient comfort and minimizing anxiety is important.
 01:20
Assessment of Ventilation I: Respiratory Rate
A Ventilation assessment is critical for monitoring a patient's health status. Respiration, one of the most accessible vital signs, provides insights into the function of numerous body systems and can indicate serious health issues, such as brainstem injuries from head trauma.
Critical Guidelines for Assessing Ventilation:
 01:23
Assessment of Respiration
Subjective Assessment: Nurses interview the patient to gather information directly during the subjective assessment. It includes questions about the individual's medical history, medications, and symptoms, focusing on past respiratory conditions like asthma or COPD,...
 01:30
Assessment of Airway, Skin Color, and Use of Accessory Muscles
Introduction
The initial evaluation of a patient's respiratory system...
 01:29
Assessment of Ventilation II: Respiratory Depth and Rhythm
Respiratory depth measures the volume of air inhaled or exhaled during a breath. It can vary from shallow to deep and typically remains consistent when a person is at rest or asleep. Occasionally, individuals will automatically inhale deeply, known as sighing, which inflates the lungs with more air than normal breathing.
To assess respiratory depth, observe the degree of chest excursion or movement:
 01:27
Chronic Obstructive Pulmonary Disease-IV: Assessement and Diagnostic Studies
Medical History