Related Experiment Video
Updated: Oct 9, 2026

Quantification of the Immunosuppressant Tacrolimus on Dried Blood Spots Using LC-MS/MS
Published on: November 8, 2015
Pharmacokinetics of cyclosporin in children with stable renal transplants
J C Tam1, J W Earl, N S Willis
1Centre for Kidney Research, Royal Alexandra Hospital for Children, PO Box 3515, Parramatta, NSW Australia 2124.

Insights
Cyclosporine A (CSA) peak concentration (Cmax) is a better indicator of drug exposure in pediatric kidney transplant patients than trough levels (Cmin). Child
Area of Science:
- Pharmacokinetics
- Pediatric Nephrology
- Transplantation
Background:
- Cyclosporine A (CSA) is a crucial immunosuppressant in pediatric kidney transplantation.
- Optimizing CSA dosing is vital for graft survival and minimizing toxicity.
- Understanding CSA absorption variability in children is essential for effective therapeutic drug monitoring.
Purpose of the Study:
- To evaluate the pharmacokinetic profile of cyclosporine A (CSA) in pediatric kidney transplant recipients.
- To compare the utility of peak concentration (Cmax) versus trough concentration (Cmin) as a measure of CSA exposure.
- To explore the relationship between patient age and CSA pharmacokinetic parameters.
Main Methods:
- Pharmacokinetic analysis of whole blood CSA levels in 14 children (5-17 years) post-kidney transplant.
- Measurement of CSA concentrations at multiple time points after the morning dose.
- Model-independent pharmacokinetic analysis to determine AUC, CL/F, Vss/F, Tdel, Tmax, and Cmax.
Main Results:
- Significant variability in absorption delay time (Tdel) and time to peak concentration (Tmax) was observed.
- Patient age positively correlated with Tmax (Tmax = 0.027 age + 1.41).
- Area under the curve (AUC) showed a strong correlation with Cmax (Cmax = 0.25 AUC + 423.32), suggesting Cmax is a reliable indicator of exposure.
Conclusions:
- Peak cyclosporine A concentration (Cmax) is a more suitable measure of drug exposure than trough concentration (Cmin) in pediatric kidney transplant patients.
- Age influences the time to reach peak CSA levels, which can inform blood sampling strategies.
- Further research may refine age-based predictions for optimal CSA monitoring in children.
Abstract:
Fourteen children, aged between 5 and 17 years, with stable renal graft function and stable cyclosporin A (CSA) trough levels (Cmin) were studied. They had been taking CSA 12-hourly since their transplant 1.5-9 years previously, with the average dose of Neoral being 6.4 (range 4.4-8.4) mg/kg per day. CSA whole blood levels were measured at 0, 20, and 40 min, and at 1, 1.5, 2, 2.5, 3, 4, 6, and 8 h following the morning dose using the Abbott TDx fluorescence polarization immunoassay. The area under the concentration time curve (AUC), clearance adjusted for bioavailability (CL/F), and steady-state volume of distribution adjusted for bioavailability (Vss/F) were determined using model-independent pharmacokinetic analysis. Delay time (Tdel), peak concentration (Cmax), time to peak concentration (Tmax), and Cmin were also determined and correlated with AUC and other parameters. The Tdel in absorption varied from 0.3 to 1.6 (mean 0.73) h, resulting in a similarly variable time to Tmax of 1-2.4 h (mean 1.59). Tmax was related to the age of the patient (Tmax = 0.027 age + 1.41, r2 = 0.56, P < 0.005). The AUC showed good correlation with Cmax (Cmax = 0.25 AUC + 423.32, r2 = 0.96, P < 0.0005). Cmax appears to be a more-suitable measure of exposure to CSA than Cmin. Prediction of Tmax from the age of the child may help to overcome the problem of when to collect blood for peak levels.

Related Concept Videos
 01:26
Pharmacokinetics in Pediatric Patients: Drug Excretion
 01:24
Pharmacokinetics in Pediatric Patients: Drug Metabolism
 01:17
Pharmacokinetics in Pediatric Patients: Drug Distribution
 01:23
Pharmacokinetics in Pediatric Patients: Overview and Drug Absorption
 01:18
Pharmacokinetics in Geriatric Patients: Effect of Age on Drug Excretion
 01:20
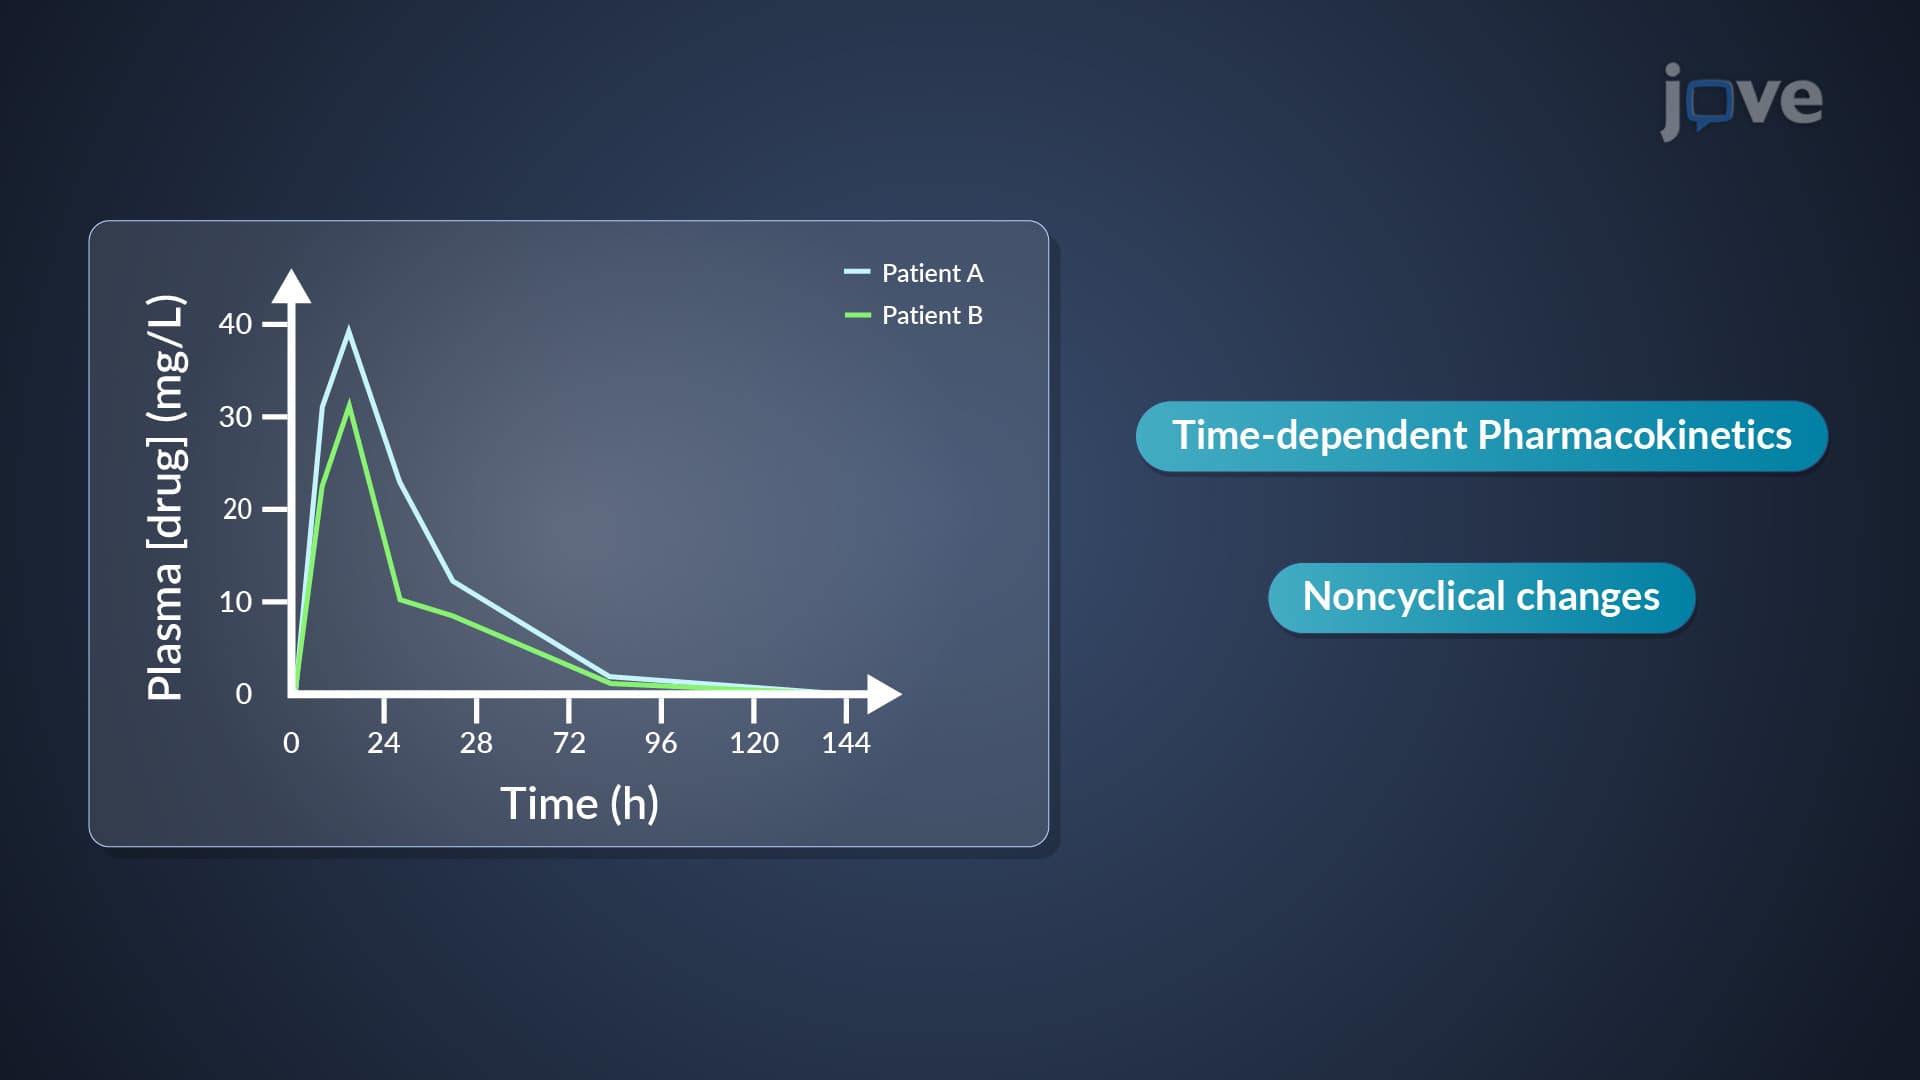
Chronopharmacokinetics: Time-Dependent Pharmacokinetics
Time-dependent pharmacokinetics refers to non-cyclical changes in drug rate processes over a period of time. It can lead to nonlinear pharmacokinetics, where the relationship between drug concentration and time is not proportional. Non-cyclical...