Related Experiment Video
Updated: Oct 9, 2026


Human Primary Trophoblast Cell Culture Model to Study the Protective Effects of Melatonin Against Hypoxia/reoxygenation-induced Disruption
Published on: July 30, 2016
Oxygen transport in tibetan women during pregnancy at 3,658 m
L G Moore1, S Zamudio, J Zhuang
1Department of Anthropology, University of Colorado at Denver, Denver, Colorado 80262, USA. Lorna.g.moore@uchsc.edu

High-altitude reduces infant birth weight as a result of intrauterine growth restriction (IUGR) and is associated with increased neonatal mortality. We hypothesized that babies born to Tibetan compared to Han (Chinese) high-altitude residents were protected from IUGR as the result of increased maternal O(2) transport due, in turn, to increased uterine artery (UA) blood flow. We studied 68 nonpregnant or pregnant Tibetan or Han residents of Lhasa, Tibet Autonomous Region, China (3,658 m). The pregnant women had higher hypoxic ventilatory responses (HVR A) and resting ventilations (V(E)) than their nonpregnant counterparts (Tib HVR = 134 +/- 16 (SEM) vs. 30 +/- 8, Han HVR = 134 +/- 16 vs. 66 +/- 18 A units; Tib V(E) = 11.8 +/- 0.3 vs. 10.1 +/- 0.5, Han V(E) = 10.7 +/- 0.5 vs. 9.4 +/- 0.5 l BTPS/min; all P < 0.05). Pregnancy did not change hemoglobin concentration in the Han but lowered values more than 2 g/dl in the Tibetans, serving to reduce arterial O(2) content below Han values (15.4 +/- 0.3 vs. 17.4 +/- 0.5 ml O(2)/100 ml whole blood, P < 0.05). Compared with the Han, the pregnant Tibetans had higher UA blood flow velocity (58.5 +/- 2.9 vs. 49.1 +/- 3.2, P < 0. 05) and distributed a higher portion of common iliac (CI) blood flow to the UA (4.8 +/- 0.4 vs. 3.3 +/- 0.3, P < 0.05). Birth weights averaged 635 g greater in the Tibetan than Han high-altitude residents (3,280 +/- 78 vs. 2,645 +/- 96 g, P < 0.01), or 694 g more when adjusted for maternal age, parity, height, and near-term body weight. Heavier birth weight babies were born to women with higher V(E) (r = 0.62, P < 0.01) and greater distribution of CI blood flow to the UA (r = 0.42, P < 0.05). We conclude that increased UA blood flow, and not higher arterial O(2) content, permits Tibetan women to increase uteroplacental O(2) delivery and protect their infants from altitude-associated IUGR.
High-altitude reduces infant birth weight as a result of intrauterine growth restriction (IUGR) and is associated with increased neonatal mortality. We hypothesized that babies born to Tibetan compared to Han (Chinese) high-altitude residents were protected from IUGR as the result of increased maternal O(2) transport due, in turn, to increased uterine artery (UA) blood flow. We studied 68 nonpregnant or pregnant Tibetan or Han residents of Lhasa, Tibet Autonomous Region, China (3,658 m). The pregnant women had higher hypoxic ventilatory responses (HVR A) and resting ventilations (V(E)) than their nonpregnant counterparts (Tib HVR = 134 +/- 16 (SEM) vs. 30 +/- 8, Han HVR = 134 +/- 16 vs. 66 +/- 18 A units; Tib V(E) = 11.8 +/- 0.3 vs. 10.1 +/- 0.5, Han V(E) = 10.7 +/- 0.5 vs. 9.4 +/- 0.5 l BTPS/min; all P < 0.05). Pregnancy did not change hemoglobin concentration in the Han but lowered values more than 2 g/dl in the Tibetans, serving to reduce arterial O(2) content below Han values (15.4 +/- 0.3 vs. 17.4 +/- 0.5 ml O(2)/100 ml whole blood, P < 0.05). Compared with the Han, the pregnant Tibetans had higher UA blood flow velocity (58.5 +/- 2.9 vs. 49.1 +/- 3.2, P < 0. 05) and distributed a higher portion of common iliac (CI) blood flow to the UA (4.8 +/- 0.4 vs. 3.3 +/- 0.3, P < 0.05). Birth weights averaged 635 g greater in the Tibetan than Han high-altitude residents (3,280 +/- 78 vs. 2,645 +/- 96 g, P < 0.01), or 694 g more when adjusted for maternal age, parity, height, and near-term body weight. Heavier birth weight babies were born to women with higher V(E) (r = 0.62, P < 0.01) and greater distribution of CI blood flow to the UA (r = 0.42, P < 0.05). We conclude that increased UA blood flow, and not higher arterial O(2) content, permits Tibetan women to increase uteroplacental O(2) delivery and protect their infants from altitude-associated IUGR.
Related Concept Videos
 01:27
Oxygen Transport in the Blood
 01:20
Respiration and Gaseous Exchange
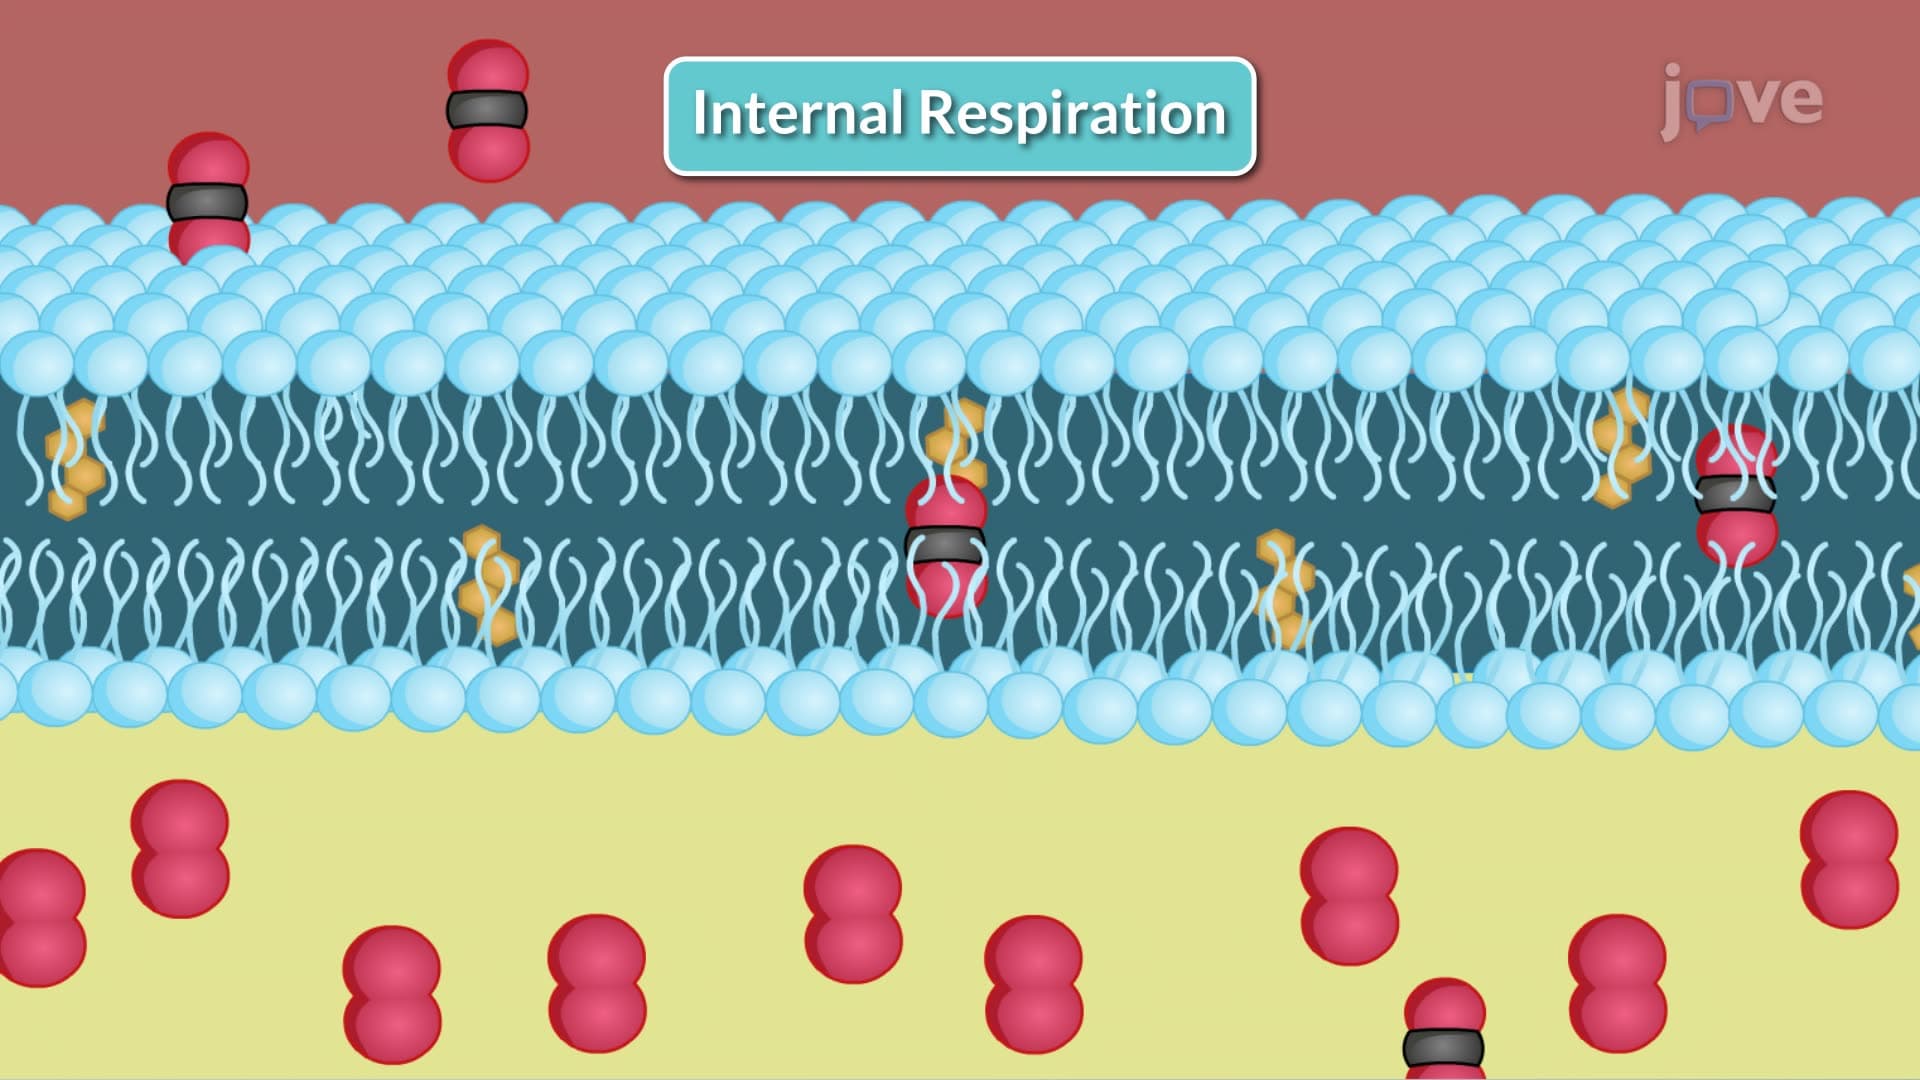
Respiration involves the exchange of gases, especially oxygen (O2) and carbon dioxide (CO2), between the alveoli and body cells, a process facilitated by blood circulation. As a result, the cardiovascular system, which involves the...
 01:19
Carbon Dioxide Transport in the Blood
Forms of CO2 Transport
1. Dissolved in plasma: A small percentage (7-10%) of CO2 is transported and dissolved directly in the plasma.
2. Carbaminohemoglobin: Just over 20% of CO2 is chemically bound to...
 01:19
Special considerations while measuring oxygen saturation
Ensuring accuracy in vital sign recordings while prioritizing patient comfort and minimizing anxiety is important.
 01:24
Factors Affecting Respiration
 01:16
Oxygen Delivering System II: Venturi Mask and Transtracheal Oxygen
Venturi Mask
The Venturi mask, named after the Venturi effect, is designed to deliver precise oxygen concentrations. It consists of a large tube with an oxygen inlet that narrows down, causing a pressure drop that pulls air in through adjustable side ports. The mask is a lightweight,...