Related Experiment Video
Updated: Oct 9, 2026


Analysis of Electrocardiograms and Behavior in Mice from Pregnancy to Lactation Period
Published on: April 5, 2024
Beta blockers and lactation: an update
M E Shannon1, S E Malecha, A J Cha
1Searle Pharmaceuticals, Skokie, Illinois, USA.

Insights
Beta-blockers are frequently used for heart conditions. This review examines the latest data on common beta-blockers, assessing their safety for breastfeeding mothers.
Area of Science:
- Pharmacology
- Cardiology
- Neonatal Medicine
Background:
- Beta-adrenergic antagonists (beta-blockers) are a cornerstone in managing hypertension, angina pectoris, arrhythmias, and post-myocardial infarction mortality.
- The widespread use of beta-blockers raises concerns about potential exposure in lactating women and their infants.
Purpose of the Study:
- To review current data on the safety of commonly prescribed beta-blockers during lactation.
- To provide healthcare professionals with up-to-date information for managing hypertensive or cardiac conditions in breastfeeding women.
Main Methods:
- Literature review of recent studies and clinical data.
- Focus on specific beta-blocker agents: metoprolol, atenolol, propranolol, carvedilol, nadolol, sotalol, and betaxolol.
- Analysis of pharmacokinetic and pharmacodynamic properties relevant to lactation.
Main Results:
- Data on the transfer of specific beta-blockers into breast milk varies.
- Some agents show minimal infant exposure, while others require closer monitoring.
- Individual patient factors and dosage influence safety profiles.
Conclusions:
- Most common beta-blockers are generally considered compatible with breastfeeding, but careful consideration is needed.
- Individualized risk-benefit assessment is crucial for selecting beta-blockers in lactating women.
- Continued research is essential to refine safety guidelines for beta-blocker use during lactation.
Abstract:
Beta-adrenergic antagonists are one of the most commonly used class of agents in the treatment of hypertension. They have also demonstrated utility in the treatment of angina pectoris and certain arrhythmias and for the reduction in mortality following a myocardial infarction. The use of this class of agents creates the potential for beta-blocker exposure among lactating women. This review focuses on the most up-to-date data regarding the more common agents--metoprolol, atenolol, propranolol, carvedilol, nadolol, sotalol, and betaxolol--and their safety in lactating women.

Related Concept Videos
 01:31
Adrenergic Antagonists: ɑ and β-Receptor Blockers
 01:27
Adrenergic Antagonists: Pharmacological Actions of β-Receptor Blockers
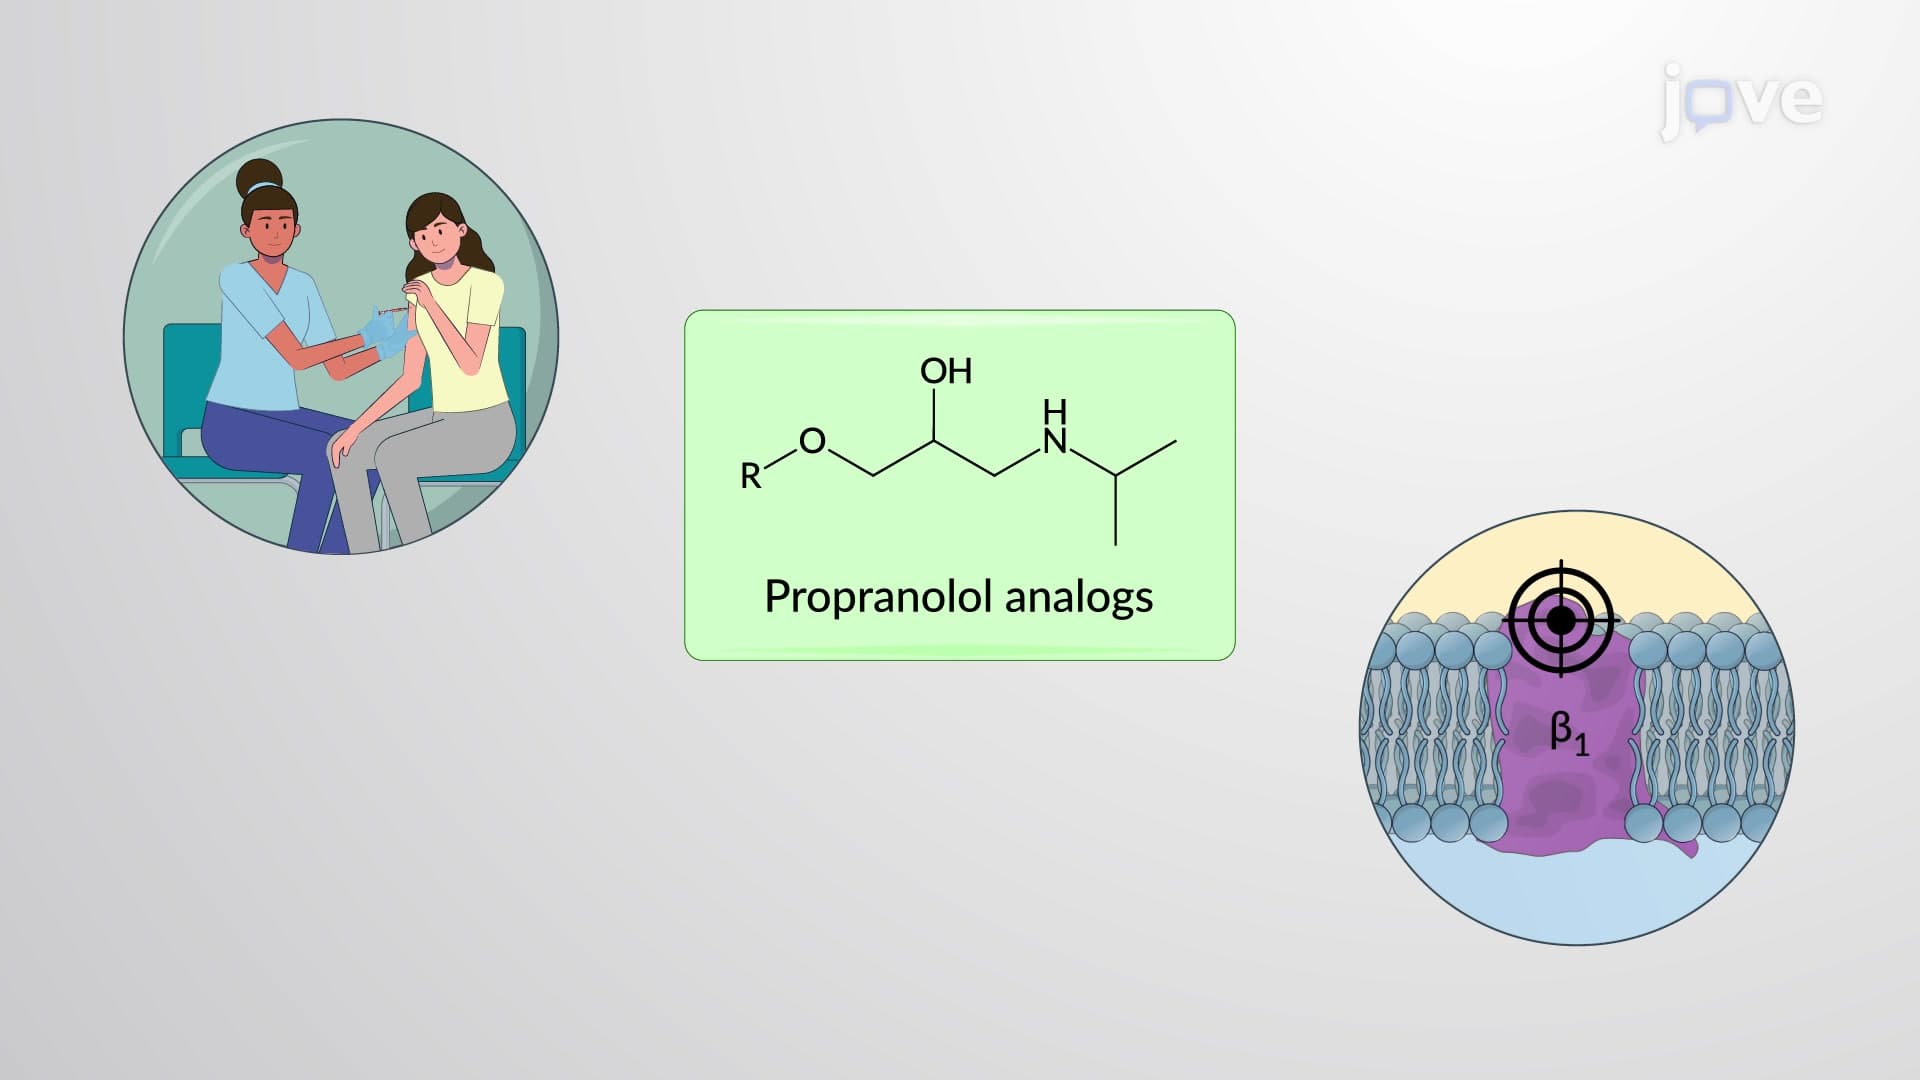 01:25
Adrenergic Antagonists: Chemistry and Classification of β-Receptor Blockers
 01:24
Antiarrhythmic Drugs: Class II Agents as β-Adrenergic Blockers
 01:28
Antihypertensive Drugs: Types of β-Blockers
 01:22
Heart Failure Drugs: β-Blockers