Related Experiment Video
Updated: Aug 14, 2026

Sodium Taurocholate Induced Severe Acute Pancreatitis in C57BL/6 Mice
Published on: June 28, 2021
Procalcitonin, soluble interleukin-2 receptor, and soluble E-selectin in predicting the severity of acute
M L Kylänpää-Bäck1, A Takala, E A Kemppainen
1Department of Surgery, Helsinki University Central Hospital, Finland.

Objective:
To investigate whether marker(s) of systemic inflammation detect, at an early stage of acute pancreatitis, patients who may ultimately develop severe disease.
Design:
Prospective study.
Setting:
University hospital emergency unit.
Patients:
Thirty patients with mild acute pancreatitis (SEV0 group) and 27 with severe acute pancreatitis. Of the latter, 11 did not develop organ failure (SEV1 group), whereas the other 16 patients developed acute respiratory failure and 9 of them also developed renal failure (SEV2 group).
Interventions:
Blood samples were collected at admission to the hospital (T0), and at 12 hrs (T12) and 24 hrs (T24 after admission.
Measurements And Main Results:
The plasma concentrations of procalcitonin (PCT), soluble E-selectin (sE-selectin), soluble interleukin-2 receptor (sIL-2R), and the serum concentration of C-reactive protein (CRP) were monitored. PCT levels at T0 were significantly higher in the SEV1 group (median 0.4 ng/mL, range 0.2-2.3) and the SEV2 group (0.8 ng/mL, 0.2-73.5) than in the SEV0 group (0.3 ng/mL, 0.1-3, p < .05 and p < .001, respectively). At T12, PCT level in the SEV2 group was significantly higher than that in the SEV1 group (2.2 ng/mL, 0.2-86.6 vs. 0.4 ng/mL, 0.3-2.8, p = .05), as it also was at T24 (2.2 ng/mL, 0.4-73.3 vs. 0.5 ng/mL, 0.3-4, p < .01). Among SEV2 patients, PCT concentration correlated negatively with the time elapsed between admission and the diagnosis of organ failure. At T12, sIL-2R levels of the SEV1 group (1,011 U/mL, range 334-2,211) and the SEV2 group (1,495 U/ml, range 514-4,526) both differed significantly from the SEV0 group (636 U/ml, range 356-1,678, p < .05 and p < .001, respectively) as they also did at T24. Although CRP level in the SEV1 group at T12 did not differ from the SEV0 group, the difference between SEV2 (272 microg/mL, range 46-462) and SEV0 was significant (53 microg/mL, range 5-243, p < 0.01). sE-selectin levels did not differ between groups.
Conclusions:
At admission to hospital, concentrations of PCT, but not those of CRP, sE-selectin, or sIL-2R, are higher in patients with severe acute pancreatitis than in patients with mild pancreatitis. PCT test had sensitivity of 94% and specificity of 73% for development of organ failure. PCT may be useful to identify the patients who benefit from novel therapies aimed at modifying the course of systemic inflammation.
More Related Videos
 07:10
Establishment of a Mouse Severe Acute Pancreatitis Model using Retrograde Injection of Sodium Taurocholate into the Biliopancreatic Duct
Published on: April 1, 2022
 07:38
Preparing a Mice Model of Severe Acute Pancreatitis via a Combination of Caerulein and Lipopolysaccharide Intraperitoneal Injection
Published on: May 10, 2024
Related Concept Videos
 01:27
Acute Pancreatitis I: Introduction
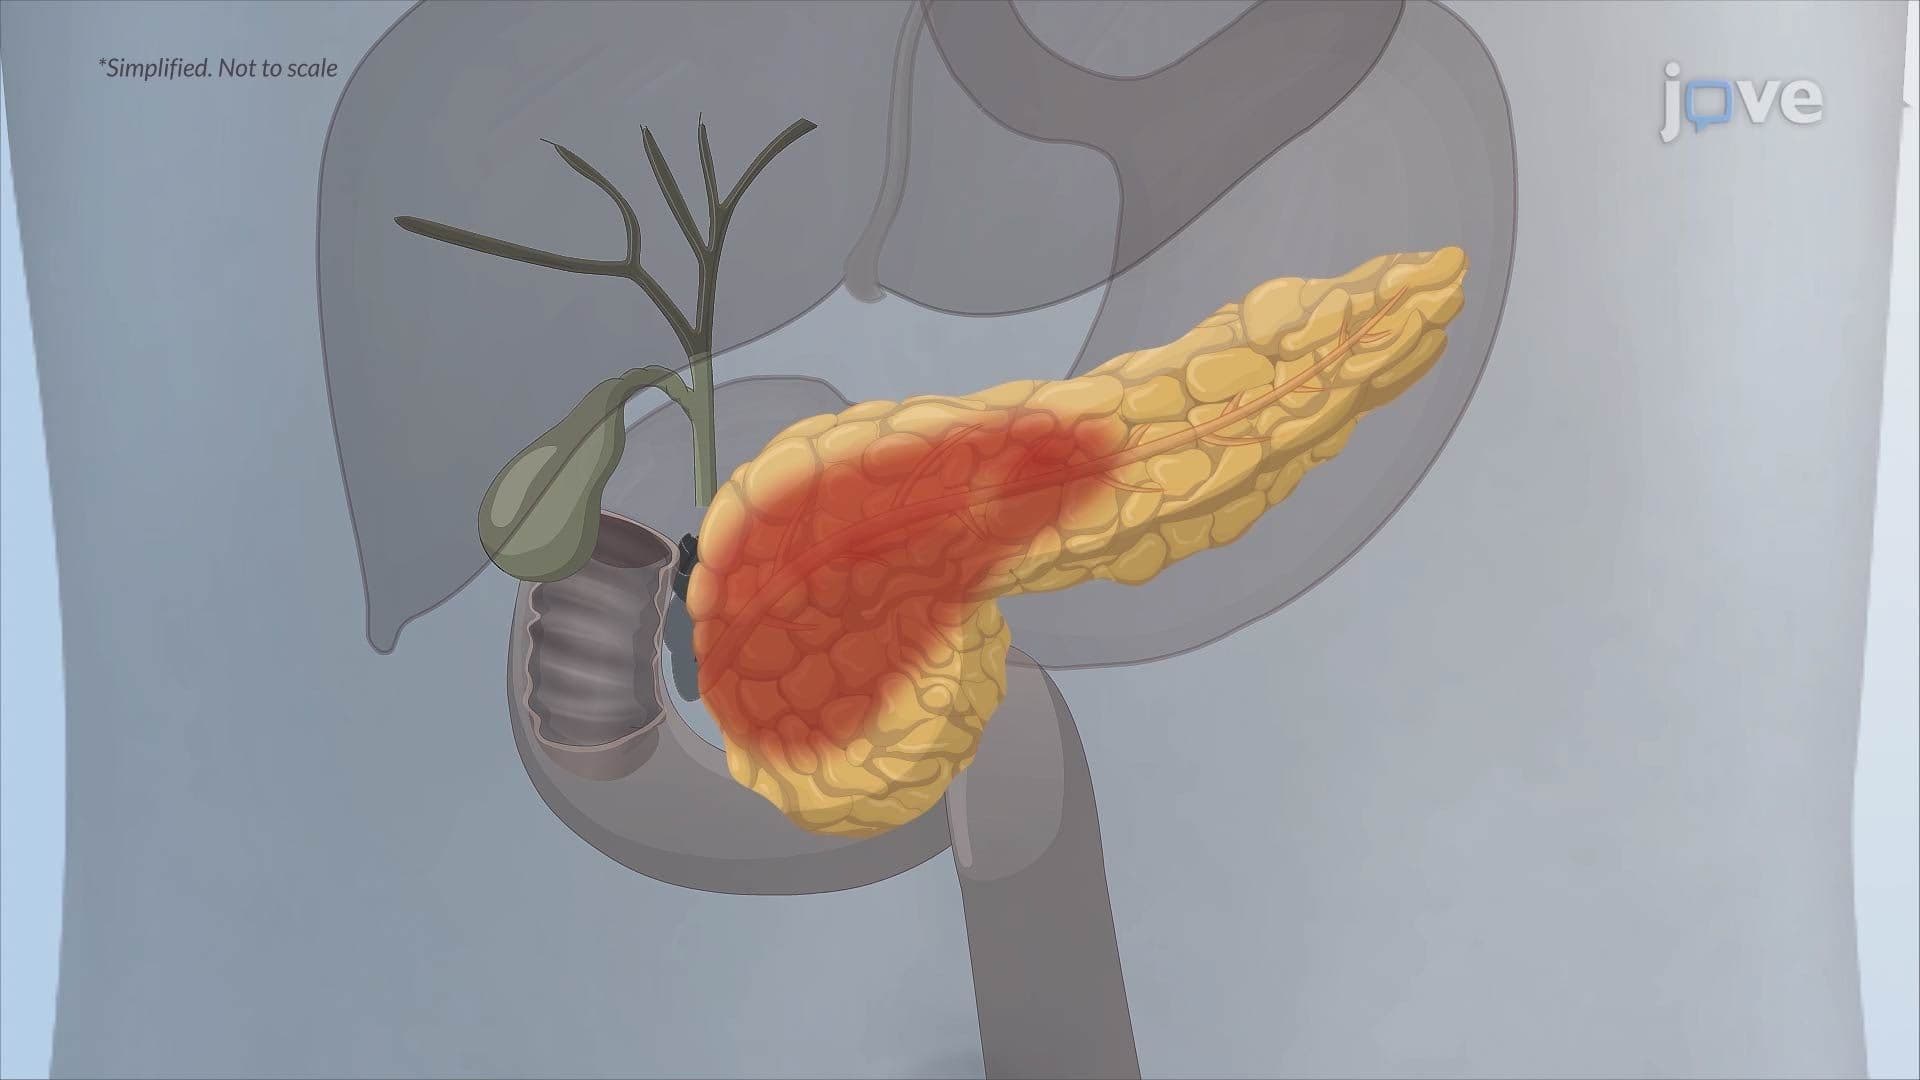
Acute pancreatitis is characterized by rapid inflammation of the pancreas, often caused by factors like gallstone blockage or excessive alcohol consumption. Chronic pancreatitis, on the other hand, is a slow, progressive inflammation that may result from long-term alcohol abuse, obstructions in the pancreatic duct, or genetic factors.
The causes of acute pancreatitis include:
 01:30
Acute Pancreatitis II: Clinical Manifestations and Management
 01:29
Chronic Pancreatitis II: Collaborative Care
Assessment:
 01:25
Acute Pancreatitis I: Introduction
 01:21
Acute Pancreatitis II: Pathophysiology
 01:25
Chronic Pancreatitis I: Introduction