Related Experiment Video
Updated: Oct 9, 2026
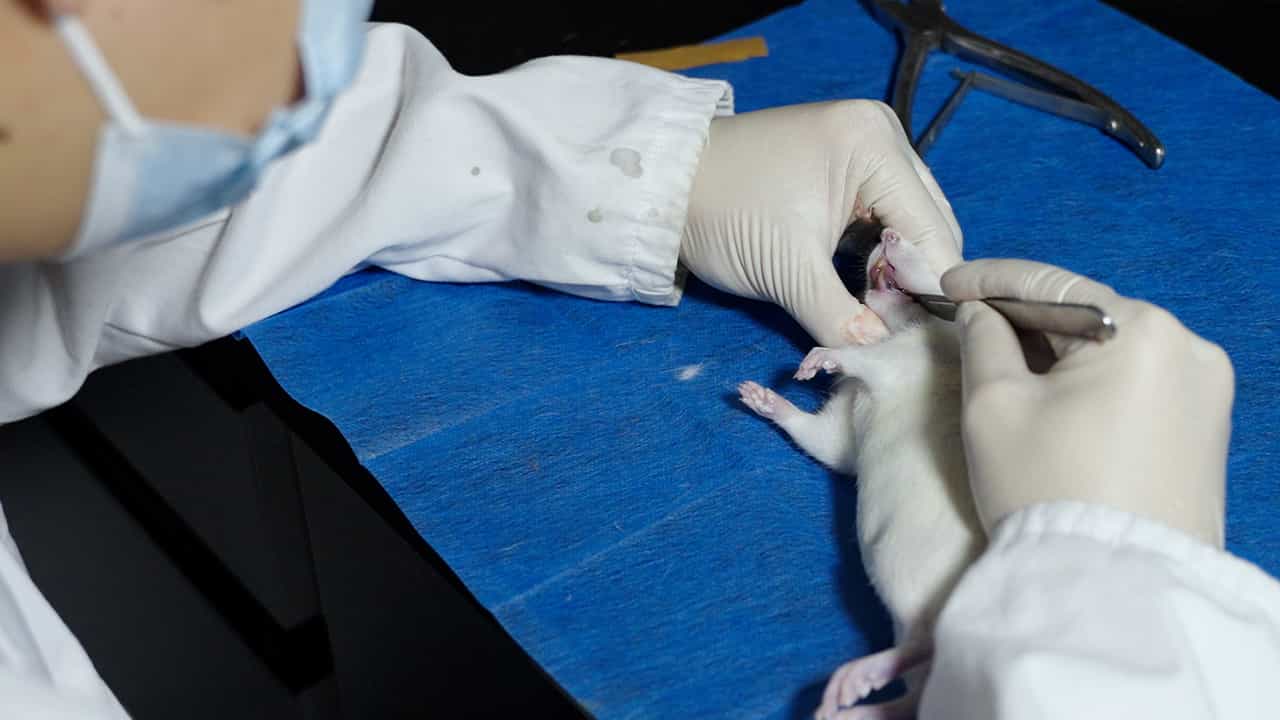
Immunofluorescent Labeling in Nasal Mucosa Tissue Sections of Allergic Rhinitis Rats via Multicolor Immunoassay
Published on: September 22, 2023
Allergic rhinitis update: Epidemiology and natural history
J A Bellanti1, D B Wallerstedt
1Departments of Pediatrics and Microbiology-Immunology and the International Center for Interdisciplinary Studies of Immunology, Georgetown University Medical Center, Washington, DC, USA.

Abstract:
Allergic rhinitis is the most common chronic condition, with an estimated prevalence in the United States of 5-22%, which increases from infancy, peaks in childhood and adolescence, and decreases in the elderly. As a major cause of morbidity, absenteeism, and restricted activity in both children and adults, allergic rhinitis, similar to asthma, appears to be increasing with time. Allergic rhinitis is commonly defined as seasonal or perennial, depending upon whether symptoms are manifested at defined yearly intervals or throughout the year, respectively. While trees, grasses, weeds, and molds are the most frequent causes of seasonal allergic rhinitis, dust mites and molds are the major contributors to perennial allergic rhinitis. The pathogenesis of allergic rhinitis is based upon interactions of allergen with membrane-bound allergen-specific IgE on the surface of mediator cells, i.e., basophils and mast cells, leading to the release of allergic mediators (both performed and newly synthesized) including histamine, leukotrienes, and eosinophil cationic protein (ECP). These are responsible for both immediate allergic responses characteristic of acute allergic rhinitis and the late inflammatory reactions responsible for chronic allergic rhinitis. The evaluation of rhinitis should include a detailed patient history, a careful physical examination, and appropriate diagnostic tests including skin prick tests or serum assays for allergen-specific IgE. Seasonal allergic rhinitis is readily distinguished from perennial allergic rhinitis by history and confirmed by positive skin tests to causative aeroallergens. It is important to differentiate seasonal rhinitis from non-allergic disorders including infectious rhinitis, structural or anatomic problems such as nasal polyps or septal deviation, rhinitis medicamentosa (due to the overuse of topical vasoconstrictors), hormonal rhinopathy (e.g., pregnancy, hypothyroidism), non-allergic vasomotor rhinopathy, non-allergic inflammatory rhinitis with eosinophils (NARES), or rarely, a neoplasm. A knowledge of the epidemiologic and clinical presentation of allergic rhinitis together with these pathophysiologic mechanisms is essential for a modern-day diagnostic and therapeutic approach to the patient who suffers from allergic rhinitis.

Related Concept Videos
 01:28
Asthma I: Introduction
 02:06
Allergic Reactions
 01:20
Asthma: Pathogenesis and Management
Asthma is classified as allergic and non-allergic. Allergens such as dust mites, pollen, and pet dander trigger allergic asthma, while factors like cold air, intense emotions, or exercise can induce non-allergic asthma.
 01:30
Allergic Reactions: Anaphylaxis
 01:29
Asthma-I: Introduction
 01:26
Asthma-II: Pathophysiology and Classification
Additionally, environmental and genetic factors play crucial roles in determining an individual's susceptibility to asthma and the severity of their condition.
Critical processes in asthma pathophysiology include: