Related Experiment Video
Updated: Aug 14, 2026
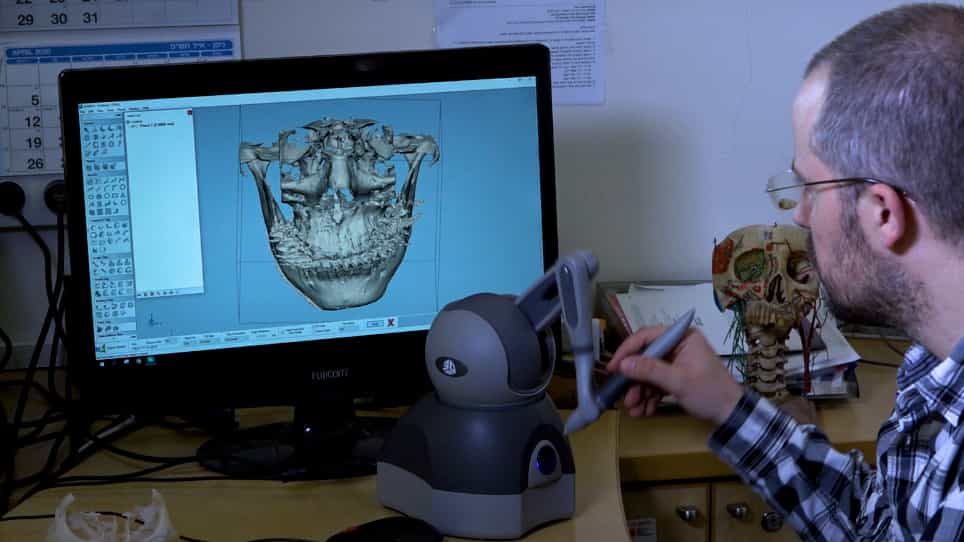
Treatment of Facial Deformities using 3D Planning and Printing of Patient-Specific Implants
Published on: May 23, 2020
Update on craniofacial surgery: the differential diagnosis of lambdoid synostosis/posterior plagiocephaly
R G Ellenbogen1, J S Gruss, M L Cunningham
1Division of Pediatric Neurological Surgery, Seattle Children's Hospital and Regional Medical Center, Seattle, Washington, USA.

Abstract:
There has been an evolution of thought on the diagnosis and treatment of posterior plagiocephaly. Synostotic posterior plagiocephaly (lambdoid synostosis) can be diagnosed and differentiated from non-synostotic posterior plagiocephaly (positional molding) based on specific cosmetic and radiologic criteria. The advent of high-resolution three-dimensional CT analysis of cranial morphology combined with meticulous clinical studies of the two major causes of posterior plagiocephaly has added much to our understanding of this skull deformity. Children with lambdoid synostosis have a trapezoid-shaped skull with posterior displacement of their ipsilateral ear, ipsilateral mastoid bossing, contralateral occipital bossing, and a fused lambdoid suture that appears as a ridge. Children with posterior plagiocephaly without lambdoid synostosis have a characteristic parallelogram-shaped skull with anterior displacement of the ipsilateral ear and ipsilateral frontal bossing. This subject is surrounded in controversy because many of the children in the past thought to have lambdoid synostosis probably did not, based in part on the aforementioned specific criteria. This is an important point, as most patients with posterior plagiocephaly without synostosis will improve without surgery. One should thus be appropriately conservative in the selection of patients for surgery. The majority of infants evaluated at craniofacial clinics presumably have posterior plagiocephaly without synostosis and can be successfully treated with frequent head turning, helmet, or band therapy. Patients with clinically and radiologically proven synostotic posterior plagiocephaly and a severe deformity should undergo craniofacial surgery. The technique of biparieto-occipital craniotomy is safe, simple, and delivers a good cosmetic result. Our postoperative photographic evaluations have shown an immediate, aesthetically pleasing change in the contour of the occiput, which tends to improve with time.
More Related Videos
 10:23
Three-Dimensional Cephalometric Landmark Annotation Demonstration on Human Cone Beam Computed Tomography Scans
Published on: September 8, 2023
 08:03
Midface Hypoplasia and Cranial Base Morphology in Syndromic Craniosynostosis: A Comparative Analysis Study Using a Predictive Regression Model
Published on: November 4, 2025
Related Concept Videos
 01:14
Cranial Bones: Superior and Posterior View
The frontal bone is the single bone that forms the forehead. At its anterior midline, between the eyebrows, there is a slight depression called the glabella. The frontal bone also forms the supraorbital margin of the orbit. Near the middle of this margin is the supraorbital foramen, the opening that provides passage for a sensory nerve to the forehead. The frontal bone is thickened just above each supraorbital margin,...
 01:27
Cranial Bones: Lateral View
The temporal bone forms the lower lateral side of the skull. The temporal bone is subdivided into several regions. The flattened upper portion is the squamous portion of the temporal bone. Below this area and projecting anteriorly is the zygomatic process of the temporal bone, which forms the posterior portion of the zygomatic arch. Posteriorly is the mastoid portion of the temporal bone. Projecting...