Related Experiment Video
Updated: Aug 15, 2026


Isolation of Leukocytes from the Human Maternal-fetal Interface
Published on: May 21, 2015
Corticosteroid-binding globulin status at the fetomaternal interface during human term pregnancy
C Benassayag1, I Souski, T M Mignot
1INSERM U.361, Maternité Port-Royal Cochin, Université René Descartes, 75014 Paris, France. u361@cochin.inserm.fr

The status of the corticosteroid-binding globulin (CBG) at the fetomaternal interface, especially in the maternal intervillous blood space (I), was investigated and compared to that of CBG in the maternal (M) and fetal (umbilical arteries [A] and vein [V]) peripheral circulations at term. Immunoquantitation of plasma CBG showed that the CBG concentration in I was 30% less than that in M (P < 0.001) and threefold higher than that in umbilical cord blood (P < 0.001). The microheterogeneity of CBG studied by immunoaffinoelectrophoresis in the presence of concanavalin A and Western blotting indicated that the CBG in I was mainly of maternal origin and different from fetal CBG. A CBG mRNA, but no classic 50- to 59-kDa CBG, was found in isolated term trophoblastic cells. The steroid environment of the CBG in I differed greatly from that in the peripheral maternal and fetal circulations, because the progesterone:cortisol molar ratio in I was 75-fold higher than that in M and 7- to 10-fold higher than that in the fetal circulation. Binding studies revealed that the affinity constants of CBG for cortisol in I, A, and V were significantly lower than that in M plasma (P < 0.02) in their respective hormonal contexts. The binding parameters for I-CBG stripped of endogenous steroids and lipids were close to those for M-CBG but different from those of fetal CBG (P < 0.001). These data reflect the physiological relevance of the CBG-steroid interaction, especially with very CBG-loaded progesterone at the fetomaternal interface during late pregnancy.
The status of the corticosteroid-binding globulin (CBG) at the fetomaternal interface, especially in the maternal intervillous blood space (I), was investigated and compared to that of CBG in the maternal (M) and fetal (umbilical arteries [A] and vein [V]) peripheral circulations at term. Immunoquantitation of plasma CBG showed that the CBG concentration in I was 30% less than that in M (P < 0.001) and threefold higher than that in umbilical cord blood (P < 0.001). The microheterogeneity of CBG studied by immunoaffinoelectrophoresis in the presence of concanavalin A and Western blotting indicated that the CBG in I was mainly of maternal origin and different from fetal CBG. A CBG mRNA, but no classic 50- to 59-kDa CBG, was found in isolated term trophoblastic cells. The steroid environment of the CBG in I differed greatly from that in the peripheral maternal and fetal circulations, because the progesterone:cortisol molar ratio in I was 75-fold higher than that in M and 7- to 10-fold higher than that in the fetal circulation. Binding studies revealed that the affinity constants of CBG for cortisol in I, A, and V were significantly lower than that in M plasma (P < 0.02) in their respective hormonal contexts. The binding parameters for I-CBG stripped of endogenous steroids and lipids were close to those for M-CBG but different from those of fetal CBG (P < 0.001). These data reflect the physiological relevance of the CBG-steroid interaction, especially with very CBG-loaded progesterone at the fetomaternal interface during late pregnancy.
Related Concept Videos
 01:15
Transcytosis of IgG
IgG molecules from a mother undergo transcytosis starting around 13 weeks of gestation. The amount of IgG transferred and entering the fetal blood circulation increases with...
 01:21
Drug Distribution: Tissue Binding
For...
 01:29
Drug Distribution: Plasma Protein Binding
 01:25
Physiological Barriers
The blood endothelial barrier is the most porous of these. It allows all small ionized, un-ionized, and lipophilic molecules to pass through the endothelial lining into the interstitial space...
 01:30
Drug Binding to Blood Components
HSA is the most abundant plasma protein and is vital in drug binding. It contains distinct drug-binding sites, with different drugs exhibiting affinity for specific sites. There are three main drug-binding domains for HSA: sites I, II, and III. These domains are further...
 01:09
Hepatic Drug Clearance: Effect of Protein Binding
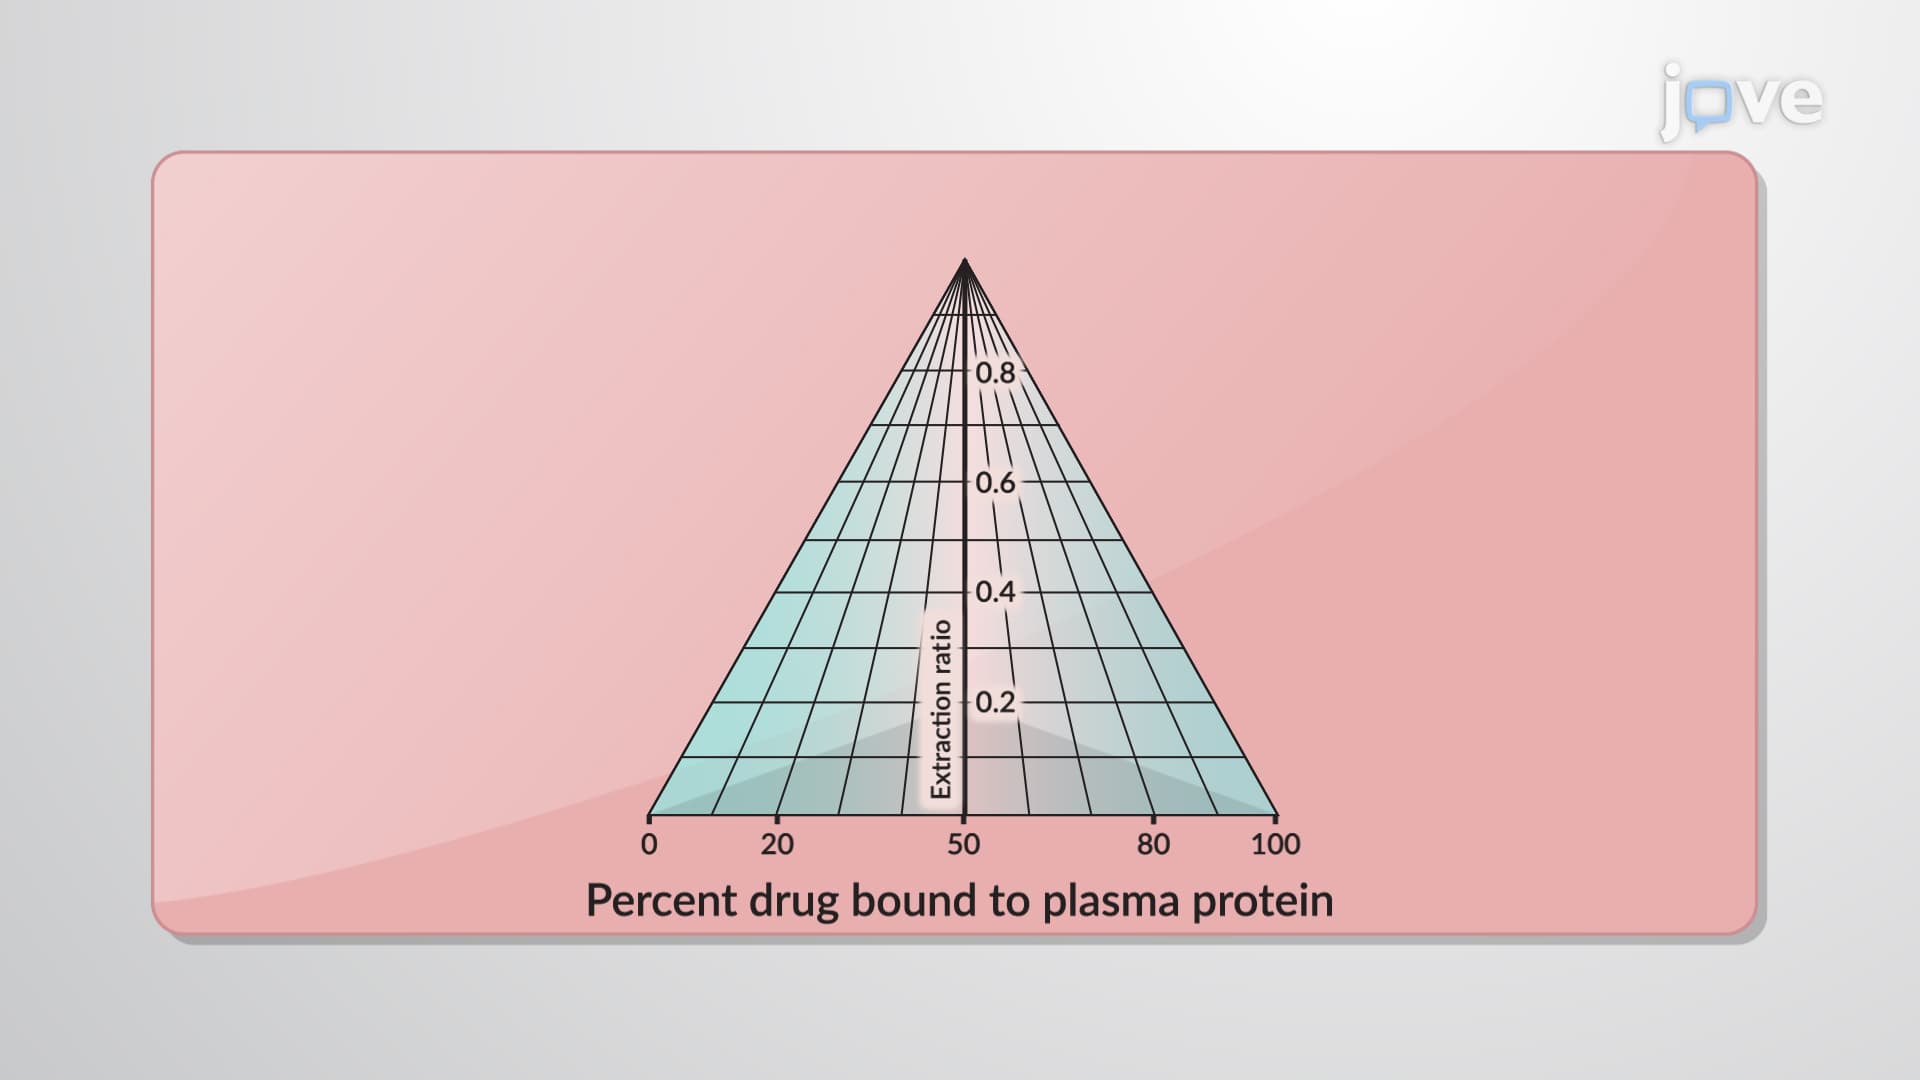
For low-extraction-ratio drugs that are less than 80% protein-bound, minor changes in protein binding...