Related Experiment Video
Updated: Aug 10, 2026

A Novel Inhalation Mask System to Deliver High Concentrations of Nitric Oxide Gas in Spontaneously Breathing Subjects
Published on: May 4, 2021
What intervals in oral therapy of isosorbide dinitrate in various doses are sufficient to prevent nitrate tolerance?
M Kośmicki1, Z Sadowski, H Szwed
1Department of Ischaemic Heart Diseases, National Institute of Cardiology, ul. Spartańska 1, 02-637 Warsaw, Poland.

Introductions:
The organic nitrates are effective anti-anginal drugs during initial treatment, but their therapeutic value is compromised by the rapid development of tolerance during sustained therapy. The only widely accepted method of preventing tolerance is the use of intermittent administration, but without specifying to what extent the length of interval is dependent on type and dose of nitrate. The aim of this study was to evaluate how long periods free of nitrates are sufficient to prevent tolerance in long-term therapy with oral sustained-release isosorbide dinitrate (ISDN).
Material And Methods:
In a double-blind study, 38 patients with stable angina, received ISDN: 40 mg, 80 mg and 120 mg or placebo in the first ingestion (1st) and in long-term therapy in four 7 day phases: 4-times-daily (4x), 3-times-daily (3x) with 12 h nitrate-free interval, twice-daily (2x) with 18 h interval and once-daily (1x). After 1st and on the last day of each long-term phases, exercise tests with the analysis of walking times: total, to angina and to ischaemia (WTI) were performed: preceding ingestion, 2 h and 6 h after.
Results:
Six hours after 1st all doses WTI improved significantly in comparison to placebo (p < 0.0001): 40 mg by 52.5%, 80 mg by 66.0% and 120 mg by 58.4%. None of the ISDN doses improved significantly WTI in 4x phase; in 3x, only 40 mg by 12.1% (p < 0.05); in 2x, only 80 mg by 22.3% (p < 0.05) and in once-daily, 80 mg by 27.2% and 120 mg by 36.2% (p < 0.01).
Conclusion:
12 h nitrate-free interval is sufficient in order to prevent tolerance in long-term treatment of sustained-release ISDN with 40 mg dose, 18 h with 80 mg and 24 h with 120 mg doses.
Insights
To prevent tolerance to oral sustained-release isosorbide dinitrate (ISDN), intermittent dosing is key. Nitrate-free intervals of 12, 18, or 24 hours are sufficient for 40, 80, and 120 mg doses, respectively.
Area of Science:
- Cardiology
- Pharmacology
Background:
- Organic nitrates are effective anti-anginal drugs but tolerance limits long-term use.
- Intermittent nitrate administration is the primary strategy to prevent tolerance.
- Optimal nitrate-free interval duration for sustained-release isosorbide dinitrate (ISDN) remains unclear.
Purpose of the Study:
- To determine sufficient nitrate-free interval durations to prevent tolerance.
- To evaluate long-term oral sustained-release ISDN therapy efficacy.
- To assess the impact of varying ISDN doses on tolerance development.
Main Methods:
- Double-blind study involving 38 stable angina patients.
- Patients received ISDN (40, 80, 120 mg) or placebo in phases with varying daily frequencies and nitrate-free intervals (12, 18, 24 hours).
- Exercise tests analyzed walking times to angina and ischemia (WTI) pre- and post-ingestion.
Main Results:
- Initial ISDN doses significantly improved WTI compared to placebo.
- No significant WTI improvement was observed with 4x daily dosing, indicating tolerance.
- Intermittent dosing (3x, 2x, 1x daily) showed dose-dependent WTI improvements, with longer intervals yielding better results.
Conclusions:
- A 12-hour nitrate-free interval prevents tolerance for 40 mg ISDN.
- An 18-hour interval is sufficient for 80 mg ISDN to prevent tolerance.
- A 24-hour nitrate-free interval is required for 120 mg ISDN to prevent tolerance.

Related Concept Videos
 01:23
Antihypertensive Drugs: Vasodilators
 01:16
Antianginal Drugs: Nitrates and β-Blockers
Organic nitrates, such as nitroglycerin, play a pivotal role. Once metabolized, they liberate nitric oxide, a molecular marvel. Nitric oxide triggers guanylyl cyclase and augments cGMP production. This biochemical cascade orchestrates the relaxation of vascular smooth muscles, ushering in vasodilation and enhancing coronary blood flow. Administered...
 01:28
Treatment for Pulmonary Arterial Hypertension: Phosphodiesterase Inhibitors
Among the PDE5 inhibitors, sildenafil (Revatio) stands out as a competitive and selective inhibitor. It operates by elevating cellular levels of cGMP and augmenting signaling through the cGMP-PKG pathway, promoting vasodilation. Upon oral...
 01:18
Drug Delivery: Enteral Route
Drugs in...
 01:25
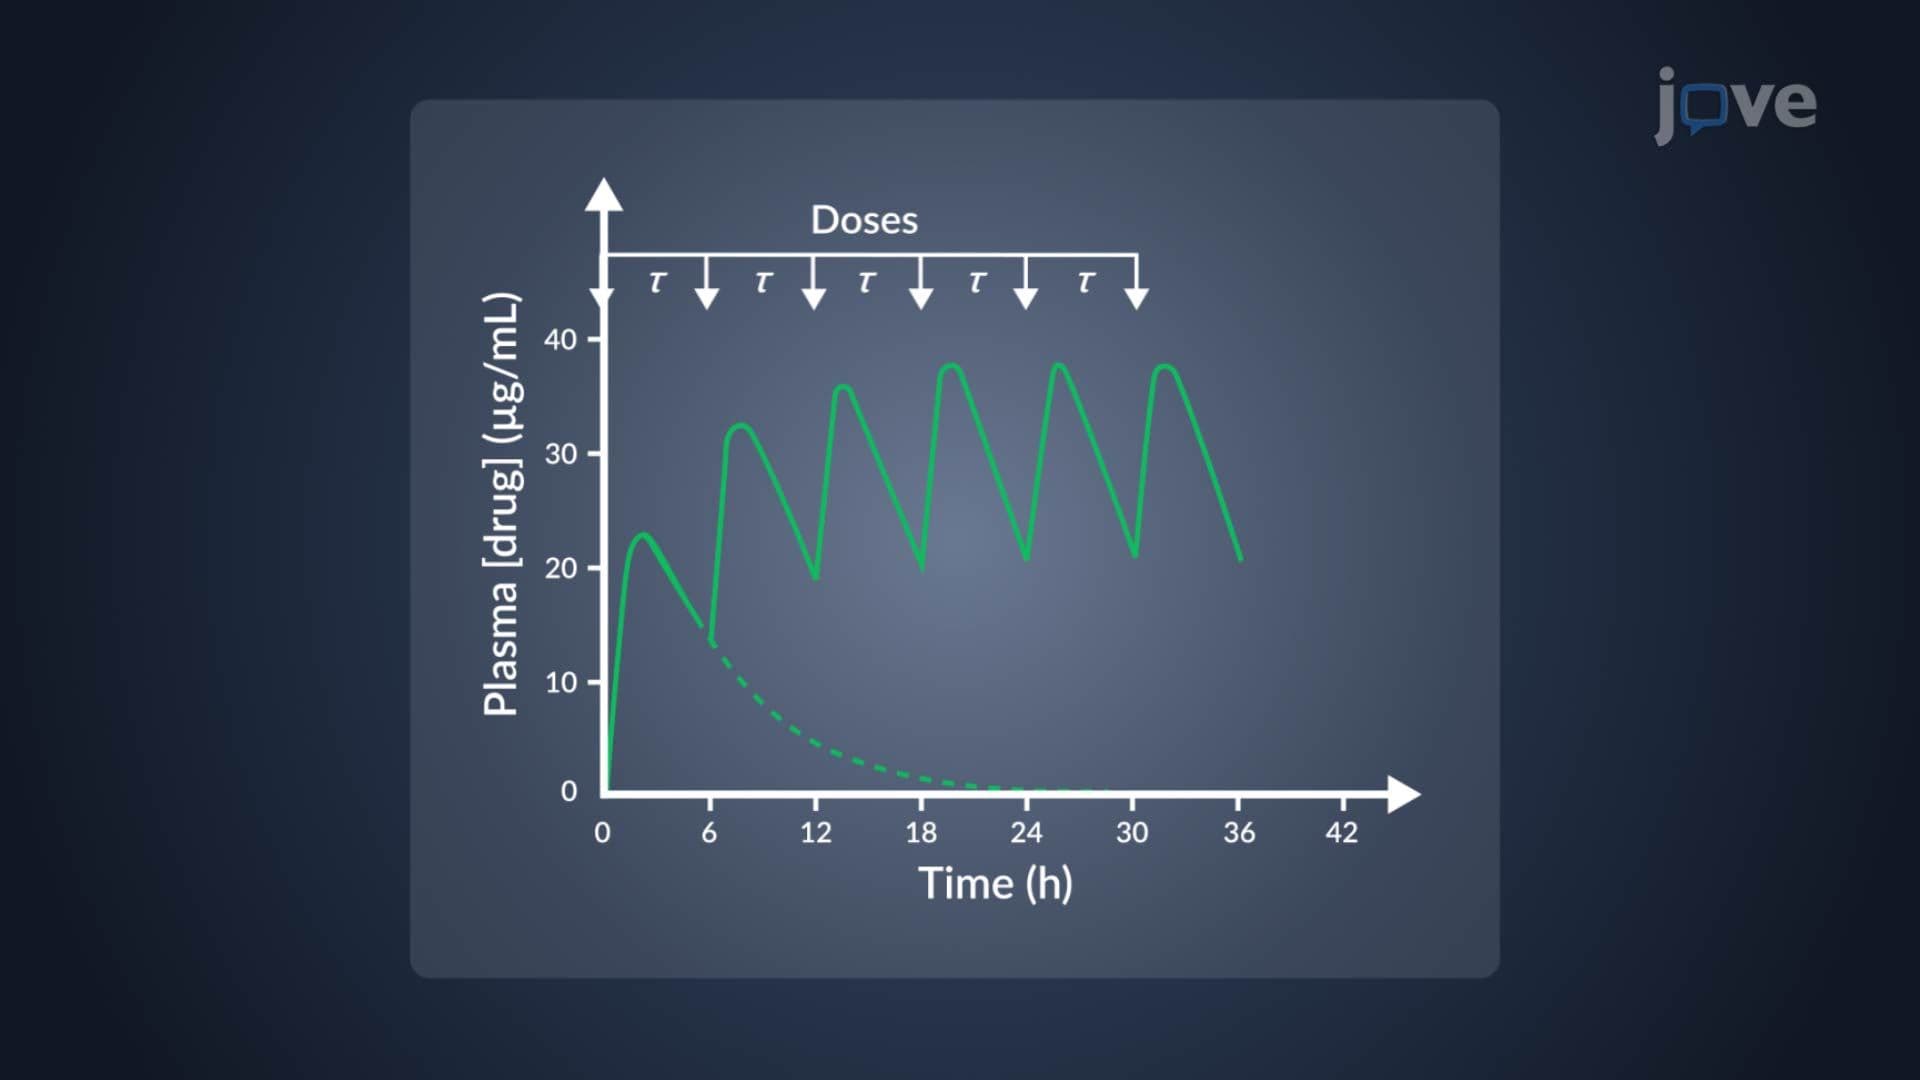
Dosage Regimen: Multiple Oral Dosage
 01:28
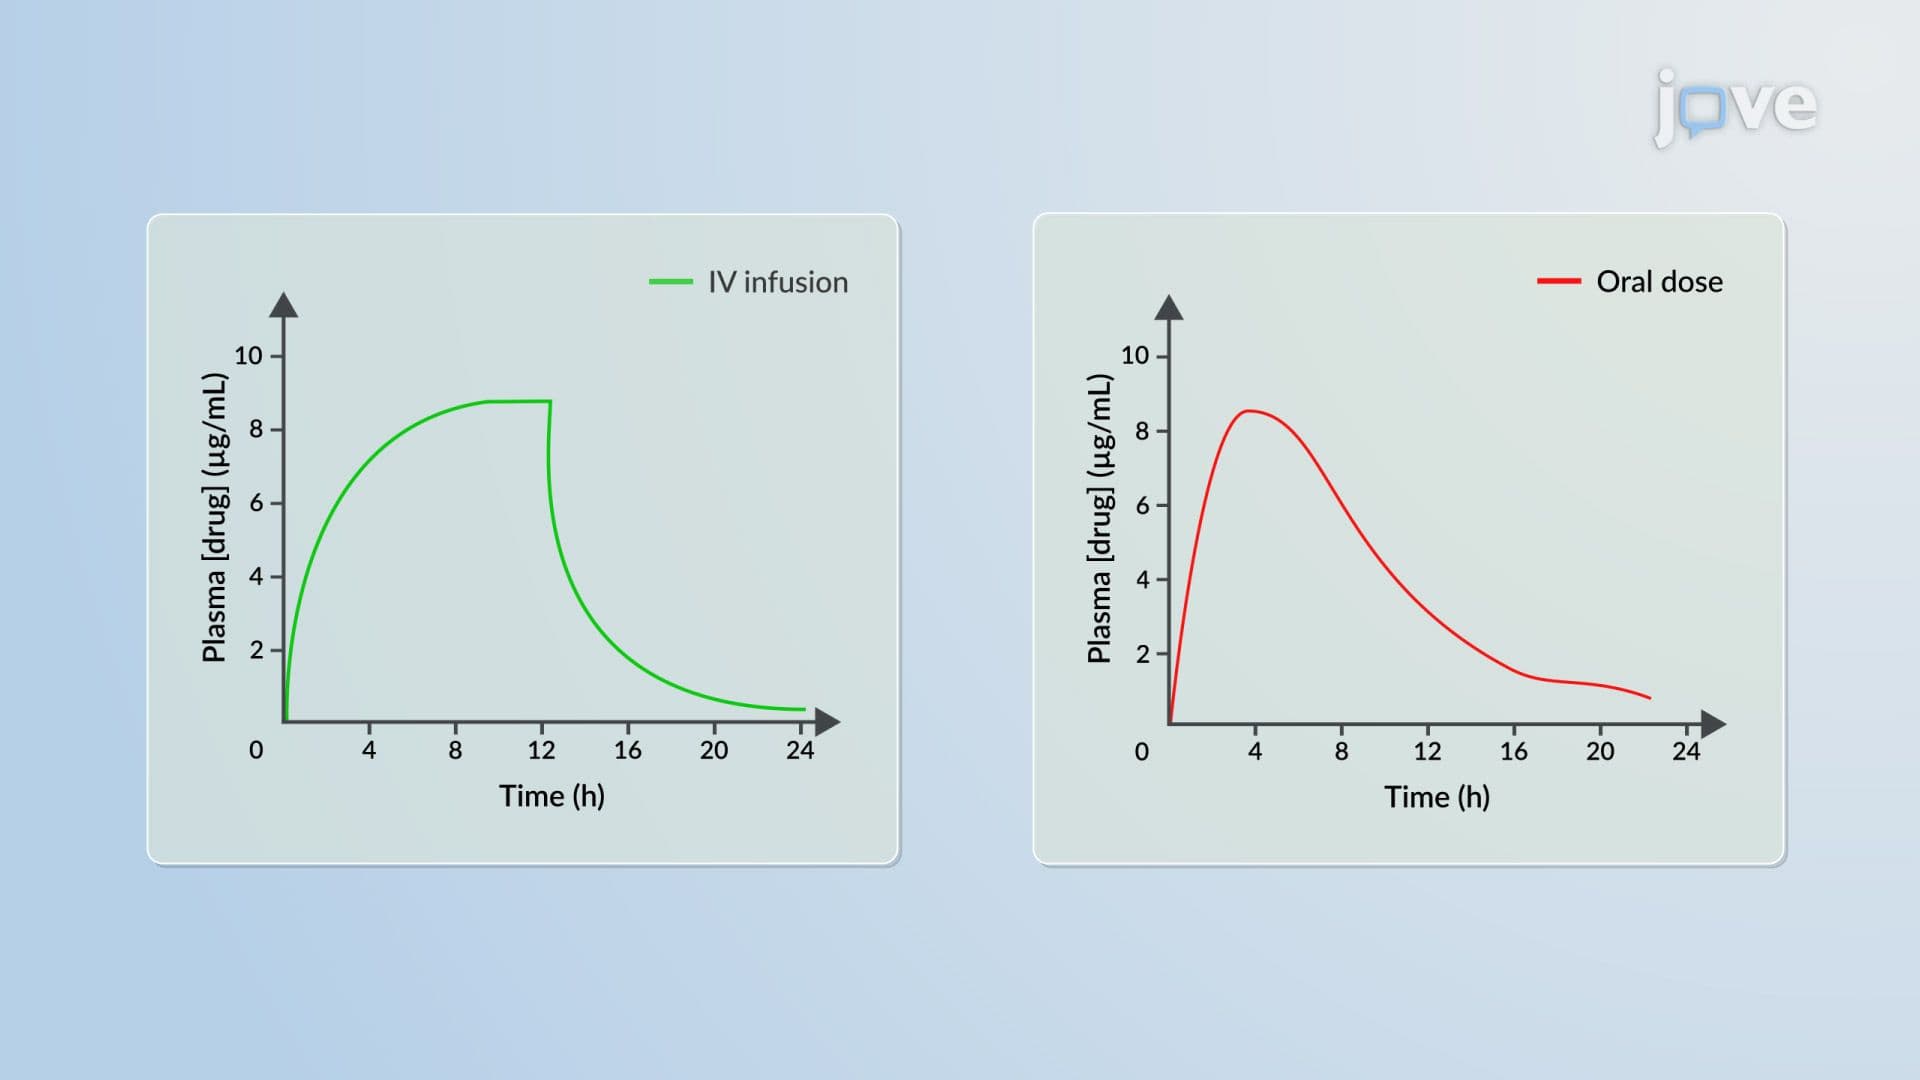
IV Infusion to Oral Dosing: Conversion Methods