Related Experiment Video
Updated: Aug 13, 2026

Scanning Skeletal Remains for Bone Mineral Density in Forensic Contexts
Published on: January 29, 2018
An analysis of burst fractures of the spine in adolescents
1Division of Pediatric Orthopaedics, Children's Hospital of Eastern Ontario, University of Ottawa, Canada.

Abstract:
Burst fractures are less common in children than in adults because of the greater mobility and elasticity of the pediatric spine. Because of these spine characteristics, these fractures may behave differently in childhood than in adulthood. To try to address these differences, we reviewed our experience with 11 children (5 boys, 6 girls) treated for burst fractures. Average age at time of injury was 14.4 years. Follow-up averaged 9 years. All fractures were categorized using the Denis classification system for burst fractures. Three children had associated spinal cord injury. Five children were treated with nonoperative bedrest and casting; the other 6 children, who had the most severe burst fractures, were treated with posterior spinal fusion and instrumentation. Satisfactory functional results were found in 90% of the children at follow-up. Radiological evaluation at initial and follow-up examination showed that children treated operatively improved or maintained their fracture kyphosis (range, 12 degrees - 19 degrees). Anterior vertebral compression improved an average of 15% (range, 24%-39%). In the children treated nonoperatively, kyphosis progressed an average of 9 degrees (range, 15 degrees - 24 degrees), and anterior vertebral compression increased a further 8% (range, 36%-44%). Our results showed that (a) the children who sustained burst fractures tended to develop mild progressive angular deformity at the site of the fracture, (b) operative stabilization prevented further kyphotic deformity as well as decreased the length of hospitalization without contributing to further cord compromise, and (c) nonoperative treatment of burst fracture was a viable option in neurologically intact children, but progressive angular deformity occurred during the first year after the fracture.
More Related Videos
 04:19
Minimally Invasive Treatment for Thoracolumbar Burst Fracture Using Sagittal Alignment Screws and A Trauma Reduction Device
Published on: November 8, 2024
 07:12
Clinical Efficacy of an Innovative Multidimensional Traction Therapy in Moderate Adolescent Idiopathic Scoliosis
Published on: February 10, 2026
Related Concept Videos
 01:27
Fractures: Bone Repair
Minor fractures with no bone displacement are treated by immobilizing the fractured bone using a cast or splint. However, in the case of fractures with displaced bones, the broken bones are repositioned before immobilization to ensure successful healing without deformation and loss of function. The realignment of fractured bone ends is performed through a process called reduction. If the procedure...
 01:16
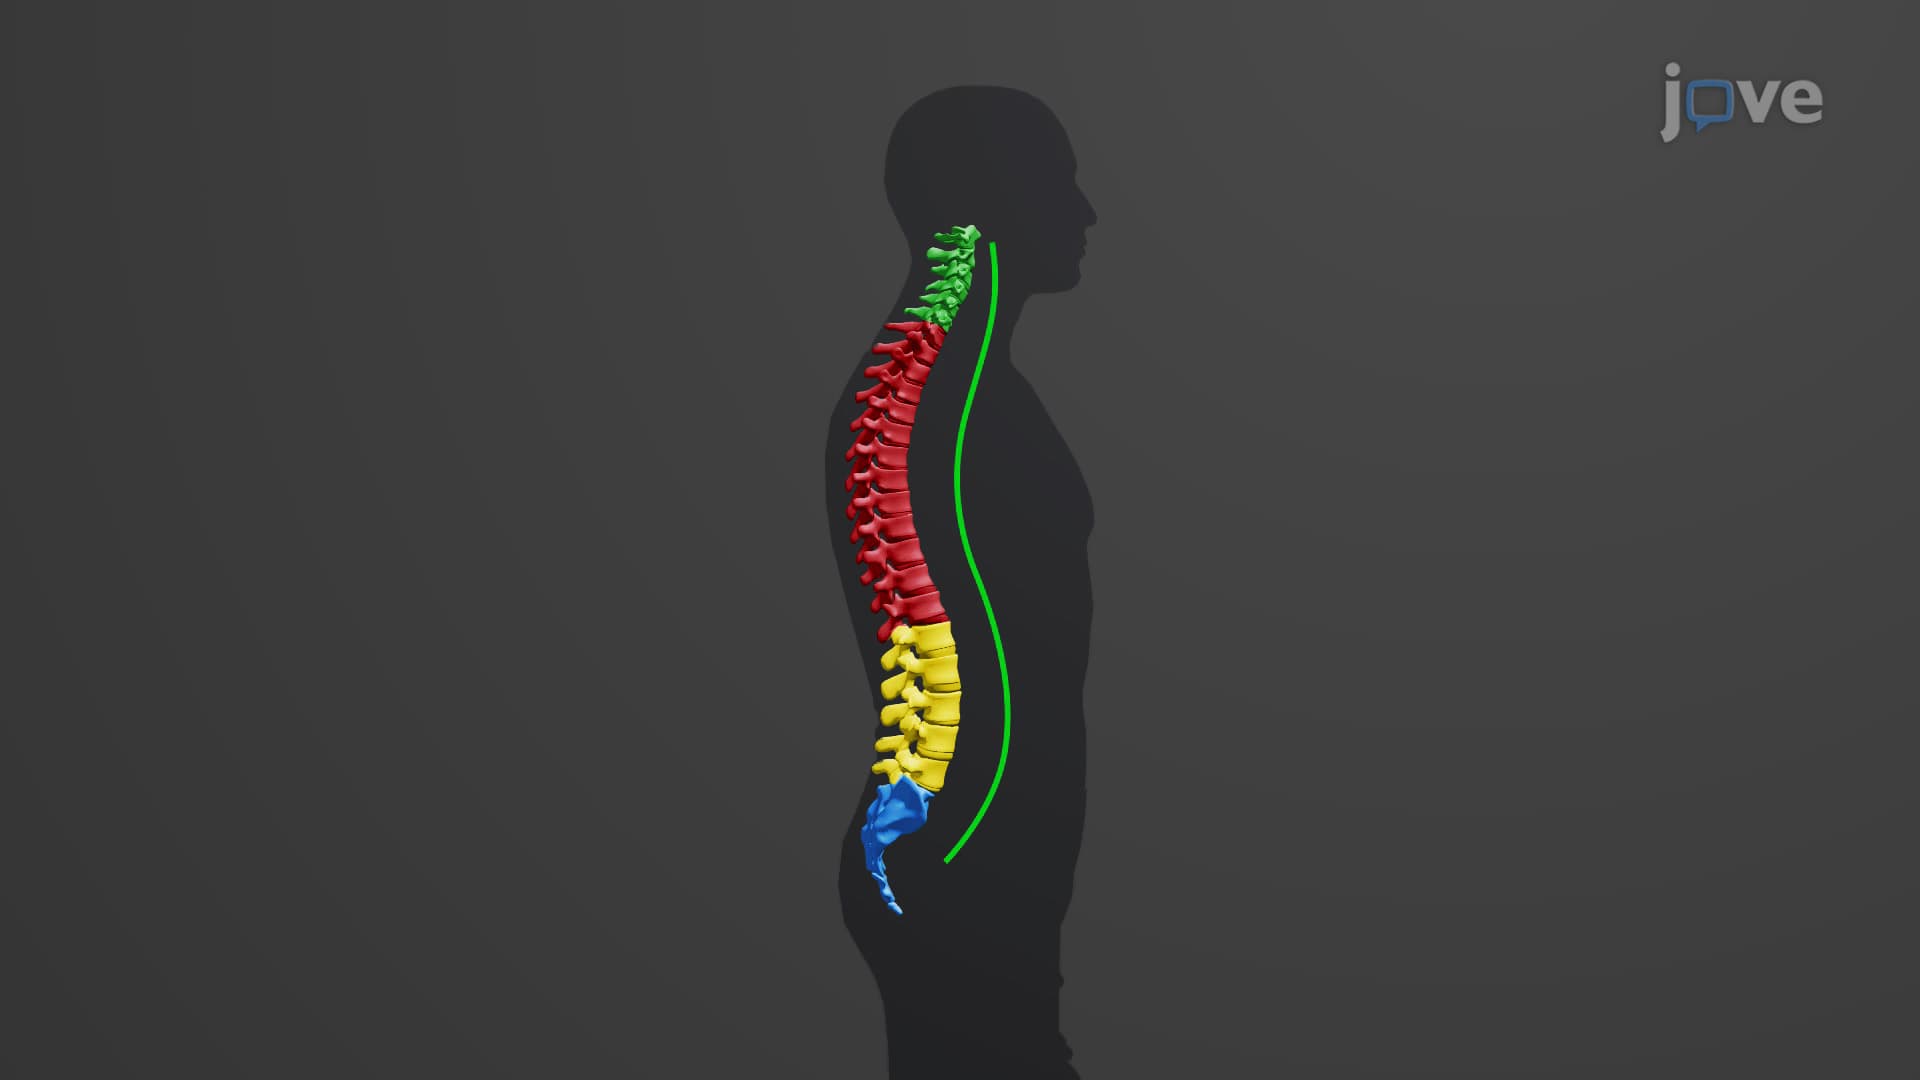
Vertebral Column: Regions and Curvature
Regions of the Vertebral Column
In an adult, the spine is subdivided into five regions: the cervical, the thoracic, the lumbar, the sacral, and the coccygeal region. The spine initially develops as a series of 33 vertebrae; after 20 years of age, the nine bones in the sacral region, five sacral, and four coccygeal bones fuse to form the...
 01:09
Changes in the Appendicular Skeleton with Age
Initially, the limb buds consist of a core of mesenchyme covered by a layer of ectoderm. The ectoderm at the end of the limb bud thickens to form a narrow crest called the apical ectodermal ridge. This ridge stimulates the underlying...
 01:24
Stress-Strain Diagram - Brittle Materials