Related Experiment Video
Updated: Oct 9, 2026

Surfactant Depletion Combined with Injurious Ventilation Results in a Reproducible Model of the Acute Respiratory Distress Syndrome (ARDS)
Published on: April 7, 2021
Low flow inflation pressure-time curve in patients with acute respiratory distress syndrome
E Kondili1, G Prinianakis, S Hoeing
1Department of Intensive Care, University Hospital of Heraklion, University of Crete, Greece.

Objective:
In mechanically ventilated patients with ARDS, determination of the lower (LIP) and upper (UIP) inflection points of the static pressure-volume curve (P-V) is crucial for planning ventilatory strategies. Recently, a simple new method was proposed for measuring the P-V curve by inflating the lung with constant low flow [14]. We hypothesized that during low flow inflation LIP and UIP might be determined using the pressure-time curve (P-T) instead of P-V.
Methods:
Eleven paralyzed patients with ARDS were studied. During volume control ventilation the patients were allowed to reach passive functional residual capacity (FRC) and then ventilator frequency, inspiratory to total breath duration ratio and tidal volume (VT) were set to 5 breaths/ min, 80% and 500 or 1,500 ml, respectively. With these settings, constant inspiratory flow (V'I) was administered for 9.6 s and ranged, depending on VT, between 0.05 and 0.15 l/s. P-V and P-T were obtained at two levels of positive end-expiratory pressure (PEEP; 0 and 10 cm H2O), with V'I being achieved either fast (< 0.1 s, minimum delay) or slowly (0.4 s, maximum delay).
Results:
With minimum flow delay for a given experimental condition, the shape of the P-T did not differ from that of P-V. In all cases P-T correctly identified the presence of LIP and UIP, which did not differ significantly between P-T and P-V. With maximum flow delay, compared to P-V, the initial part of P-T was significantly shifted to the left. P-T did not identify the presence of UIP and LIP in one and two cases, respectively.
Conclusions:
Provided that constant flow is given relatively fast, P-T accurately determines the shape of P-V, as well as the LIP and UIP. Flow delay causes a leftward shift of the initial part of P-T, masking the presence of LIP and UIP in some cases.
Related Concept Videos
 01:23
Acute Respiratory Failure-IV
 01:29
Acute Respiratory Failure-V
Ensure that patients are monitored continuously for their response to therapy, including changes in...
 01:21
Acute Respiratory Failure-I
Definition: It is defined by specific criteria based on blood gas measurements. Hypoxemia happens when the partial pressure of oxygen (PaO2) falls below 60 mmHg. At the same time,...
 01:24
Pulmonary Ventilation: Inhalation
Boyle's law becomes particularly pertinent when examining respiratory...
 01:21
Acute Respiratory Failure-II
The underlying physiological abnormalities that contribute to hypoxemic respiratory failure include:
 01:24
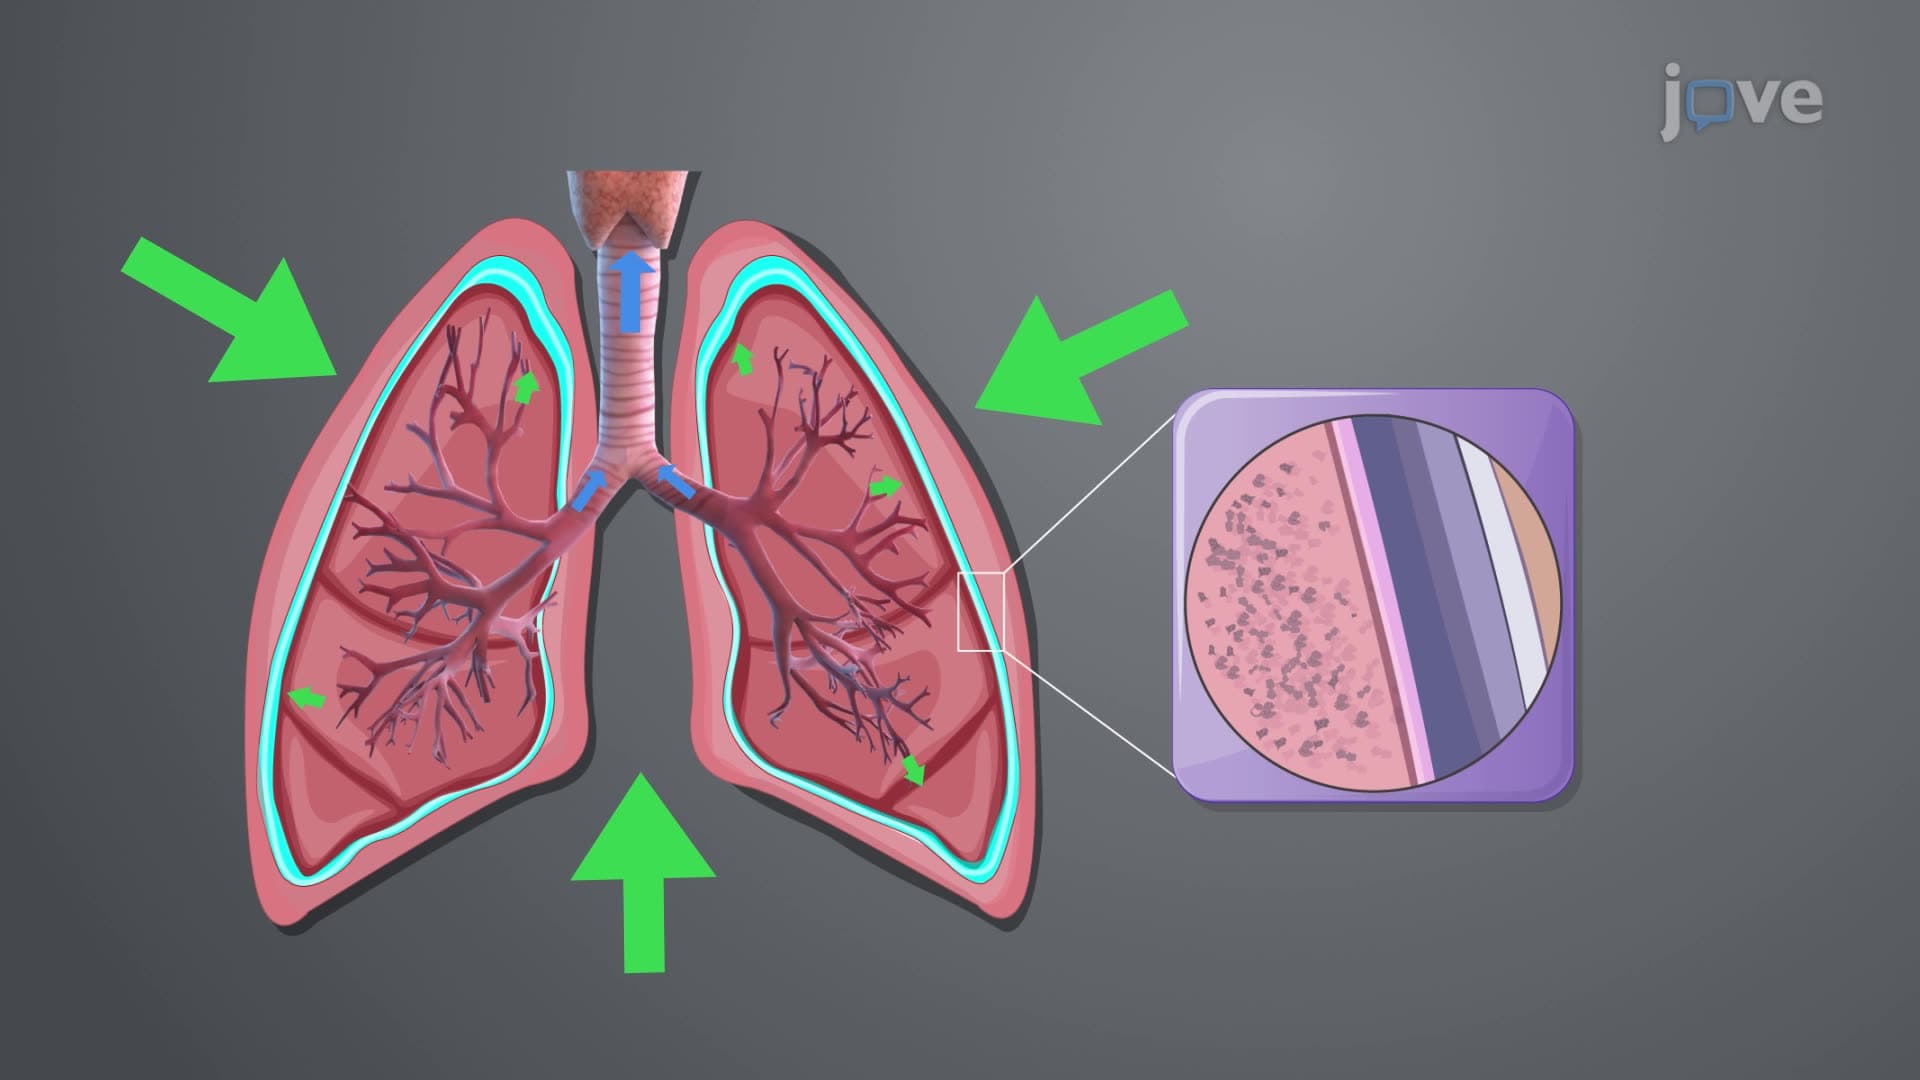
Pressure Relationships in Thoracic Cavity
Breathing Mechanisms
Both intra-alveolar and intrapleural pressures rely on specific lung properties. The ability to breathe—allowing air to enter the lungs during...