Related Experiment Video
Updated: Oct 9, 2026

07:43
Endoscopic Endonasal Trans-sphenoidal Approach: Minimally Invasive Surgery for Pituitary Adenomas
Published on: January 17, 2018
Refractory hypokalemia in metastatic adrenocorticotrophic hormone--secreting pituitary carcinoma
The Journal of the Association of Physicians of India
|March 29, 2001

Abstract
No abstract available in PubMed .
Related Concept Videos
 01:19
Cushing Syndrome II: Pathophysiology
Cortisol production is normally governed by the hypothalamic–pituitary–adrenal (HPA) axis, which maintains hormonal balance through tightly regulated feedback mechanisms. Disruption of this regulatory system is central to the development of Cushing syndrome, whether the excess cortisol originates from external medications or internal pathology. Persistent cortisol elevation alters metabolism, immune function, and endocrine signaling, producing the characteristic clinical features of the...
 01:26
Cushing Syndrome I: Introduction
Cushing syndrome refers to the collection of clinical manifestations that arise when tissues are exposed to excessive amounts of cortisol or cortisol-like medications over an extended period. Cortisol, a glucocorticoid produced by the adrenal cortex, regulates metabolism, immune responses, and the body’s adaptation to stress. When its concentration remains chronically elevated, these physiological pathways become dysregulated, resulting in the characteristic features of the syndrome.Exogenous...
 01:28
Antihypertensive Drugs: Potassium-Sparing Diuretics
Liddle syndrome is a genetically inherited form of hypertension characterized by the overactivity of epithelial sodium channels in the nephron, the functional unit of the kidney. This heightened activity leads to increased sodium reabsorption and excessive excretion of potassium. To counteract this, potassium-sparing diuretics such as amiloride are used. They function by blocking these sodium channels, thereby reducing the influx of sodium into the epithelial cells and minimizing the loss of...
 01:27
Hyperthyroidism II: Pathophysiology
Hyperthyroidism is a hypermetabolic state caused by elevated levels of thyroid hormones, triiodothyronine (T3) and thyroxine (T4). It results from dysregulation at the thyroid, pituitary, or immune system level and affects multiple organ systems.PathophysiologyThe most common cause of hyperthyroidism is Graves’ disease, an autoimmune disorder in which antibodies, specifically thyroid-stimulating antibodies (TSAb), a subtype of TSH receptor antibodies (TRAb), bind to and activate TSH receptors...
 01:23
Hypothyroidism II: Pathophysiology
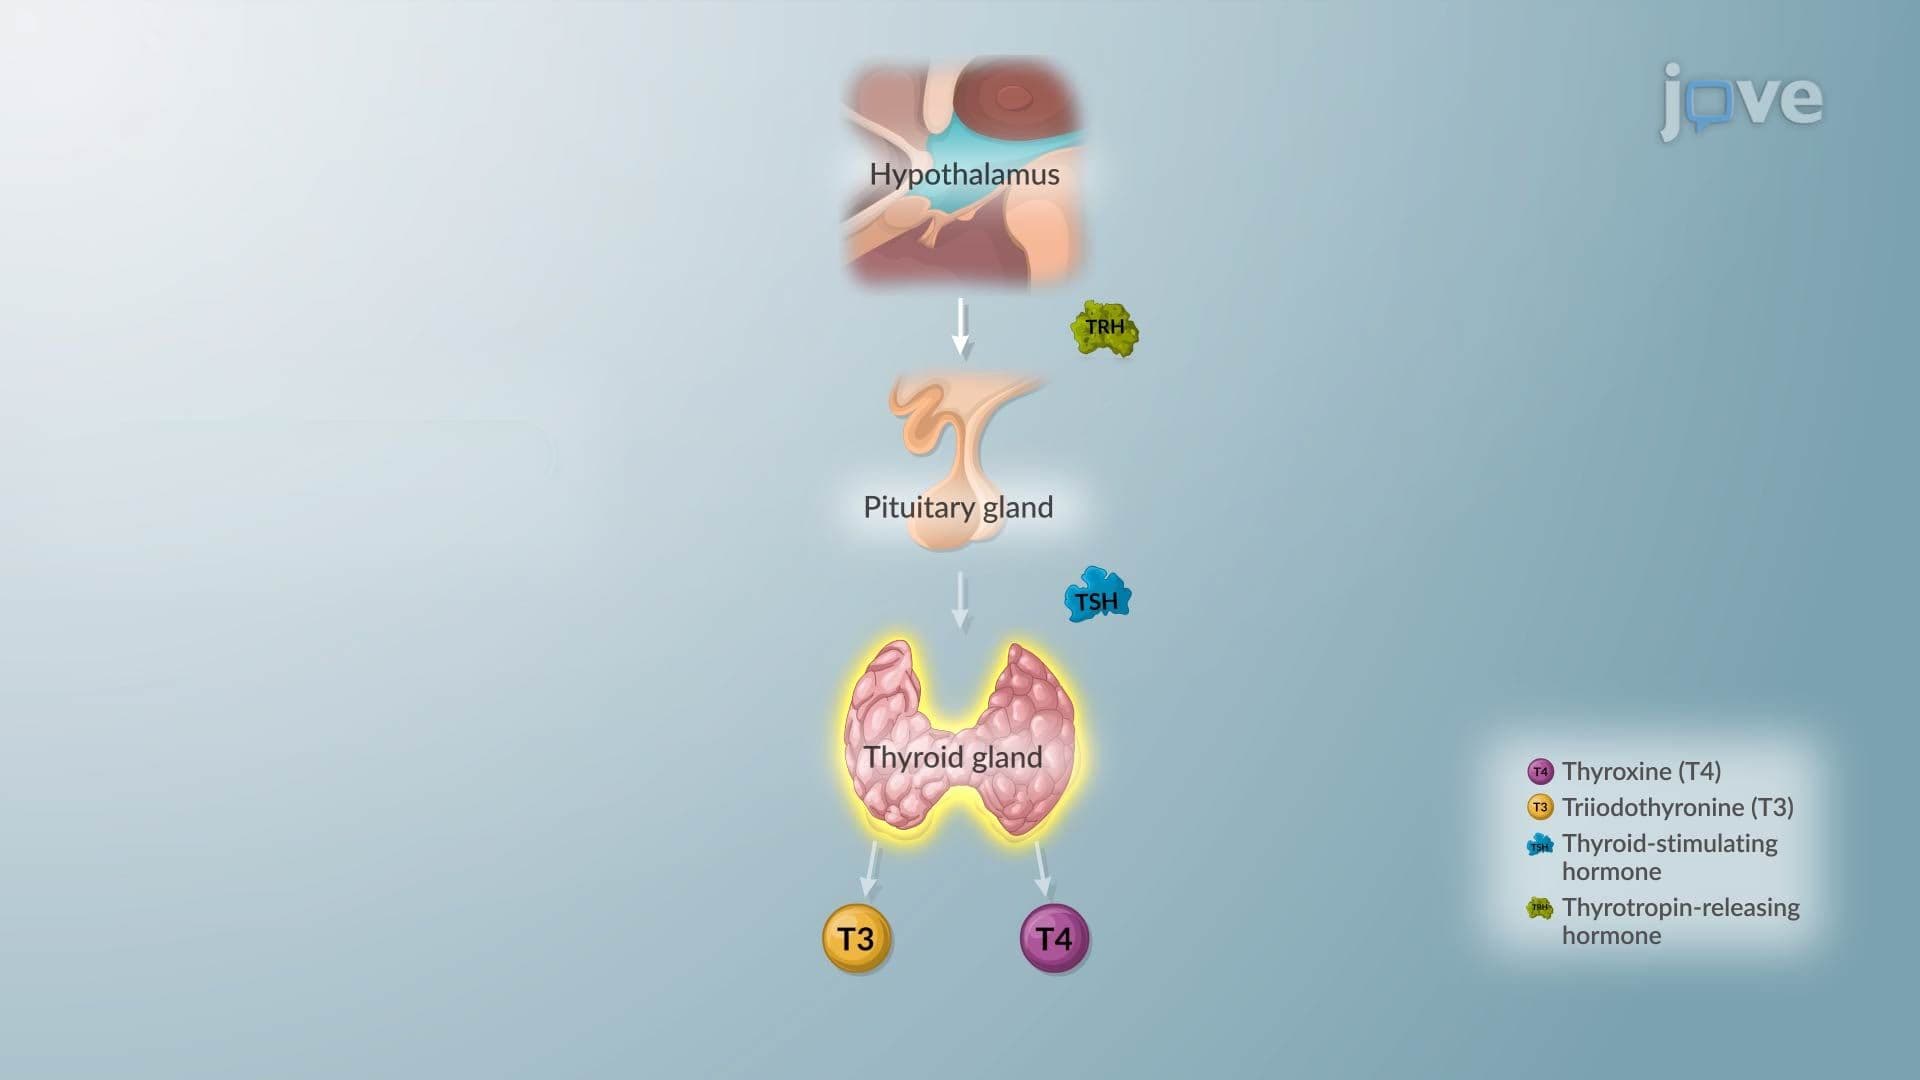
Hypothyroidism is a disorder characterized by insufficient production of thyroid hormones, which regulate metabolism, energy balance, and multiple organ systems.TypesHypothyroidism is classified based on the level of dysfunction. Primary hypothyroidism results from intrinsic thyroid gland dysfunction, causing reduced hormone production despite normal or increased stimulation. Secondary hypothyroidism arises from inadequate thyroid-stimulating hormone (TSH) secretion by the pituitary. Tertiary...
 01:28
Chemotherapy-Induced Nausea and Vomiting: Neurokinin-1 Receptor Antagonists
Neurokinin 1 (NK1) receptors are distributed across the GI tract, vagal afferents, and key CNS regions including the central vomiting center and chemoreceptor trigger zone (CTZ) Chemotherapy agents stimulate enterochromaffin cells in the gastrointestinal (GI) tract to release large amounts of substance P (SP). SP is a neuropeptide released by specific sensory nerves in response to many different stressors, including those in the GI mucosa affected by chemotherapy. SP binds and activates these...