Cefazolin dialytic clearance by high-efficiency and high-flux hemodialyzers
Related Experiment Videos
K M Sowinski1, B A Mueller, D W Grabe
1Department of Pharmacy Practice, School of Pharmacy and Pharmacal Sciences, Purdue University, Indianapolis, IN 46202-2879, USA. ksowinsk@iupui.edu

Abstract:
Cefazolin dialytic clearance has not been determined in patients undergoing hemodialysis with high-efficiency or high-flux dialyzers. The objective of this study is to determine the pharmacokinetics and dialytic clearance of cefazolin and develop dosing strategies in these patients. Twenty-five uninfected subjects undergoing chronic thrice-weekly hemodialysis were administered a single dose of intravenous cefazolin (15 mg/kg) after their standard hemodialysis session. Fifteen subjects underwent hemodialysis with high-efficiency hemodialyzers, and 10 subjects underwent hemodialysis with high-flux hemodialyzers. Blood and urine samples were collected serially over the interdialytic period, during the next intradialytic period, and immediately after the next hemodialysis session. Serum and urine concentrations of cefazolin were determined by high-performance liquid chromatography. Differential equations describing a two-compartment model were fit to the cefazolin serum concentration-time data over the study period, and pharmacokinetic parameters were determined. Mean dialytic clearance values for cefazolin were significantly greater in the high-flux group compared with the high-efficiency group (30.9 +/- 6.52 versus 18.0 +/- 6.26 mL/min, respectively; P: < 0.05). Cefazolin reduction ratios were significantly greater (0.62 +/- 0.08 versus 0.50 +/- 0.07; P: < 0.005) in the high-flux group compared with the high-efficiency group and correlated well with equilibrated urea reduction. The pharmacokinetic model developed from patient data was used to simulate cefazolin serum concentration data for high-efficiency and high-flux dialyzers. Cefazolin doses of 15 or 20 mg/kg after each hemodialysis session maintained adequate serum concentrations throughout a 2- or 3-day interdialytic period regardless of hemodialyzer type.
Related Concept Videos
 01:25
Extracorporeal Removal of Drugs: Hemoperfusion and Hemofiltration
 01:30
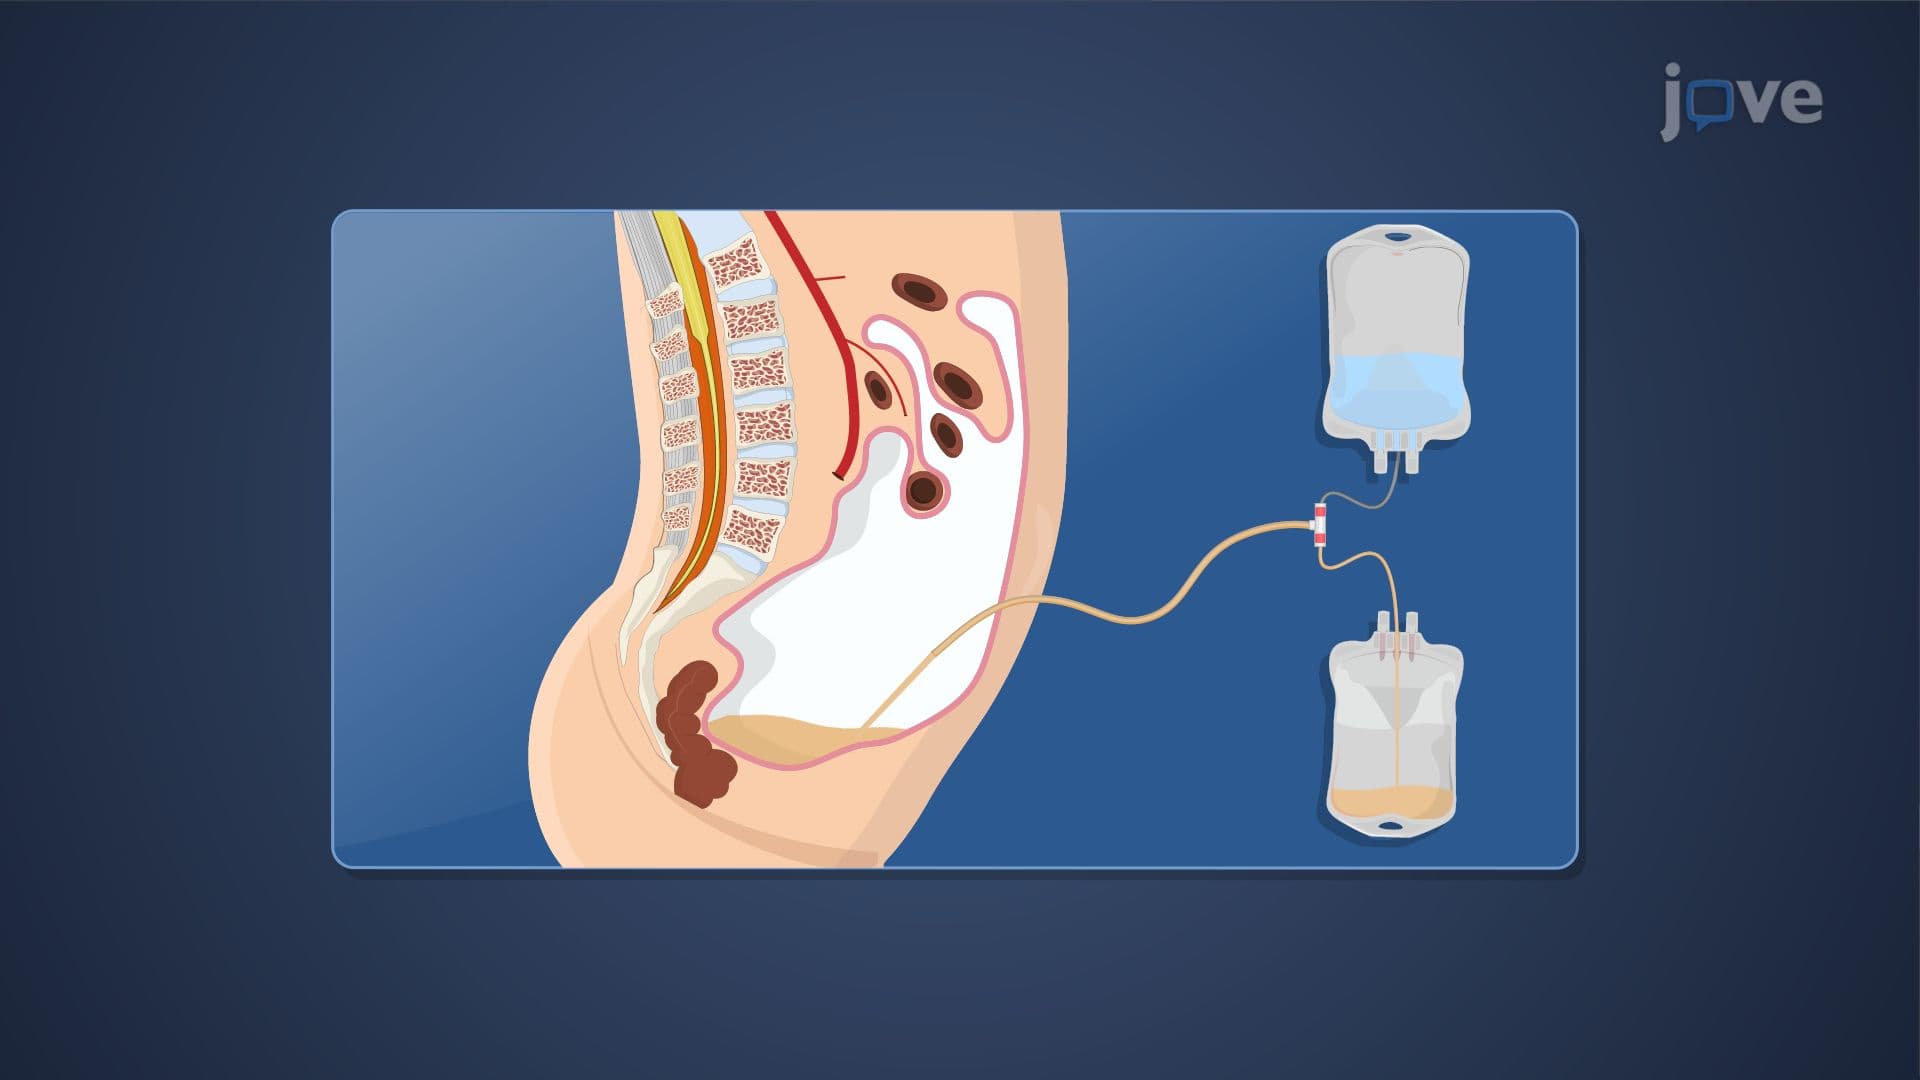
Extracorporeal Removal of Drugs: Peritoneal Dialysis and Hemodialysis
 01:15
Dialysis
 01:27
Dialysis
Acute kidney injury develops suddenly and can be caused by pre-renal causes (e.g., hypovolemia, shock), intrinsic renal causes (e.g., acute tubular necrosis), or post-renal causes (e.g., urinary obstruction). In contrast, chronic renal failure progresses gradually over time and is often...
 01:24
Hemodialysis II: Procedure and Complications
 01:09
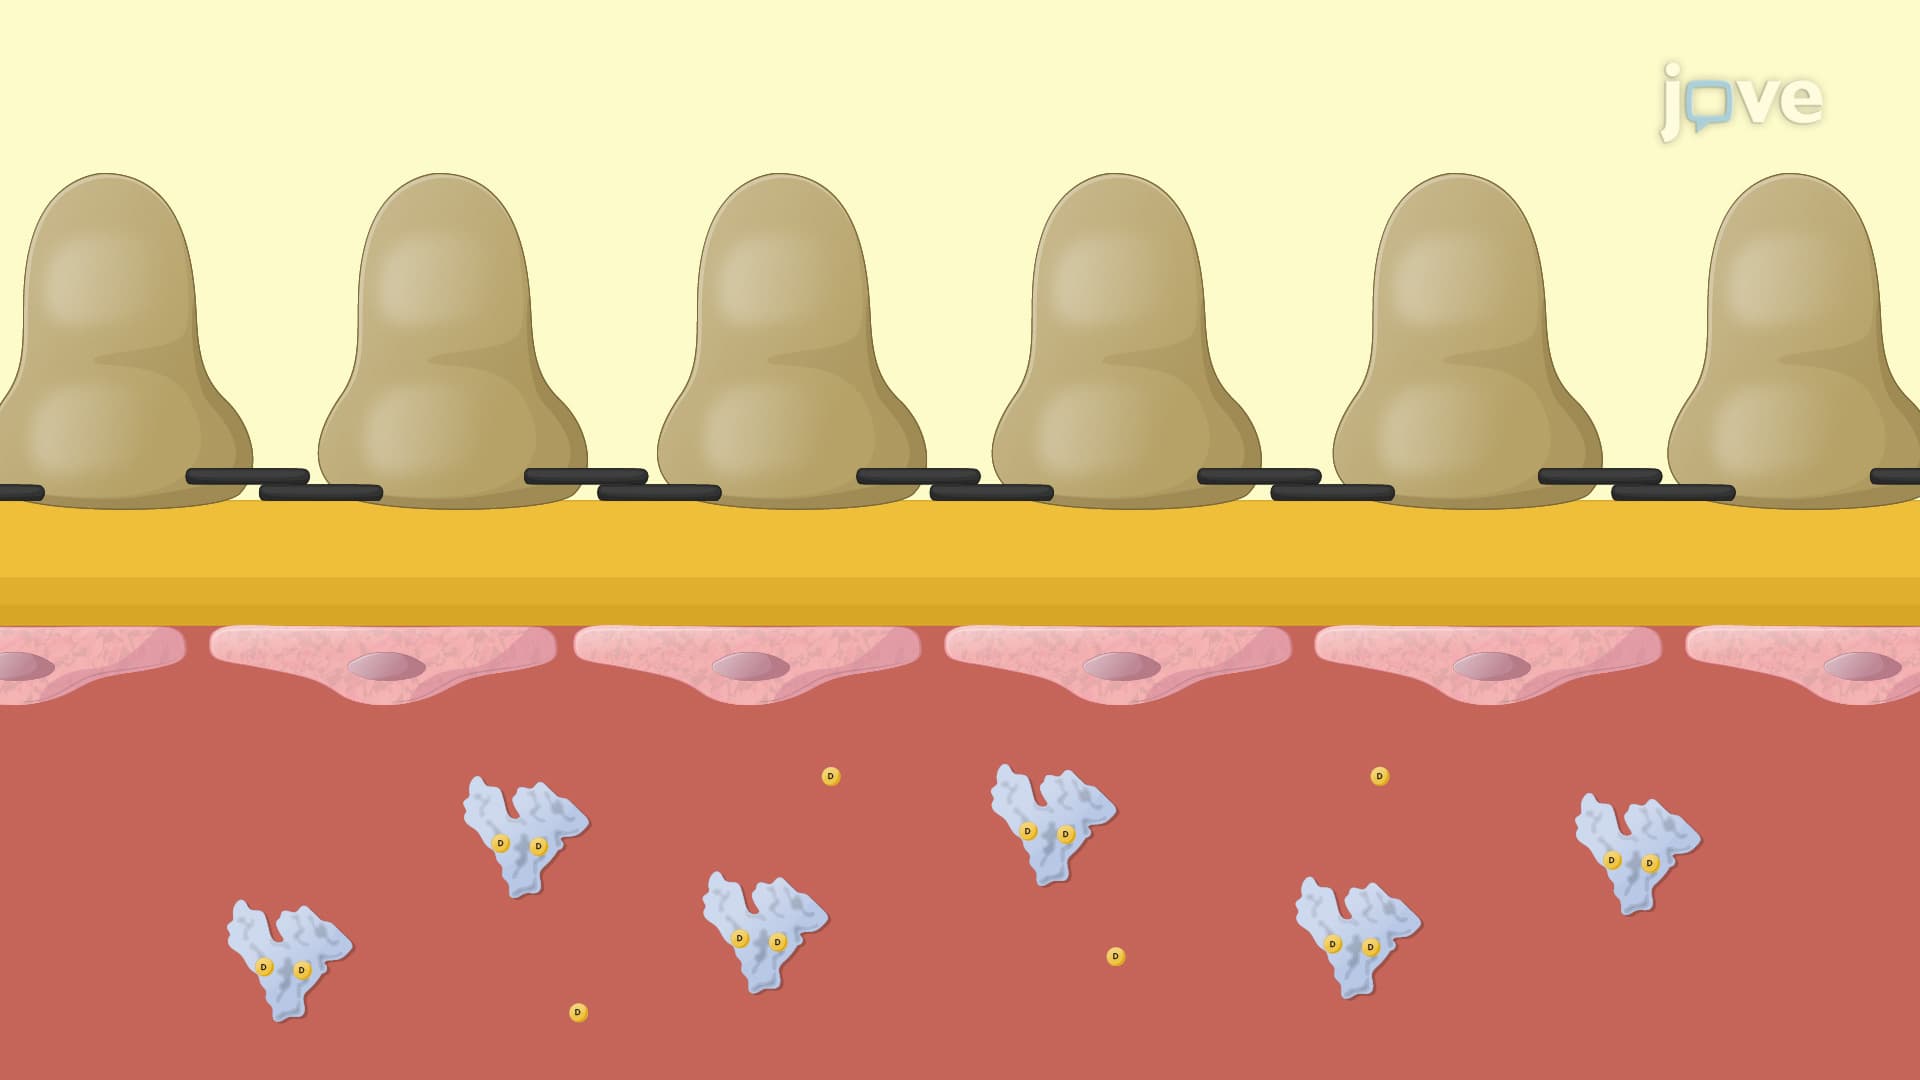
Factors Affecting Renal Clearance: Drug Distribution and Drug Interactions
One important factor is the relationship between renal clearance and the apparent volume of distribution. Renal clearance tends to be inversely proportional to the apparent volume of distribution. Drugs with an extensive distribution volume or those...