Related Experiment Video
Updated: Oct 8, 2026

Zebra II as A Novel System to Record Electrophysiological Signals in Zebrafish
Published on: August 16, 2024
The effects of amiodarone on the thyroid
E Martino1, L Bartalena, F Bogazzi
1Dipartimento di Endocrinologia e Metabolismo, University of Pisa, Ospedale de Cisanello, via Paradisa, 2, 56124 Pisa, Italy. e.martino@endoc.med.unipi.it

Amiodarone is a benzofuranic-derivative iodine-rich drug widely used for the treatment of tachyarrhythmias and, to a lesser extent, of ischemic heart disease. It often causes changes in thyroid function tests (typically an increase in serum T(4) and rT(3), and a decrease in serum T(3), concentrations), mainly related to the inhibition of 5'-deiodinase activity, resulting in a decrease in the generation of T(3) from T(4) and a decrease in the clearance of rT(3). In 14-18% of amiodarone-treated patients, there is overt thyroid dysfunction, either amiodarone-induced thyrotoxicosis (AIT) or amiodarone-induced hypothyroidism (AIH). Both AIT and AIH may develop either in apparently normal thyroid glands or in glands with preexisting, clinically silent abnormalities. Preexisting Hashimoto's thyroiditis is a definite risk factor for the occurrence of AIH. The pathogenesis of iodine-induced AIH is related to a failure to escape from the acute Wolff-Chaikoff effect due to defects in thyroid hormonogenesis, and, in patients with positive thyroid autoantibody tests, to concomitant Hashimoto's thyroiditis. AIT is primarily related to excess iodine-induced thyroid hormone synthesis in an abnormal thyroid gland (type I AIT) or to amiodarone-related destructive thyroiditis (type II AIT), but mixed forms frequently exist. Treatment of AIH consists of L-T(4) replacement while continuing amiodarone therapy; alternatively, if feasible, amiodarone can be discontinued, especially in the absence of thyroid abnormalities, and the natural course toward euthyroidism can be accelerated by a short course of potassium perchlorate treatment. In type I AIT the main medical treatment consists of the simultaneous administration of thionamides and potassium perchlorate, while in type II AIT, glucocorticoids are the most useful therapeutic option. Mixed forms are best treated with a combination of thionamides, potassium perchlorate, and glucocorticoids. Radioiodine therapy is usually not feasible due to the low thyroidal radioiodine uptake, while thyroidectomy can be performed in cases resistant to medical therapy, with a slightly increased surgical risk.
Amiodarone is a benzofuranic-derivative iodine-rich drug widely used for the treatment of tachyarrhythmias and, to a lesser extent, of ischemic heart disease. It often causes changes in thyroid function tests (typically an increase in serum T(4) and rT(3), and a decrease in serum T(3), concentrations), mainly related to the inhibition of 5'-deiodinase activity, resulting in a decrease in the generation of T(3) from T(4) and a decrease in the clearance of rT(3). In 14-18% of amiodarone-treated patients, there is overt thyroid dysfunction, either amiodarone-induced thyrotoxicosis (AIT) or amiodarone-induced hypothyroidism (AIH). Both AIT and AIH may develop either in apparently normal thyroid glands or in glands with preexisting, clinically silent abnormalities. Preexisting Hashimoto's thyroiditis is a definite risk factor for the occurrence of AIH. The pathogenesis of iodine-induced AIH is related to a failure to escape from the acute Wolff-Chaikoff effect due to defects in thyroid hormonogenesis, and, in patients with positive thyroid autoantibody tests, to concomitant Hashimoto's thyroiditis. AIT is primarily related to excess iodine-induced thyroid hormone synthesis in an abnormal thyroid gland (type I AIT) or to amiodarone-related destructive thyroiditis (type II AIT), but mixed forms frequently exist. Treatment of AIH consists of L-T(4) replacement while continuing amiodarone therapy; alternatively, if feasible, amiodarone can be discontinued, especially in the absence of thyroid abnormalities, and the natural course toward euthyroidism can be accelerated by a short course of potassium perchlorate treatment. In type I AIT the main medical treatment consists of the simultaneous administration of thionamides and potassium perchlorate, while in type II AIT, glucocorticoids are the most useful therapeutic option. Mixed forms are best treated with a combination of thionamides, potassium perchlorate, and glucocorticoids. Radioiodine therapy is usually not feasible due to the low thyroidal radioiodine uptake, while thyroidectomy can be performed in cases resistant to medical therapy, with a slightly increased surgical risk.
Related Concept Videos
 01:12
Antiarrhythmic Drugs: Class III Agents as Potassium Channel Blockers
 01:27
Hyperthyroidism II: Pathophysiology
 01:25
Hyperthyroidism I: Introduction
 01:18
Functions of Thyroid Hormones
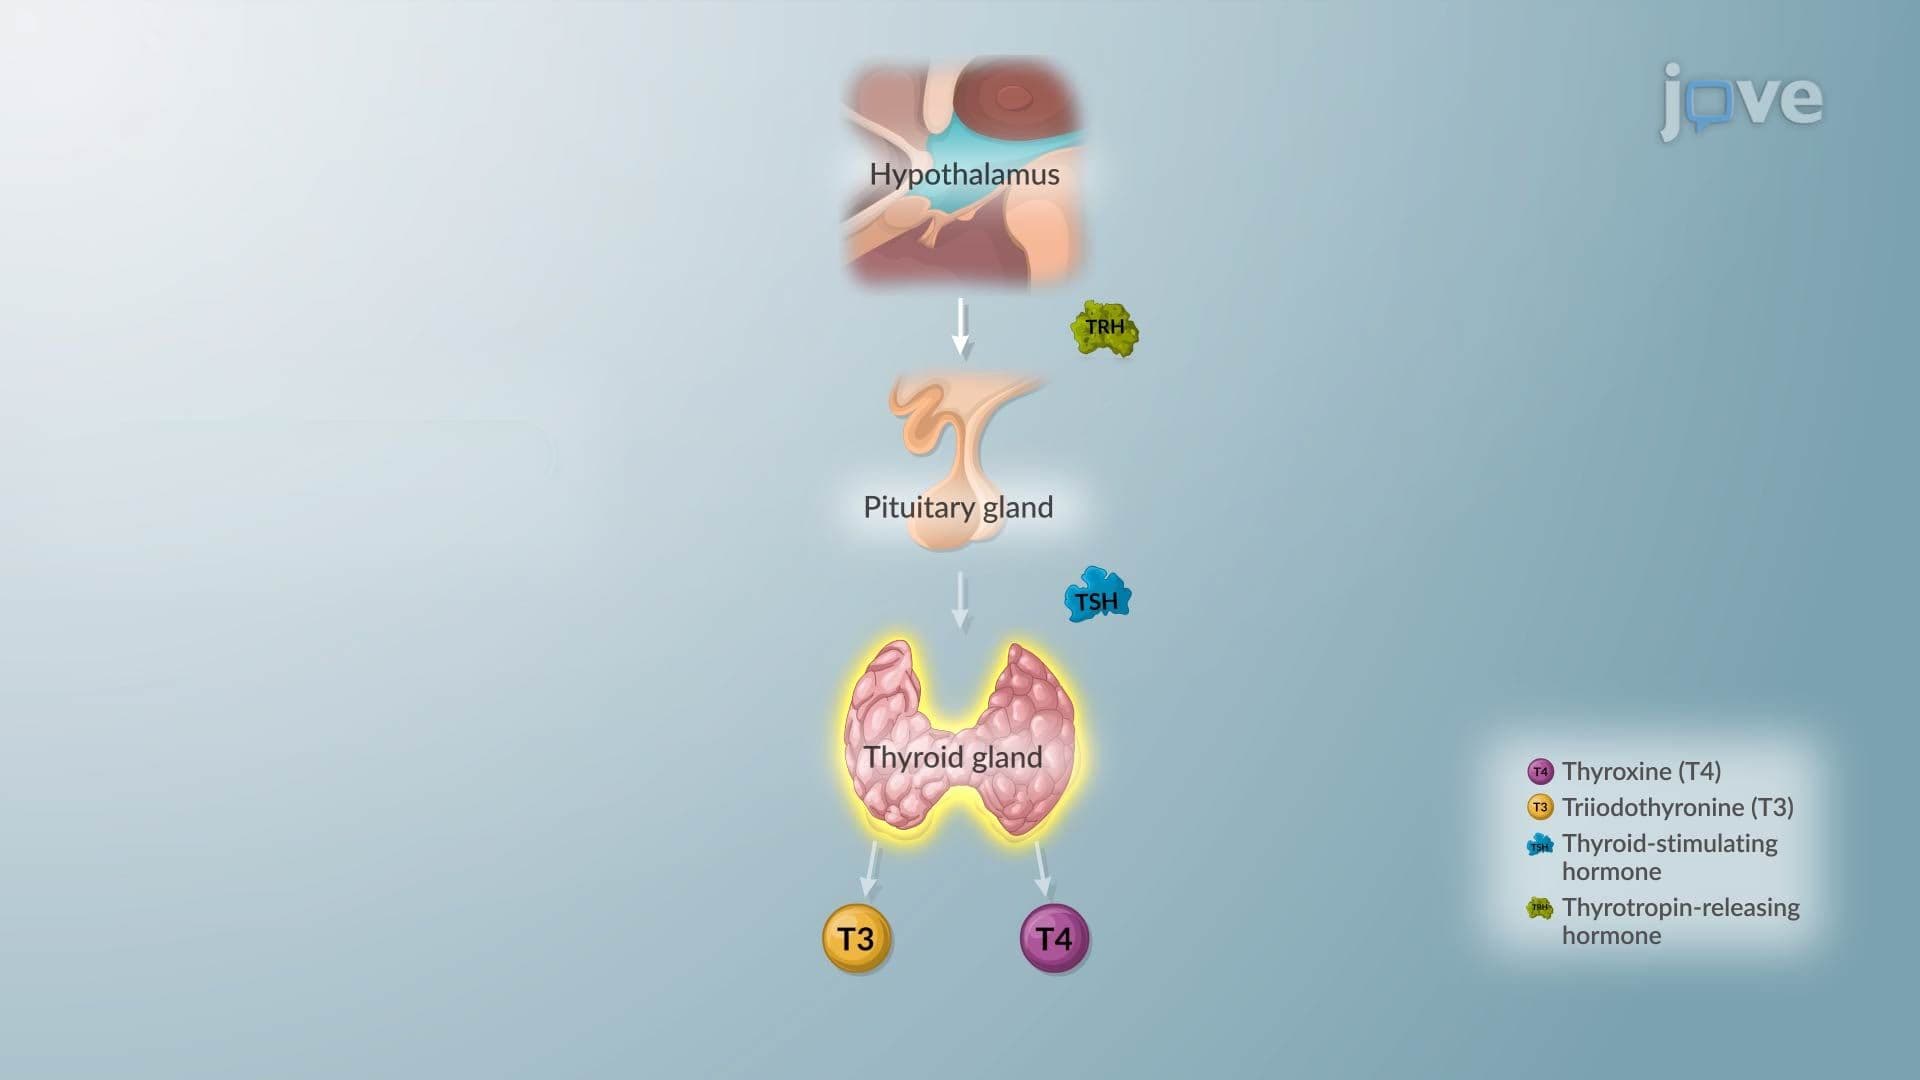
TH is indispensable for the normal development and maturation of the skeletal, muscular, and nervous systems during fetal and childhood growth. It facilitates bone mineral turnover and regulates protein synthesis in developing tissues, contributing significantly to overall growth and...
 01:23
Hypothyroidism II: Pathophysiology
 01:22
Antiarrhythmic Drugs: Class I Agents as Sodium Channel Blockers
Class 1A Antiarrhythmic Drugs: These drugs work by moderately blocking sodium channels,...