Receptor-based model accounts for phlebotomy-induced changes in erythropoietin pharmacokinetics
Related Experiment Video
Updated: Oct 8, 2026

A Comprehensive Pipeline to Assess the Efficiency of Human Erythropoiesis In Vitro and Ex Vivo
Published on: January 10, 2025
S H Chapel1, P Veng-Pedersen, R L Schmidt
1College of Pharmacy, Department of Pediatrics, The University of Iowa, Iowa City, IA 52242, USA.

Abstract:
Previous clinical studies have demonstrated two distinctive pharmacokinetic behaviors of erythropoietin (EPO): changes in pharmacokinetics (PK) after a period of rhEPO treatment and nonlinear pharmacokinetics. The objective of this work was to study the temporal changes in EPO's PK following phlebotomy in order to propose possible mechanisms for this behavior. Five healthy adult sheep were phlebotomized on two separate occasions 4-6 weeks apart to hemoglobin levels of PK 3-4 g/dL. PK parameters were estimated from the concentration-time profiles obtained following repeated intravenous bolus PK studies using tracer doses of biologically active 125I-rhEPO. Based on the changes in clearances, a PK model was derived to provide a mechanistic receptor-based description of the observed phenomena. Phlebotomy resulted in a rapid increase in the EPO plasma concentration, which peaked at 760 +/- 430 mU/mL (mean +/- SD) at 1.8 +/- 0.65 days, and which coincided with a transient reduction in EPO clearance from prephlebotomy values, i.e., from 45.6 +/- 11.2 mL/hr/kg to 24.3 +/- 9.7 mL/hr/kg. As plasma EPO levels returned toward baseline levels in the next few days, a subsequent increase in EPO clearance was noted. EPO clearance peaked at 90.2 +/- 26.2 mL/hr/kg at 8.5 +/- 3.3 days and returned to baseline by 4-5 weeks postphlebotomy. The proposed model derived from these data includes positive feedback control of the EPO receptor (EPOR) pool. The model predicts that: 1) the initial reduction in EPO plasma clearance is due to a transient saturation of EPORs resulting from the phlebotomy-induced high EPO concentration; and 2) the EPOR pool is expandable not only to compensate for EPOR loss but also to adjust to a greater need for EPORs/progenitor cells to restore hemoglobin (Hb) concentration to normal levels.
More Related Videos
 05:23
Continuous Manual Exchange Transfusion for Patients with Sickle Cell Disease: An Efficient Method to Avoid Iron Overload
Published on: March 14, 2017
 07:52
Detection of Antibodies That Neutralize the Cellular Uptake of Enzyme Replacement Therapies with a Cell-based Assay
Published on: September 10, 2018
Related Concept Videos
 01:09
Pharmacodynamic Models: Additive and Proportional Drug Effect Model
 01:29
Pharmacodynamic Models: Direct Effect Model and Indirect Response Model
 01:13
Physiological Pharmacokinetic Models: Assumption with Protein Binding
 01:14
Pharmacodynamic Models: Link Model and Systems Pharmacodynamic Model
 01:18
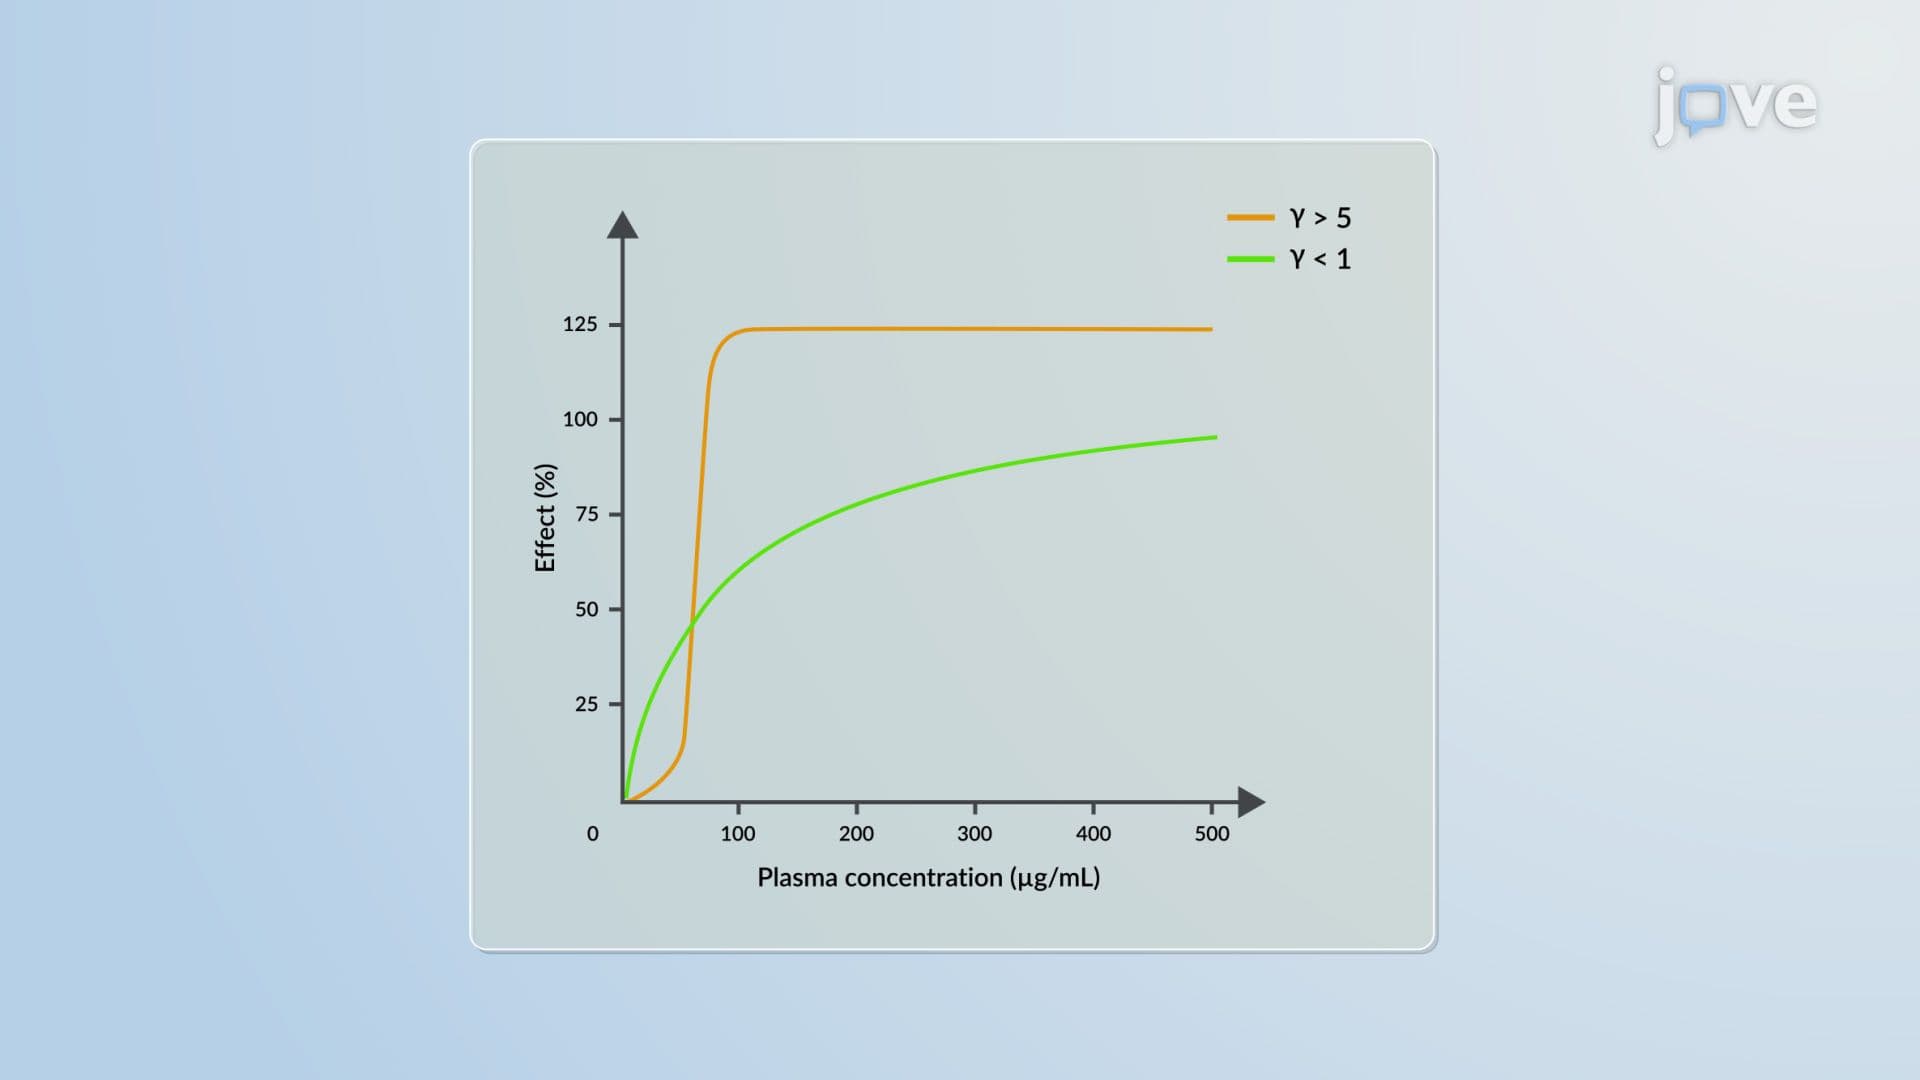
Pharmacodynamic Models: Emax Drug–Concentration Effect Model
 01:24
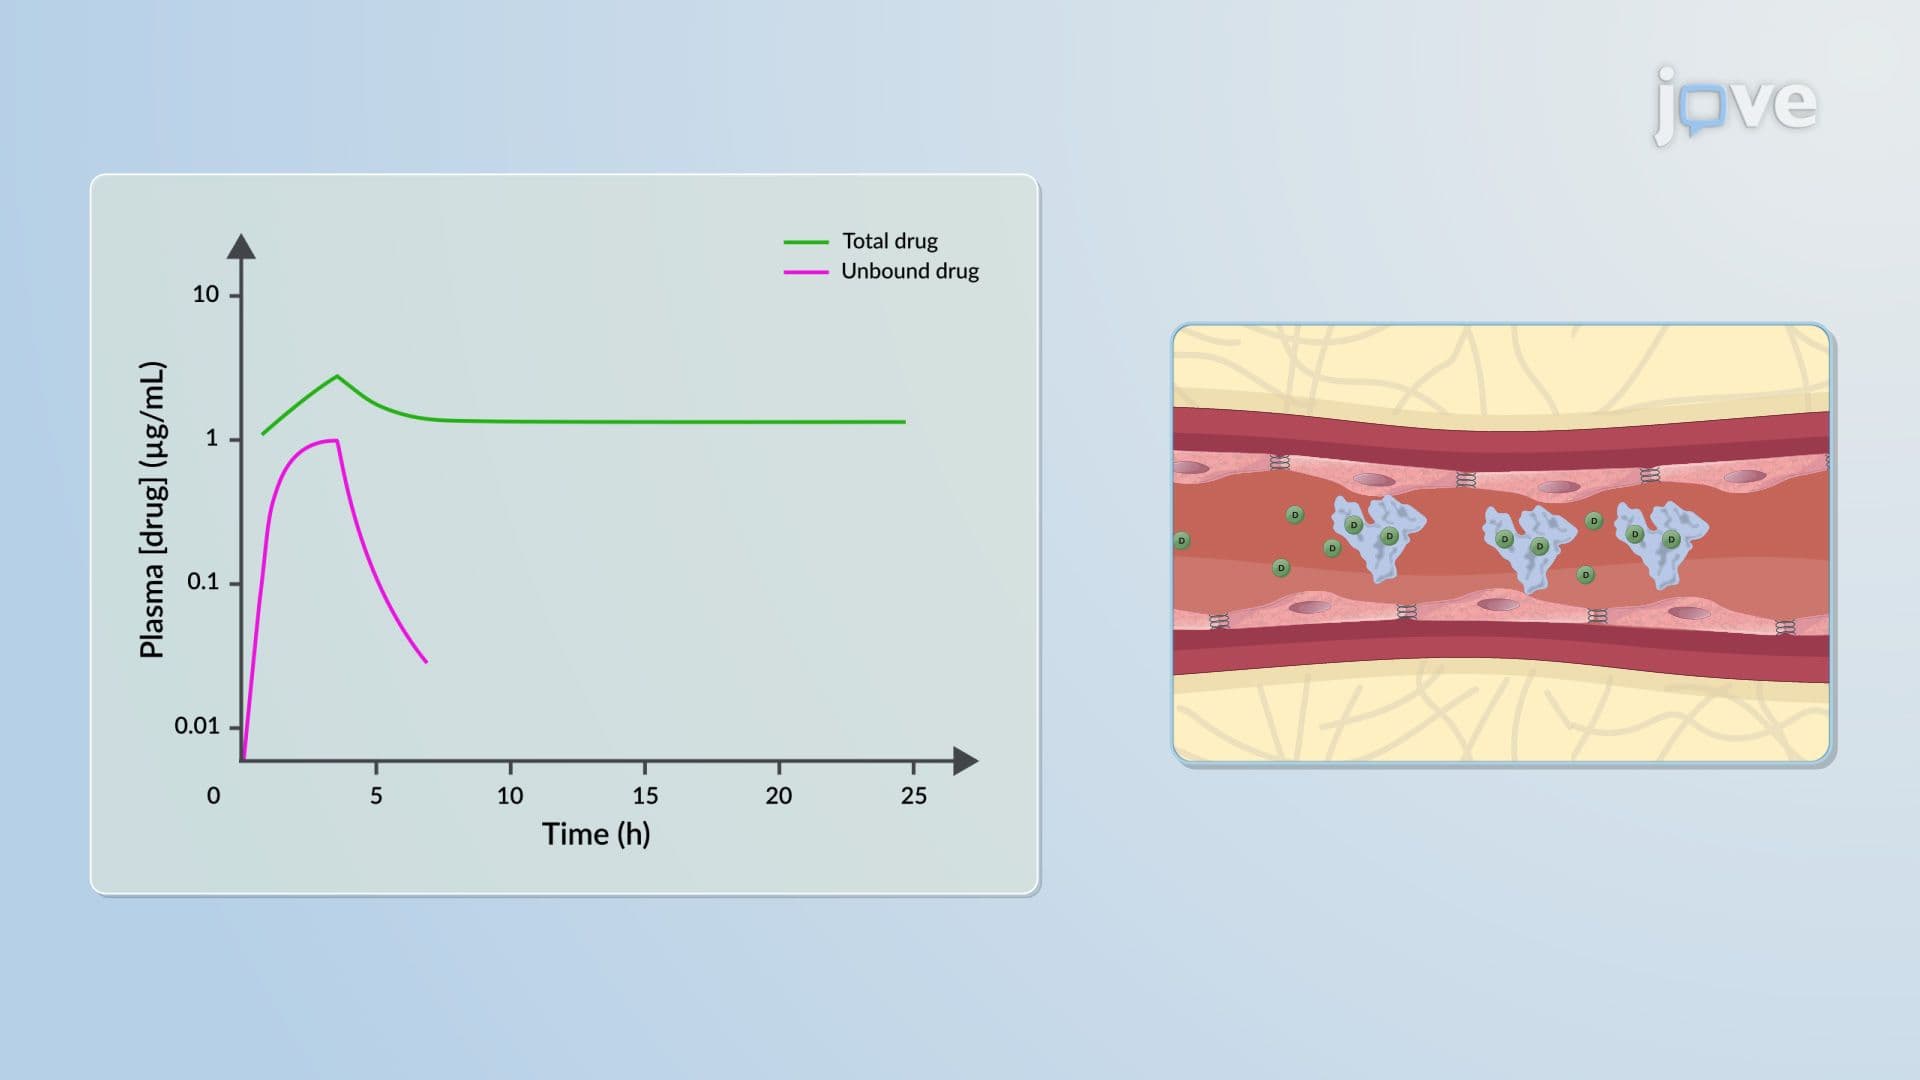
Pharmacokinetic–Pharmacodynamic Relationship: Problems