[Postobstructive polyuria in unilateral hydronephrosis. A case with 58 l/day]
Related Experiment Video
Updated: Oct 8, 2026
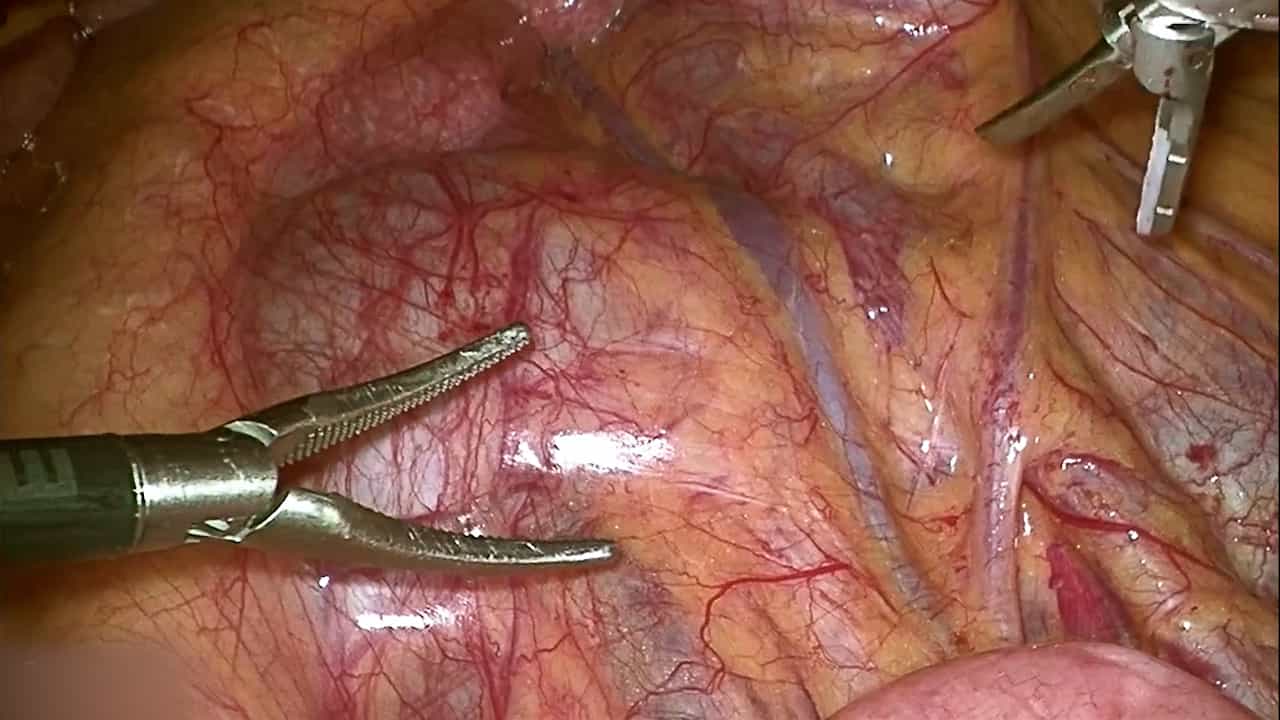
Transmesenteric Laparoscopic Pyeloplasty in Trendelenburg Position for Horseshoe Kidney with Hydronephrosis
Published on: July 8, 2025
R Thiel1, A Prützmann, T Strittmatter
1Klinik für Urologie und Kinderurologie, Kliniken Maria Hilf, Viersener Str. 450, 41063 Mönchengladbach. thielr@mariahilf.de

Abstract:
Increased urinary outputs are common after release of bilateral ureteral or subvesical obstruction. However, polyuria is rare following unilateral obstruction. We report a case of excessive postobstructive diuresis of more than 58,000 ml per day (204 l in 10 days) after release of a left ureteral obstruction in a 56-year-old female, being the highest amounts reported in the literature. Polyuria was derived from the obstructed as well as from the normal contralateral kidney. The involved pathomechanism is complex and not completely understood. Treatment includes careful monitoring of the patient and replacement of fluid and electrolytes. In our case complete recovery of kidney function was observed after several days.

Related Concept Videos
 01:22
Diabetes Insipidus II: Pathophysiology
 01:29
Diabetes Insipidus I: Introduction
 01:28
Urinary Tract Calculi V: Nursing Management
 01:20
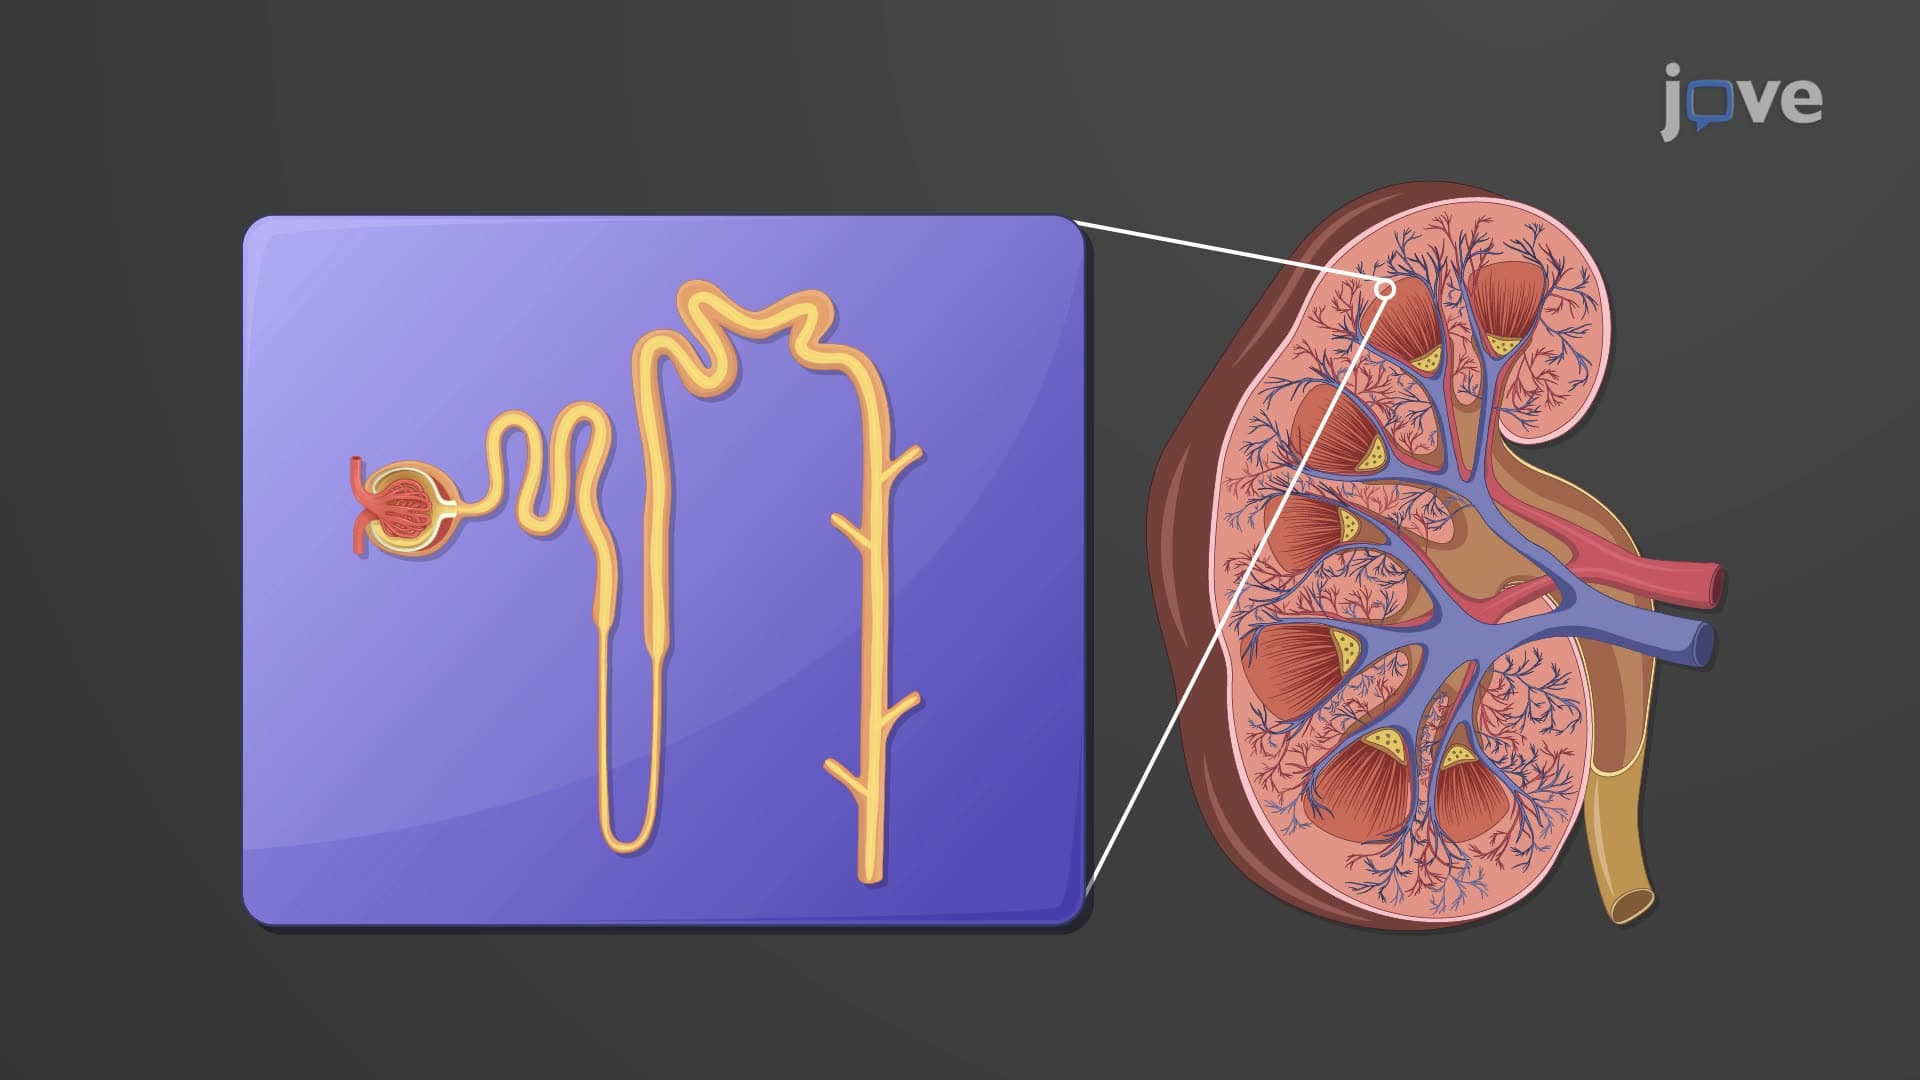
Formation of Dilute Urine
Filtrate Osmolarity in the PCT
Initially, as the filtrate passes through the proximal convoluted tubule (PCT), its...
 01:24
Renal Tubule and Collecting Duct
Proximal Convoluted Tubule (PCT):
The PCT is the initial segment of the renal tubule, extending from the Bowman's capsule that encloses the glomerulus. Its convoluted structure and microvilli-lined cells increase the surface area for reabsorption. The PCT reabsorbs glucose, amino acids, sodium, and water from the filtrate, ensuring essential...
 01:29
Acute Kidney Injury II: Pathophysiology