Related Experiment Video
Updated: Oct 8, 2026
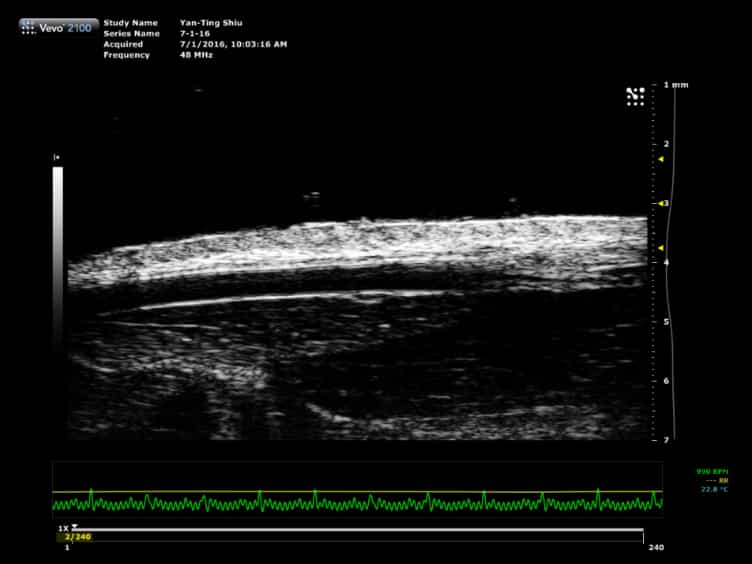
Ultrasound Assessment of Endothelial-Dependent Flow-Mediated Vasodilation of the Brachial Artery in Clinical Research
Published on: October 22, 2014
Flow-mediated dilatation of the brachial artery and left ventricular geometry in hypertensive patients
M L Muiesan1, M Salvetti, C Monteduro
1Department of Medical and Surgical Sciences, Internal Medicine, University of Brescia, Italy. muiesan@master.cci.unibs.it

Insights
Endothelial dysfunction in hypertension is common but not linked to left ventricular hypertrophy (LVH) or specific geometric patterns. These conditions likely arise from independent underlying mechanisms in hypertensive patients.
Area of Science:
- Cardiovascular Medicine
- Hypertension Research
- Vascular Biology
Background:
- Arterial hypertension can manifest diverse left ventricular (LV) geometric patterns, potentially mirroring vascular changes elsewhere.
- Hypertensive left ventricular hypertrophy (LVH) is often linked to endothelial dysfunction, assessed via vascular responses.
- Flow-mediated vasodilatation (FMD) offers a non-invasive measure of endothelium-dependent vasodilation.
Purpose of the Study:
- To investigate the relationship between brachial artery FMD and LV geometric adaptations in hypertensive individuals.
- To determine if endothelial function varies across different LV geometric patterns in hypertension.
Main Methods:
- Echocardiography was used to measure LV mass index (LVMI) and relative wall thickness (RWT) in 78 hypertensive and 16 normotensive subjects.
- High-resolution ultrasound assessed brachial artery diameter changes during reactive hyperemia and after GTN administration.
- Pulsed Doppler measured brachial artery flow velocity.
Main Results:
- Hypertensive patients exhibited reduced FMD compared to normotensive controls (P<0.01).
- No significant correlation was found between FMD and LVMI (r=-0.078) or RWT (r=0.049).
- FMD did not differ significantly among hypertensive patients with normal LV geometry, concentric remodeling, or concentric/eccentric LVH.
Conclusions:
- Endothelial dysfunction in hypertension is not associated with the presence or pattern of LVH.
- These findings suggest that mechanisms driving LVH and endothelial dysfunction in hypertension may operate independently.
- Further research is needed to elucidate the distinct pathways contributing to these cardiovascular alterations.
Objectives:
In arterial hypertension, the spectrum of geometric patterns in the left ventricle may parallel the structural alterations detected in the carotid arteries and in subcutaneous small arteries. It has been also reported that hypertensive left ventricular hypertrophy (LVH) may be associated with endothelial dysfunction, as evaluated by the response of coronary or forearm vasculature to acetylcholine infusion. The aim of this study was to evaluate the flow-mediated vasodilatation (FMD) of the brachial artery, non-invasive estimate of endothelium-dependent vasodilatation according to left ventricular geometric adaptations in hypertensive patients.
Methods And Results:
In 16 normotensive (nine males, seven females, aged 40-68 years) and in 78 hypertensive subjects (50 males, 28 females, aged 42-67 years), we performed an echocardiographic study for the measurement of left ventricular mass index (LVMI) and relative wall thickness (RWT); we measured to a high resolution the brachial artery diameter at rest, during reactive hyperaemia (5 min of brachial artery occlusion) and after sublingual glyceril trinitrate (GTN); brachial artery flow velocity was measured by pulsed Doppler. Twenty-six hypertensive patients had a normal LVMI (LVMI < 51 g/ m2.7) and geometry (RWT < 0.44), five had concentric remodelling (RWT > or = 0.44), and concentric and eccentric LVH were observed in 19 and 28 patients, respectively. FMD was reduced in hypertensive patients as compared with normotensive subjects (P< 0.01). No correlation was found between FMD and LVMI (r= -0.078) or RWT (r = 0.049); in addition, no difference in FMD was found among the left ventricular geometric patterns in hypertensive patients.
Conclusions:
In hypertensives, the presence of endothelial dysfunction is not associated with the LVH or with different left ventricular geometric patterns, suggesting that different and independent mechanisms may be responsible for the presence of LVH and of endothelial dysfunction.
Related Concept Videos
 01:29
Heart Failure II: Pathophysiology
 01:22
Aortic Regurgitation II: Clinical Features and Diagnostic Tests
 01:29
Cardiomyopathy III: Hypertrophic Cardiomyopathy
 01:20
Mitral Regurgitation I: Introduction
 01:17
Measurement of Blood Pressure
 01:23
Assessment of blood pressure in brachial artery(two-step method)