Related Experiment Video
Updated: Aug 7, 2026
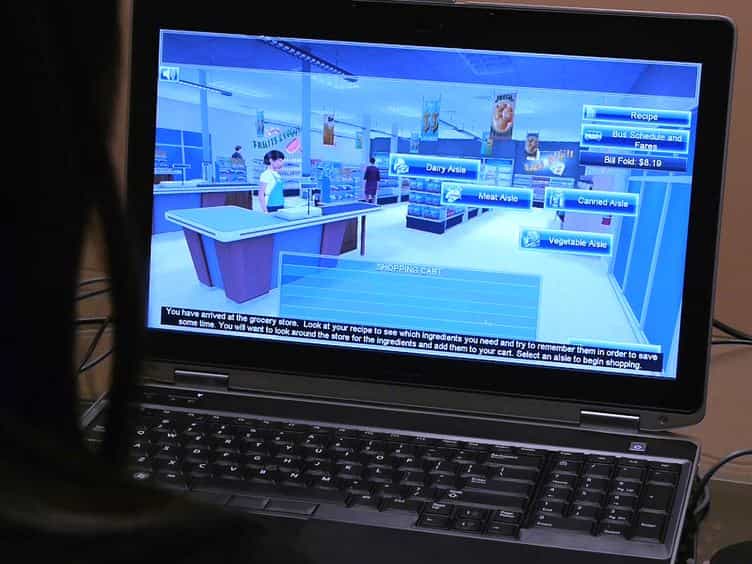

Development of a Virtual Reality Assessment of Everyday Living Skills
Published on: April 23, 2014
Dissemination of educational classes for families of adults with schizophrenia
1Pacific Clinics Institute, 909 South Fair Oaks Avenue, Pasadena, CA 91105-2625, USA. camenson@pacificclinics.org

Abstract:
Despite the well-documented efficacy of psychoeducational and behavioral approaches in family interventions for persons with serious mental illness (1), clinicians have rarely included these methods in their professional repertoires (2). Journal publications, books, continuing education courses, and advocacy by the National Alliance for the Mentally Ill and its local affiliates have induced few professionals to provide family psychoeducation. Mental health professionals adopt new services primarily for the same reason that employees of any firm change their work practices-namely, because the authority structure and contingencies of reinforcement that impinge on their daily activities are altered in a direction favoring change. Therefore, administrative clout must be brought to bear to mandate the inclusion of family psychoeducation in the spectrum of services provided by a clinic, mental health center, community support program, hospital, or independent provider (3). In addition, the consequences of clinicians' services must differentially reward the use of these methods of involving families in services for the seriously mentally ill (4). Differential rewards could come from performance standards and evaluations, performance-based pay, third-party payments, positive feedback from clients and families, public recognition, and increased self-efficacy. Use of in-service training or workshops to persuade clinicians to adopt innovations such as family psychoeducation and family management techniques has a checkered and unremarkable track record. For example, brief training has failed completely in efforts to bring about adoption of family interventions. On the other hand, more extended efforts to train staff, including organizational consultation, have been more successful (5). In one study, two days of staff training produced no change, whereas intensive training over several months resulted in the implementation of new family programs at the majority of study sites (6). Staff from sites that received extensive training but did not adopt the interventions rated family interventions as less consistent with their professional philosophy and agency norms and identified more obstacles to intervention, notably intense work pressure, uncertainty about financing the intervention, agency bureaucracy, lack of leadership, skepticism about the interventions, problems with confidentiality, and inability to provide services in the evenings or on weekends (6). In this Rehab Rounds column, Amenson and Liberman describe a three-phase, multilevel dissemination effort designed to overcome the above-mentioned barriers to the incorporation of family psychoeducation into the routine care provided at community mental health centers in an ethnically diverse urban setting. Moreover, Amenson and Liberman demonstrate the need for continued support and nurturance of the project to ensure that the original enthusiasm associated with a novel intervention is not lost once it becomes a standard part of treatment.


Related Concept Videos
 01:30
Specialized Care Centers and Settings-I
Daycare centers
They provide several functions. Some facilities care for healthy newborns and children whose parents work, while others are medically focused and care for...
 01:17
Schizophrenia
 01:29
Psychological and Sociocultural Causes of Schizophrenia
 01:30
Family Therapy
Strategic Family Therapy
Strategic family therapy emphasizes resolving communication barriers and improving problem-solving abilities...
 01:30
Community Based Intervention
Foundations of Community Mental Health Programs
Central to the success of community-based interventions is the...
 01:29
Relationship with Other Adult Family Members and Siblings