Neonatal thyroxine supplementation in very preterm children: developmental outcome evaluated at early school age
Related Experiment Videos
J M Briët1, A G van Wassenaer, F W Dekker
1Department of Neonatology, University of Amsterdam, Amsterdam, The Netherlands. j.m.briet@amc.uva.nl

Insights
Thyroxine (T4) supplementation in extremely premature infants showed benefits for cognitive and motor outcomes in those born before 29 weeks gestation. However, T4 supplementation was linked to developmental issues in infants born at 29 weeks gestation.
Area of Science:
- Neonatal Medicine
- Developmental Pediatrics
- Endocrinology
Background:
- Transient hypothyroxinemia in very premature infants is linked to developmental challenges.
- Previous studies indicated thyroxine (T4) supplementation improved mental outcomes at 2 years for infants born at 25/26 weeks gestation.
- The long-term effects of T4 supplementation beyond 2 years were previously unknown.
Purpose of the Study:
- To evaluate the effects of neonatal thyroxine (T4) supplementation on neurodevelopmental outcomes at early school age (5.7 years).
- To assess cognitive, behavioral, and motor development in survivors of a randomized, placebo-controlled T4 supplementation trial.
Main Methods:
- A randomized, placebo-controlled trial involving 200 infants born before 30 weeks gestation.
- Survivors were assessed at 5.7 years using standardized cognitive, behavioral, and motor assessments.
- Neurologic functioning was qualitatively assessed.
Main Results:
- Thyroxine (T4) supplementation showed benefits for children born before 29 weeks gestation, particularly those born at 25/26 weeks.
- A 10-point IQ difference favored the T4 group in infants <27 weeks gestation.
- In contrast, infants born at 29 weeks gestation showed a 15-point IQ difference favoring the placebo group.
- Behavioral outcomes varied, with fewer problems in the T4 group for 25/26-week infants but more problems for 27-week infants.
- Motor and neurologic outcomes favored T4 treatment for infants <29 weeks gestation, but not for those born at 29 weeks.
Conclusions:
- Neonatal thyroxine (T4) supplementation offers developmental benefits for extremely premature infants born before 29 weeks gestation.
- The most significant benefits were observed in infants born at 25/26 weeks gestation.
- Conversely, T4 supplementation in infants born at 29 weeks gestation was associated with adverse developmental outcomes.
Objective:
Transient hypothyroxinemia in very premature infants is associated with developmental problems. A randomized, placebo-controlled trial of thyroxine (T(4)) supplementation was conducted in a group of 200 infants <30 weeks' gestation. T(4) supplementation improved mental outcome at 2 years old in children of 25/26 weeks' gestation only. The effect of T(4) supplementation beyond 2 years of age is unknown. We present the effects of neonatal T(4) supplementation on outcome at early school age.
Methods:
Standardized measurements were used to assess cognitive, behavioral, and motor outcome, as well as a qualitative assessment of neurologic functioning. Survivors of the T(4) trial were assessed at the age of 5.7 years.
Results:
Ninety-nine percent of the 157 survivors participated. Outcome on all domains was comparable between the T(4) group and placebo group. In children <27 weeks' gestation, a 10 IQ point difference was found in favor of the T(4) group, whereas in children of 29 weeks' gestation, a difference of 15 IQ points was found in favor of the placebo group. Teachers' reports showed less behavioral problems in the T(4)-treated children of 25/26 weeks' gestation, but more behavioral problems in the T(4)-treated children of 27 weeks' gestation. Differences in motor outcome and neurologic outcome were in favor of the T(4)-treated children <29 weeks' gestation, but not of the T(4)-treated children of 29 weeks' gestation.
Conclusions:
We found benefits of T(4) supplementation for children <29 weeks' gestation, and especially in children of 25/26 weeks' gestation. However, in children of 29 weeks' gestation T(4) supplementation is associated with more developmental problems.
Related Concept Videos
 01:18
Functions of Thyroid Hormones
TH is indispensable for the normal development and maturation of the skeletal, muscular, and nervous systems during fetal and childhood growth. It facilitates bone mineral turnover and regulates protein synthesis in developing tissues, contributing significantly to overall growth and...
 01:18
Physical Growth During Infancy and Toddlerhood
 01:20
Synthesis and Regulation of Thyroid Hormones
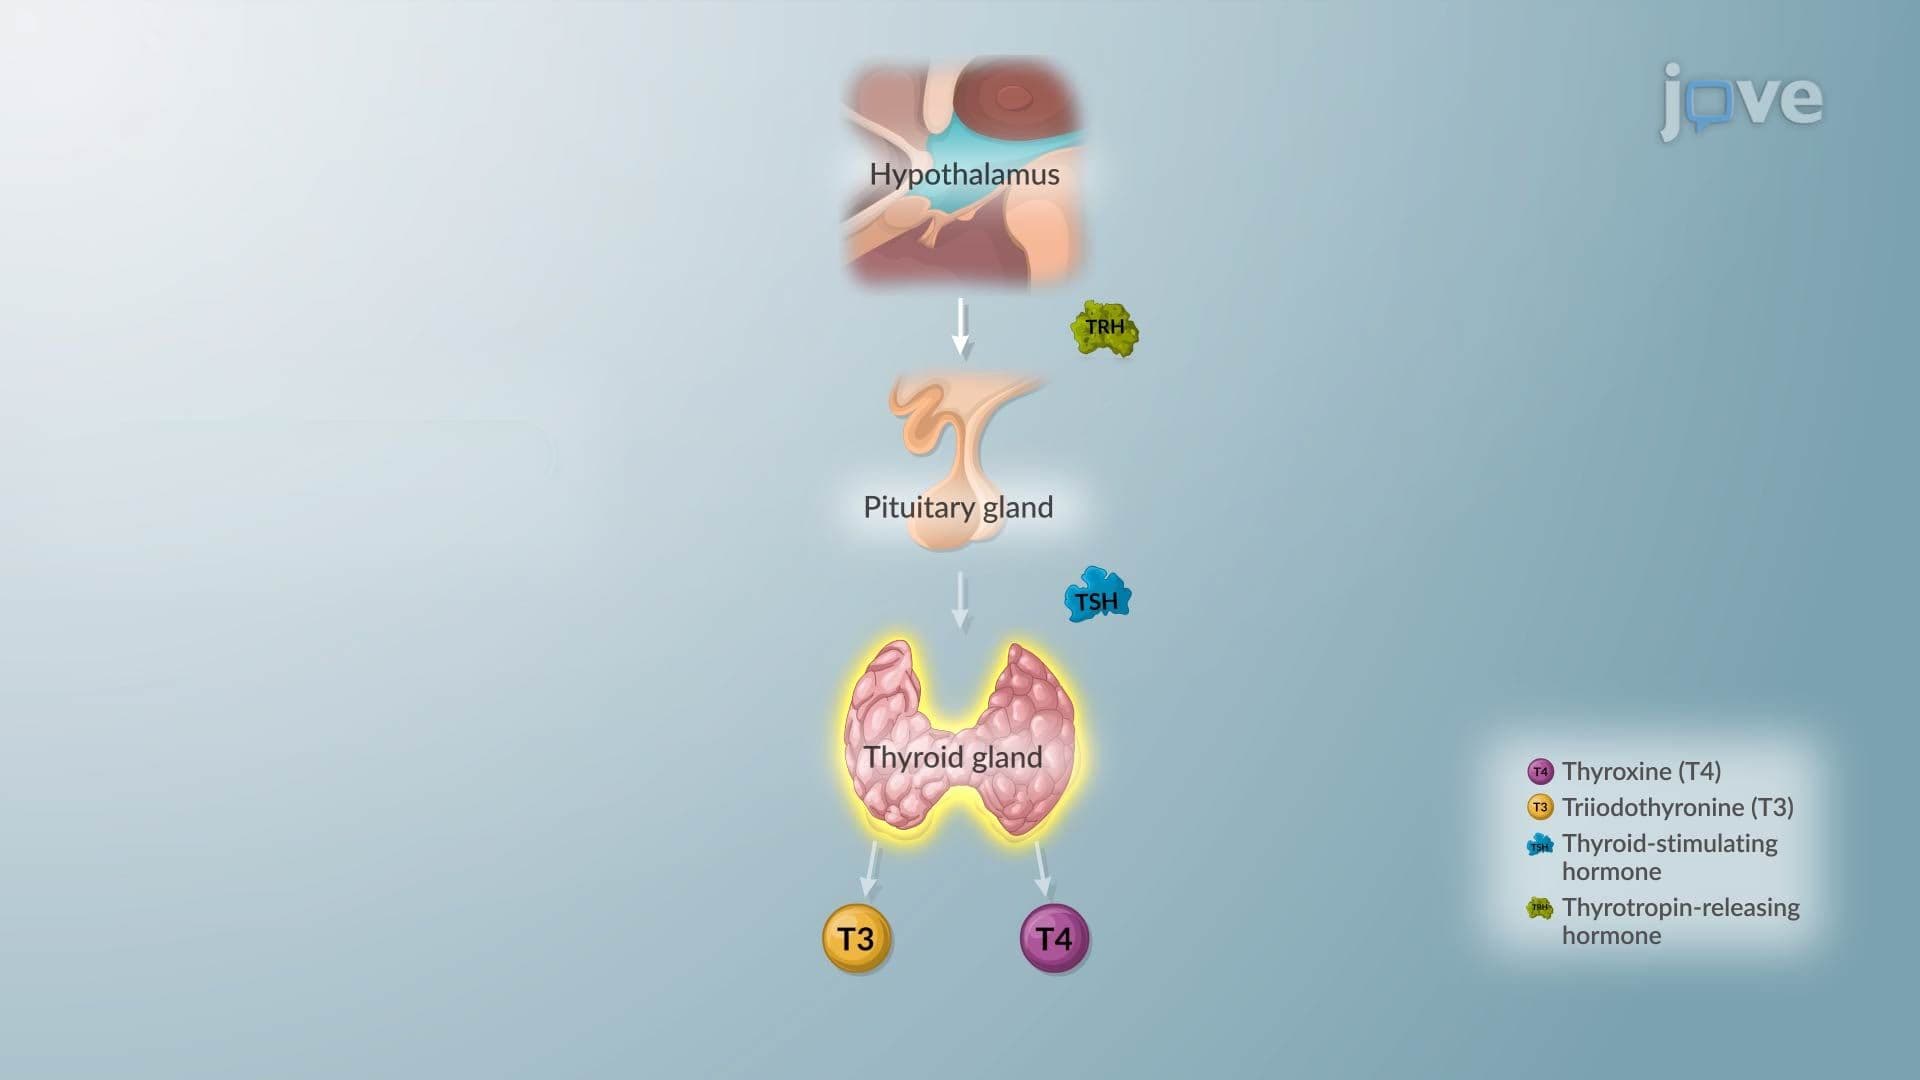
Upon reaching the thyroid gland, TSH stimulates the follicular cells' active uptake of iodide ions from the blood. The ions diffuse to the apical surface of the cells and are oxidized to iodine. The iodine is then...
 01:29
Drug Dosing: Infants and Children
 01:23
Hypothyroidism II: Pathophysiology
 01:24
Pharmacokinetics in Pediatric Patients: Drug Metabolism