Related Experiment Video
Updated: Oct 7, 2026
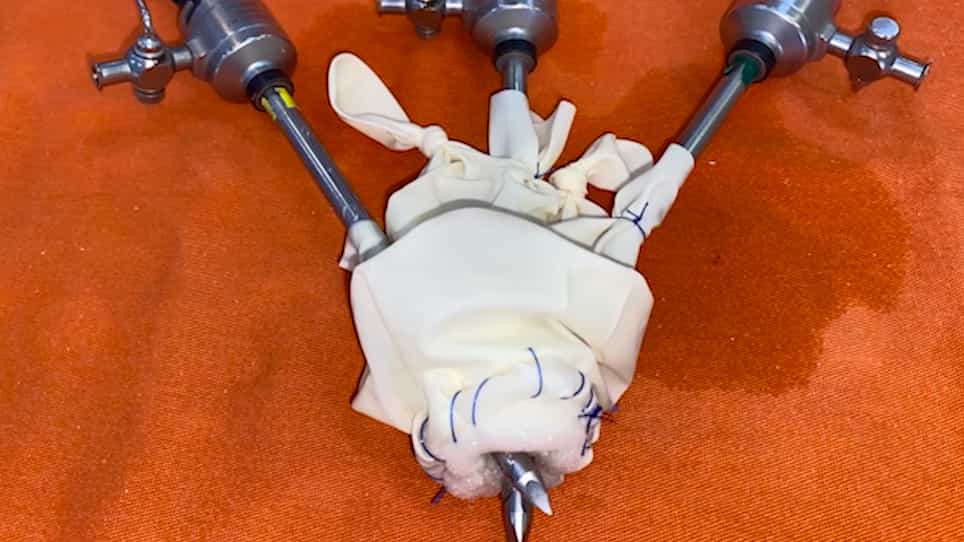
Low-Cost Single-Port (LoCoSP) Device for a Transcervical Approach in Minimally Invasive Transhiatal Esophagectomy
Published on: September 11, 2021
Transhiatal esophagectomy for treatment of benign and malignant esophageal disease
M B Orringer1, B Marshall, M D Iannettoni
1Section of General Thoracic Surgery, Department of Surgery, University of Michigan Medical Center, 2120 Taubman Health Care Center, 1500 E. Medical Center Drive, Box 0344, Ann Arbor, Michigan 48109, USA. morrin@umich.edu

Abstract:
Since our initial 1978 report, we have performed transhiatal esophagectomy (THE) in 1085 patients with intrathoracic esophageal disease: 285 (26%) benign lesions and 800 (74%) malignant lesions (4.5% upper, 22% middle, and 73.5% lower third/cardia). THE was possible in 97% of patients in whom it was attempted; reconstruction was performed at the same operation in all but six patients. The esophageal substitute was positioned in the original esophageal bed in 98%, stomach being used in 782 patients (96%) and colon in those with a prior gastric resection. Hospital mortality was 4%, with three deaths due to uncontrollable intraoperative hemorrhage. Major complications included anastomotic leak (13%), atelectasis/pneumonia prolonging hospitalization (2%), recurrent laryngeal nerve paralysis, chylothorax, and tracheal laceration (< 1% each). There were five reoperations for mediastinal bleeding within 24 hours of THE. Intraoperative blood loss averaged 689 ml. Altogether, 78% of the patients had no postoperative complications. Actuarial survival of the cancer patients mirrors that reported after transthoracic esophagectomy. Late functional results are good or excellent in 80%. Approximately 50% have required one or more anastomotic dilatations. With intensive preadmission pulmonary and physical conditioning, use of a side-to-side staple technique (which has reduced the cervical esophagogastric anastomotic leak rate to less than 3%), and postoperative epidural anesthesia, the need for an intensive care unit stay has been eliminated and the length of hospital stay was reduced to 7 days. We concluded that THE can be achieved in most patients requiring esophageal resection for benign and malignant disease and with greater safety and less morbidity than the traditional transthoracic approaches.

Related Concept Videos
 01:26
Esophageal Strictures-II: Clinical Features and Management
Healthcare providers should gather a comprehensive medical history and conduct a physical examination for diagnosis. If esophageal stricture is...
 01:21
Barrett Esophagus-II: Clinical Manifestations and Management
To diagnose Barrett's esophagus, healthcare providers often recommend an endoscopy for those showing symptoms of acid reflux. The procedure entails...
 01:30
Esophageal Strictures-I: Introduction
Etiology
The primary cause of esophageal strictures is long-standing gastroesophageal reflux disease (GERD), accounting for about 70 to 80% of adult cases. Chronic acid reflux can lead to injury and scarring of the esophageal lining, culminating in...
 01:28
Esophageal Perforation-II: Clinical Manifestations and Management
Clinical Manifestations:
 01:25
Hiatal Hernia
 01:22
Trachea
Anatomical Features:
Location: About half of the trachea is situated in the neck, anterior to the esophagus, and extends from the larynx (at the level of the...