
Clinical applications of wall-stress analysis in the pediatric intensive care unit
J A Courand1, J Marshall, Y Chang
1Department of Pediatric Critical Care Medicine, Massachusetts General Hospital, Boston, MA, USA.

Insights
Serial, noninvasive assessment of cardiac afterload and contractility reliably detects changes in cardiac function in unstable pediatric patients. This method aids in monitoring hemodynamic instability and response to treatment.
Area of Science:
- Pediatric Cardiology
- Critical Care Medicine
- Echocardiography
Background:
- Hemodynamic instability in critically ill children poses significant management challenges.
- Accurate, real-time assessment of cardiac function is crucial for optimizing treatment strategies.
Purpose of the Study:
- To evaluate the reliability of serial, noninvasive assessment of afterload, contractility, and Doppler-derived cardiac output in detecting variations in cardiac function among unstable pediatric patients.
- To establish the utility of these noninvasive measures in monitoring patient response to interventions.
Main Methods:
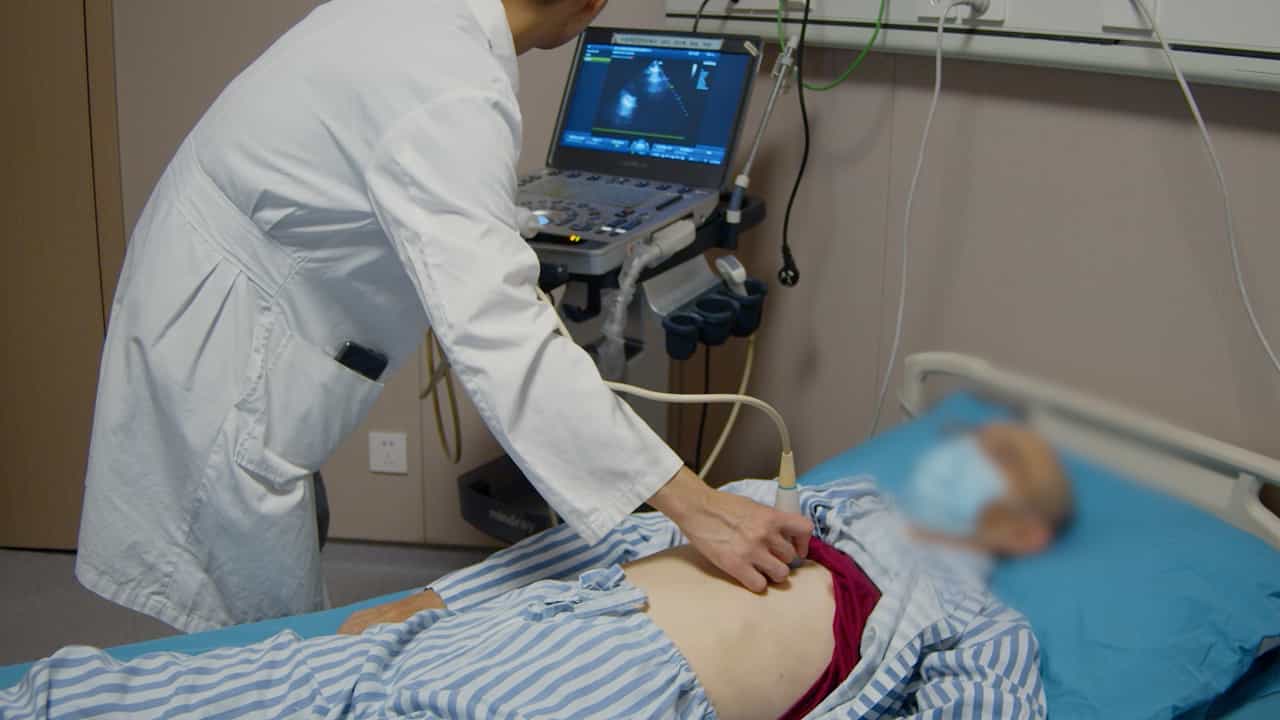
- Prospective, blinded clinical trial involving 14 critically ill pediatric patients in a pediatric intensive care unit.
- Serial echocardiograms were performed every 6 hours, generating 75 studies.
- Measurements included shortening fraction, cardiac index (CI), end-systolic wall stress (ESWS), and corrected velocity of circumferential shortening (Vcfc), analyzed via a modified stress-velocity relationship.
Main Results:
- A strong negative correlation between ESWS and Vcfc (p < .001) and a strong positive correlation between Vcfc and CI (p = .012) confirmed internal validity.
- Increased dopamine infusion correlated with decreased ESWS, increased Vcfc, and increased CI (p < .05).
- Noninvasive echocardiographic indices reliably detected patient deterioration, recovery, and response to dopamine, with urine output being the only correlating clinical index.
Conclusions:
- Wall-stress analysis of cardiac function is a safe and effective noninvasive method for mechanically ventilated pediatric patients.
- Vcfc and CI measurements demonstrated strong positive correlation, supporting internal validity.
- Noninvasive measures of afterload and contractility are valuable tools for monitoring cardiac function in critically ill children, guiding treatment adjustments and predicting outcomes.
Objective:
To determine whether serial, noninvasive assessment of afterload, contractility, and Doppler-derived cardiac output reliably detects variations in cardiac function in unstable pediatric patients.
Design:
Prospective, blinded clinical trial.
Setting:
The pediatric intensive care unit at Massachusetts General Hospital.
Patients:
Fourteen critically ill pediatric patients.
Interventions:
Pediatric patients meeting criteria for hemodynamic instability underwent serial echocardiograms every 6 hrs until they met exit criteria, generating 75 studies.
Measurements And Main Results:
Shortening fraction, cardiac index (CI), end-systolic wall stress (ESWS), and corrected velocity of circumferential shortening (Vcfc) were measured in each patient. Data points were plotted as a stress-velocity relationship, compared with published normal values, then correlated with changes in vital signs and pharmacologic interventions. Fourteen of 16 patients who were enrolled completed the study. A strong negative correlation between ESWS and Vcfc was confirmed (p < .001). As an internal measure of validity, Vcfc had a strong positive correlation with CI measurements (p = .012). An increase in dopamine infusion was associated with a fall in ESWS (p = .02), an increase in Vcfc (p = .03), and an increase in the CI as measured by Doppler (p = .035). The infusion of dopamine above renal perfusion levels moved patients from zones of normal or compensated contractility for afterload on a modified stress-velocity relationship to a zone of high contractility for afterload. Urine output was the only clinical index of cardiac function that had a significant correlation with the echocardiographic indices. Hemodynamically unstable patients followed similar patterns of deterioration and recovery on the modified stress-velocity graph. All surviving patients returned to a normal or compensated zone.
Conclusions:
Wall-stress analysis of cardiac function is easily and safely performed on mechanically ventilated pediatric patients with the production of consistently high-quality data. For internal validity, Vcfc and CI measurements were correlated and were strongly positive. Wall-stress indices reliably detected patient deterioration, recovery, and response to changes in dopamine infusion. Patients who failed to return to areas of normal or compensated levels of contractility and afterload did poorly in this study. Noninvasive measures of afterload and contractility appear useful for monitoring cardiac function of critically ill children in an intensive care setting.


Related Concept Videos
 01:04
Applications of Stress
The...
 01:15
Stress: General Loading Conditions
The shearing force, possessing potential directionality within the plane of the section, is simplified into two component forces running parallel to the x and y axes....
 01:24
Stress Concentrations
 01:23
Stresses under Combined Loadings
The process begins by slicing the tube at critical points and analyzing the internal forces and stress components at these sections, focusing on the centroid. Normal stresses, generated by axial forces and bending moments, are either compressive or tensile and vary across the section from...
 01:23
Components of Stress
Interestingly, the hidden cube faces also experience these stresses, equal and...