Related Experiment Video
Updated: Aug 12, 2026


Two Methods for Establishing Primary Human Endometrial Stromal Cells from Hysterectomy Specimens
Published on: May 23, 2014
Hormone replacement therapy and the endometrium
1Department of Histopathology, Royal Hallamshire Hospital, Sheffield S10 2JF, UK.

Abstract:
Modern hormone replacement therapy (HRT) regimens contain oestrogen and progestogen, given either in a cyclical or continuous combined manner. Most endometrial biopsies from women on sequential HRT show weak secretory features. Approximately 15% show proliferative activity, although this figure may be less if more than nine days of progestogen is given in each cycle. A small proportion will show an inactive or atrophic endometrium. Up to 50% of biopsies from women on continuous combined HRT contain minimal endometrial tissue for histopathological analysis: this correlates well with an atrophic endometrium with no appreciable pathology. Of the 50% with more substantial material, approximately one half will show endometrial atrophy, and one half will show weak secretory features. Proliferative, menstrual, and pseudodecidual changes are rare. Approximately 20% of women given unopposed oestrogen for one year develop endometrial hyperplasia. The relative risk of endometrial carcinoma is two to three. This is dramatically reduced by the addition of progestogen to the regimen, but cyclical progestogen as part of a sequential HRT regimen does not completely eliminate the risk of carcinoma. The prevalence of endometrial hyperplasia associated with sequential HRT is 5.4%, and that of atypical hyperplasia (endometrial intraepithelial neoplasia) is 0.7%. Continuous combined HRT is not associated with the development of hyperplasia or carcinoma, and may normalise the endometrium of women who have developed complex hyperplasia on sequential HRT. The probability of a histopathologist finding clinically relevant pathology in an endometrial biopsy specimen of a patient on HRT is low and is more likely to be a manifestation of pre-existing disease.

Related Concept Videos
 01:22
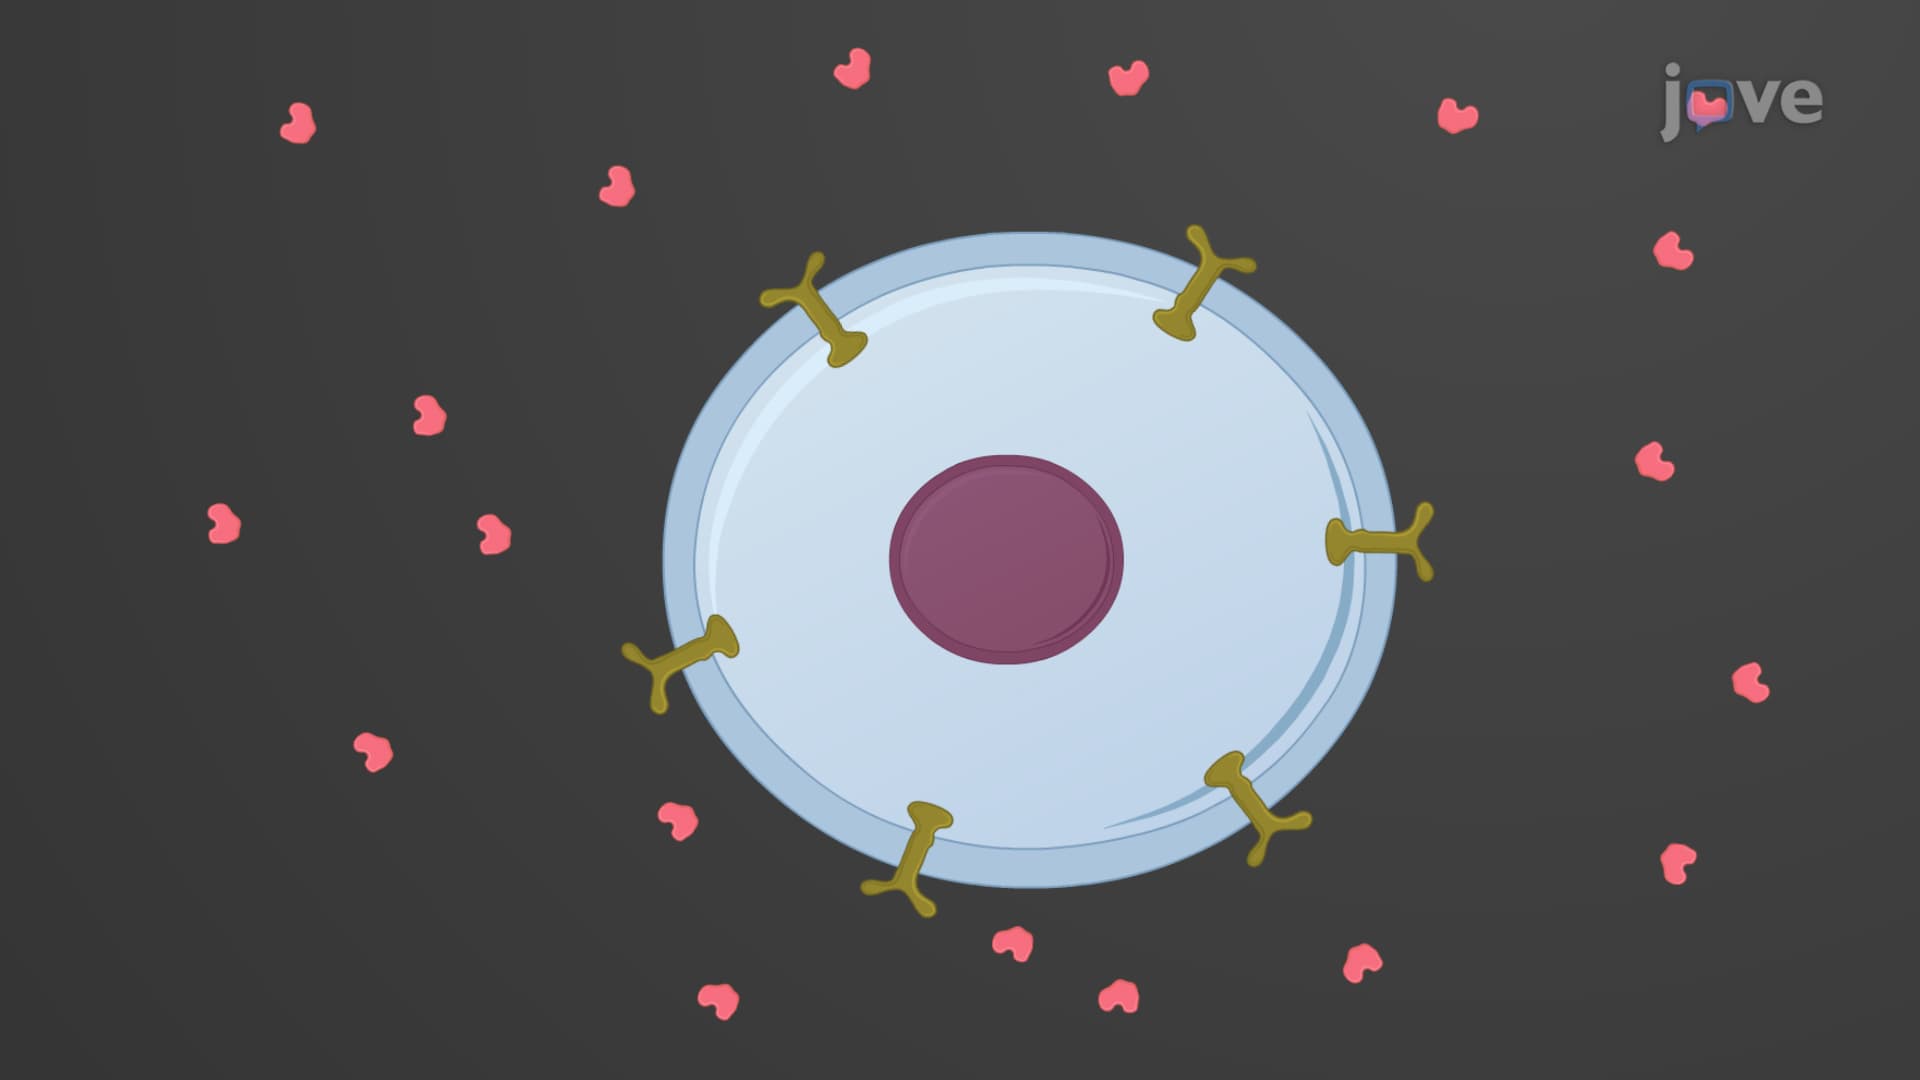
Target Cell Response to Hormones
Notably, the cellular response can be regulated by altering the number of receptors expressed in the cell. For example, prolonged exposure to elevated hormone levels results in a gradual decline or down-regulation in the number of receptors for that specific hormone on the cell surface. Conversely, in response to low hormone levels, cells may use up-regulation, producing an...
 01:22
Hormonal Regulation of the Menstrual Cycle
At puberty, GnRH begins a pulsatile release pattern, which triggers the anterior pituitary gland to secrete follicle-stimulating hormone (FSH) and luteinizing hormone (LH). The frequency and amplitude of GnRH pulses vary across the menstrual cycle, with faster pulses favoring LH release and slower pulses favoring FSH release.
 01:27
Ovarian Cycle
 01:30
Hormonal Control of the Ovarian Cycle
Before puberty, the hypothalamus releases GnRH in a low frequency, low amplitude pulsatile manner. This along with the immature hypothalamic-pituitary-gonadal axis activity, results in low estrogen levels and the absence of a fully functional ovarian cycle. At puberty, GnRH secretion increases in both frequency and...
 01:19
The Menstrual Cycle
The menstrual phase occurs from days 1 to 5 and involves the shedding of the stratum functionalis, as a uterine...
 01:20
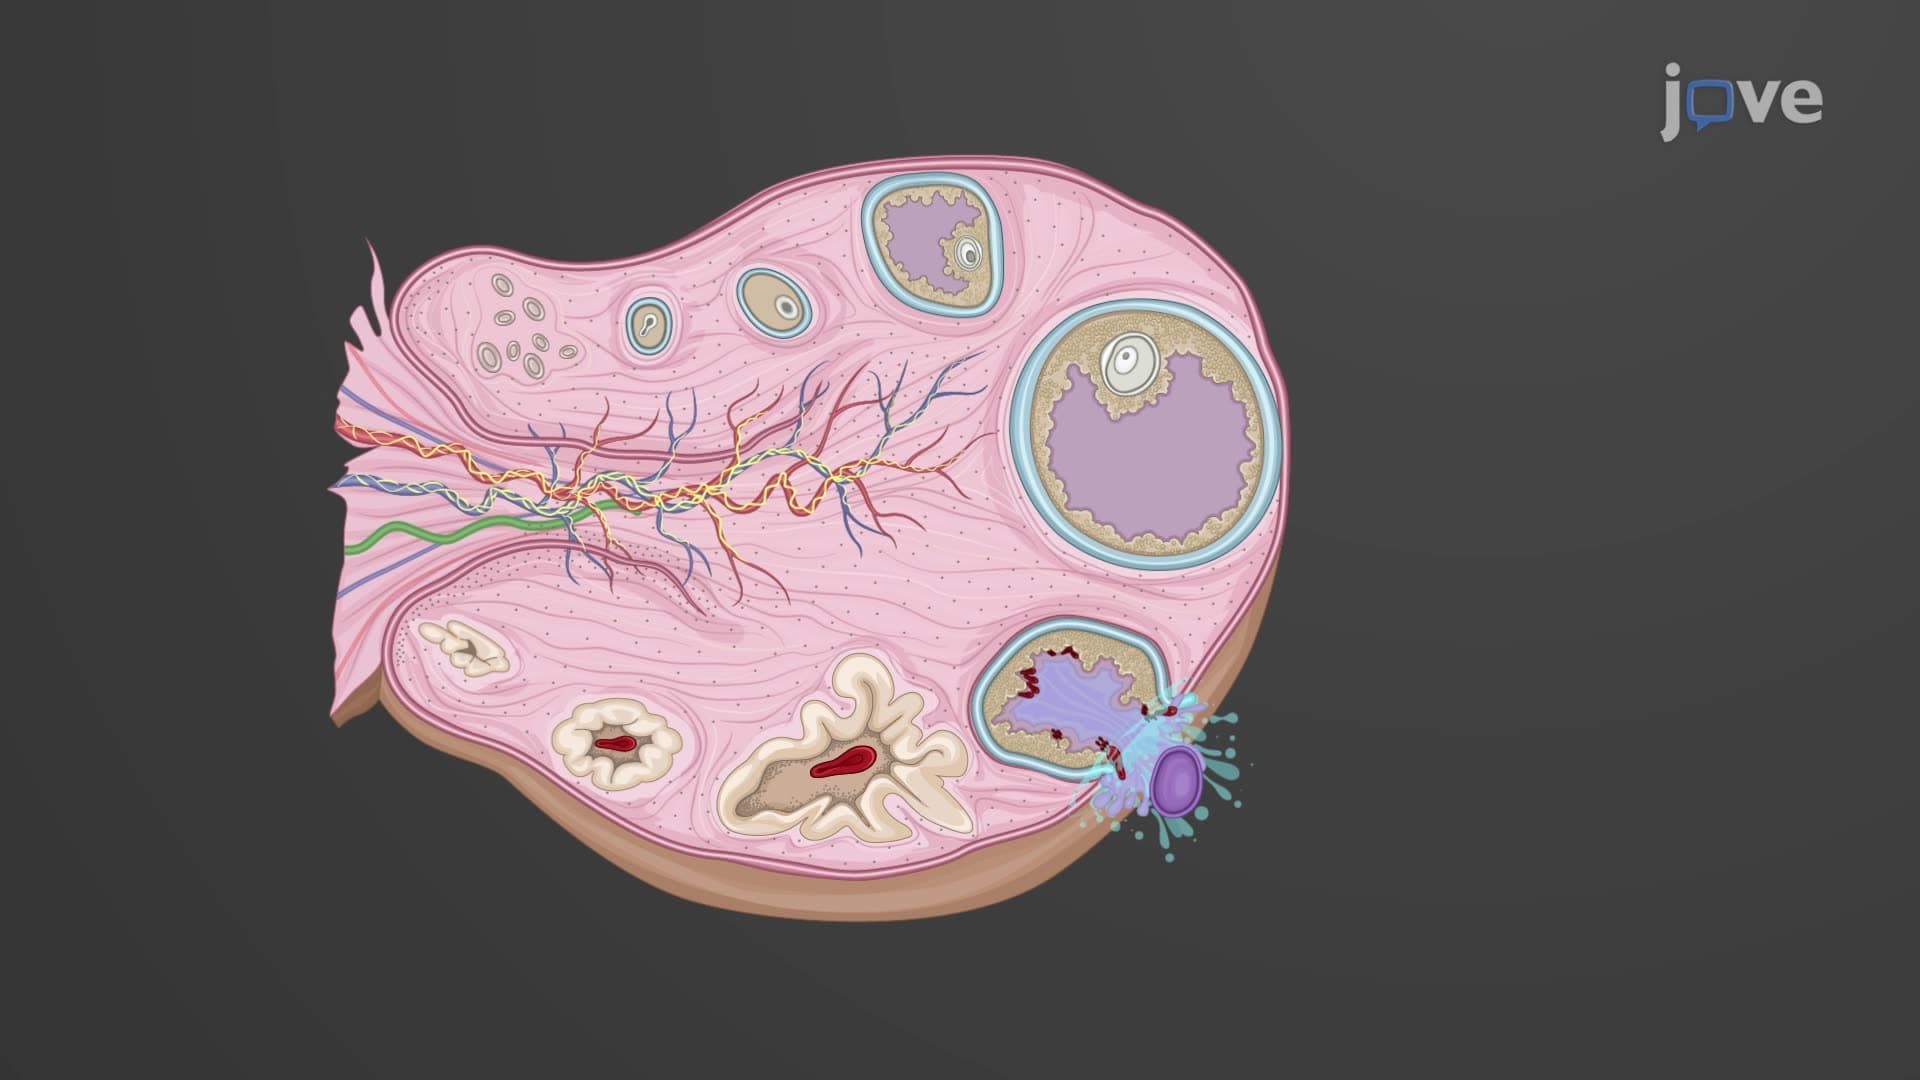
Proliferative Phase
Notably, the stratum basale, the basal layer of the endometrium, including the basal parts of the uterine glands, remains unaffected by menstruation. Stem cells in this layer undergo mitosis, regenerating the stratum functionalis and thickening the...