Apoptosis and changes in contractile protein pattern in the skeletal muscle in heart failure
Related Experiment Video
Updated: Oct 7, 2026

Analysis of Cardiac Contractile Dysfunction and Ca2+ Transients in Rodent Myocytes
Published on: May 25, 2022
G Vescovo1, G B Ambrosio, L Dalla Libera
1Divisione Medica, Ospedale di Adria (Ro), Italy.

Insights
Chronic heart failure (CHF) reduces exercise capacity due to skeletal muscle atrophy and myosin heavy chain (MHC) shifts. Treatments targeting these factors may improve patient outcomes.
Area of Science:
- Cardiology
- Skeletal Muscle Physiology
- Molecular Biology
Background:
- Chronic heart failure (CHF) significantly impairs exercise capacity.
- Reduced exercise capacity in CHF is linked to skeletal muscle changes, including atrophy and myosin heavy chain (MHC) shifts.
- Skeletal muscle apoptosis is increasingly recognized as a contributor to CHF pathophysiology.
Purpose of the Study:
- To investigate the relationship between skeletal muscle apoptosis, MHC composition, and exercise intolerance in CHF.
- To explore the role of TNFalpha and sphingolipids in CHF-induced skeletal muscle apoptosis.
- To evaluate the efficacy of angiotensin-converting enzyme inhibitors (ACEi) and angiotensin II receptor blockers (ARBs) in preventing these detrimental changes.
Main Methods:
- Utilized a monocrotaline-induced rat model of right-sided heart failure.
- Analyzed skeletal muscle apoptosis, MHC expression, and circulating TNFalpha and sphingosine levels in rats and CHF patients.
- Correlated exercise capacity, muscle atrophy, and MHC composition with CHF severity.
Main Results:
- CHF severity correlated positively with skeletal muscle apoptosis and circulating sphingosine levels.
- Increased skeletal muscle apoptosis was associated with muscle atrophy and exercise limitation in CHF patients.
- A shift towards 'fast' MHC isoforms in skeletal muscle correlated with CHF severity and premature muscle fatigue.
- ACE inhibitors and ARBs demonstrated a preventative effect on MHC shifts and apoptosis.
Conclusions:
- Skeletal muscle apoptosis and altered MHC composition are key contributors to exercise intolerance in CHF.
- TNFalpha and sphingolipids may mediate CHF-related skeletal muscle apoptosis.
- ACEi and ARBs show potential for mitigating skeletal muscle pathology in CHF, improving exercise capacity.
Abstract:
Chronic heart failure is characterized as a clinical disorder by exercise intolerance. There are two factors that are independently responsible for the reduced exercise capacity: (a) a shift from myosin heavy chain 1 (MHC1) to MHC2a and MHC2b and (b) muscle atrophy. We have demonstrated, both in experimental models of heart failure and in man, that the more severe the heart failure, the greater the magnitude of skeletal muscle apoptosis. In the monocrotaline treated rat, that develops a severe right-sided heart failure, the increased number of apoptotic nuclei was paralleled by increasing levels of circulating TNFalpha. In agreement with some recent observations showing that sphingolipids can mediate programmed cell death, we found that in animals with heart failure and high number of apoptotic nuclei, circulating levels of sphingosine were significantly increased. In a study conducted in patients with heart failure we found a correlation between exercise capacity limitation and skeletal myocytes apoptosis. There was also a correlation between degree of muscle atrophy and magnitude of apoptosis. The shift in MHCs, although with a different mechanism, is also responsible for the reduced exercise capacity in these patients. In fact there is a strong correlation between indices of severity of CHF and MHC composition. Muscle fatigue, appears earlier in patients that have a greater skeletal muscle expression of 'fast' MHCs. We have also demonstrated that MHCs shift and apoptosis can be prevented by using angiotensin II converting enzyme inhibitors and angiotensin II receptor blockers.


Related Concept Videos
 01:17
Pathophysiology of Heart Failure
 01:29
Heart Failure II: Pathophysiology
 01:27
Heart Failure I: Introduction
 01:13
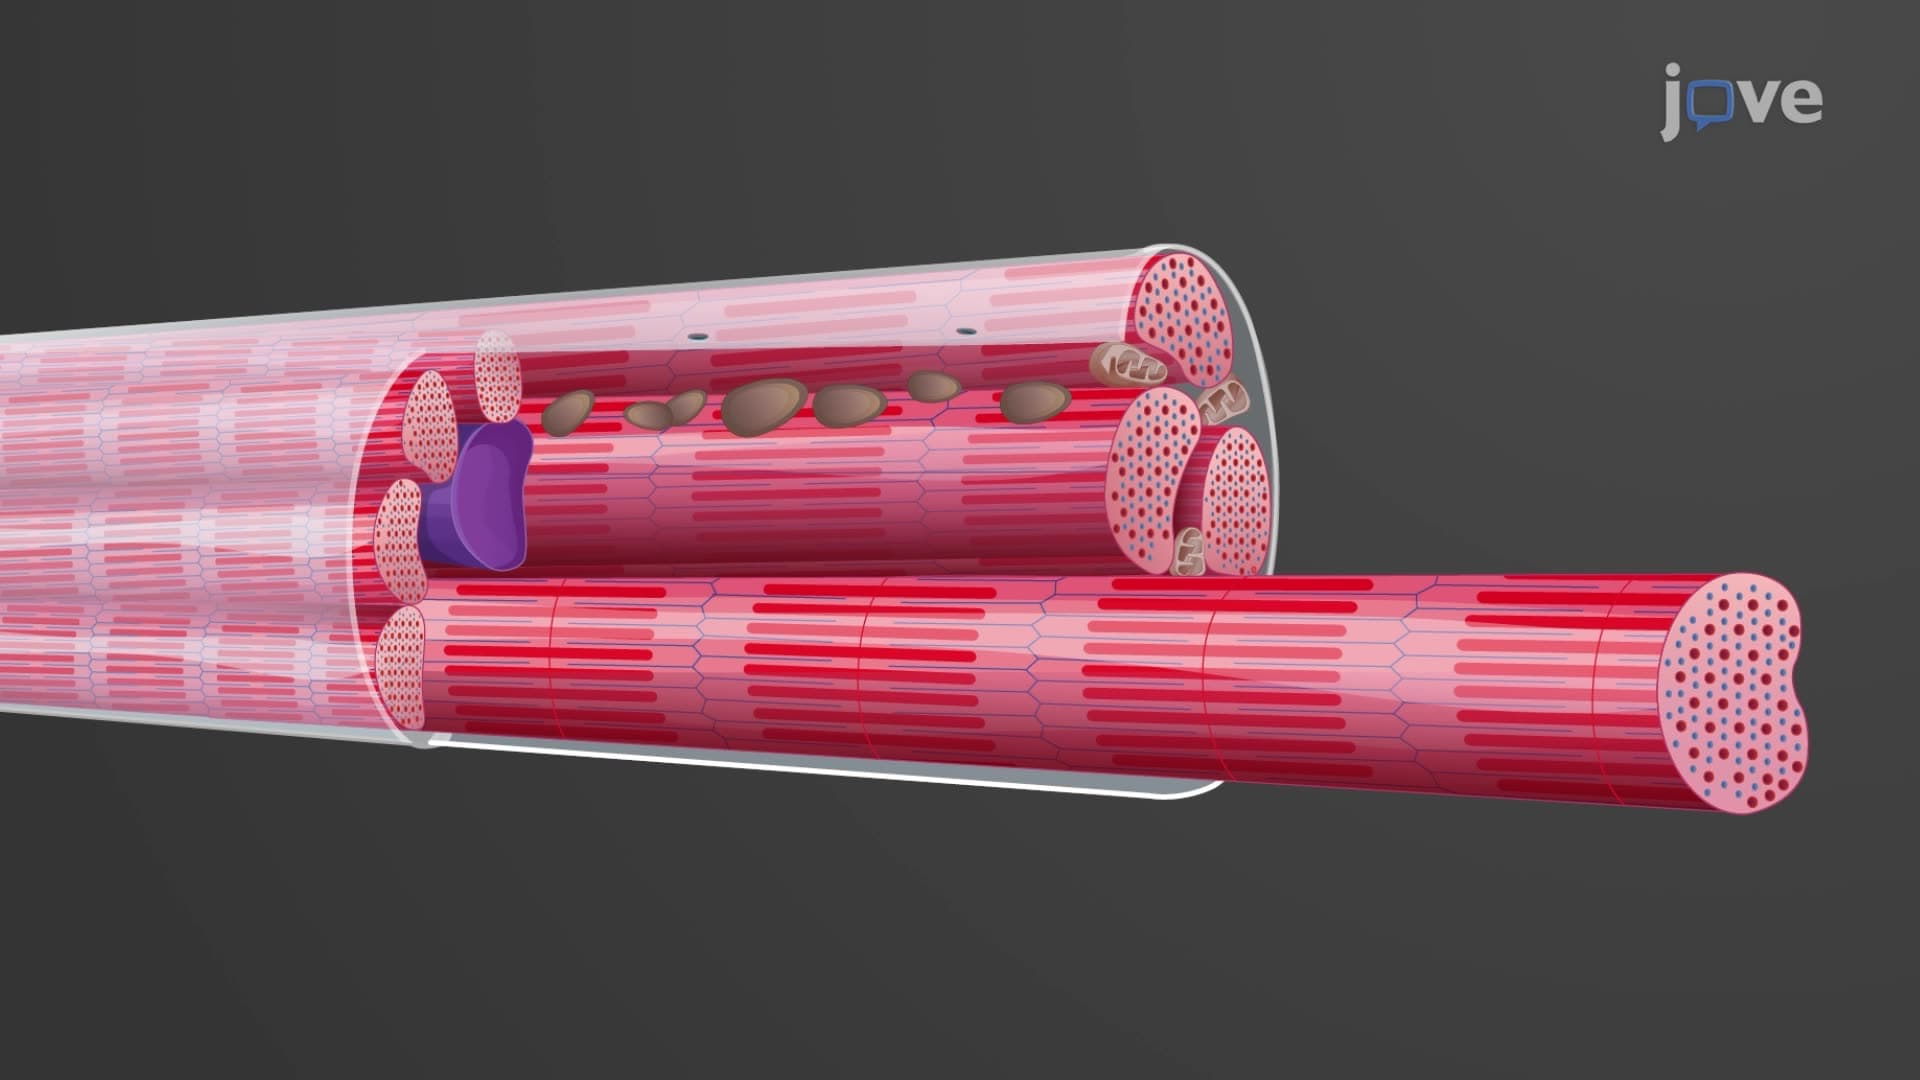
Structure of Cardiac Muscles
Compared to skeletal muscles, cardiac muscle cells are small and mostly have a single nucleus. Additionally, they are usually...
 01:29
Cardiomyopathy III: Hypertrophic Cardiomyopathy
 01:26
Heart Failure Drugs: Inotropic Agents