Related Experiment Video
Updated: Aug 6, 2026


Single-cell Analysis of Immunophenotype and Cytokine Production in Peripheral Whole Blood via Mass Cytometry
Published on: June 26, 2018
The protean nature of Whipple's disease includes multiorgan arteriopathy
1University of Texas Medical Branch, 301 University Boulevard, Galveston, Texas 77555-0175, USA.

Knowledge about the arterial abnormalities in Whipple's disease can be useful for our better understanding of both Whipple's disease and the more general question of pathogenesis of atherosclerosis. There are several notable morphological features of Whipple's arteriopathy. First, it appears to involve primarily arteries one millimeter or less in diameter. Second, there is very little evidence of inflammation accompanying invasion of any or all three layers of the walls of affected arteries, and there is almost no evidence of local attraction of platelets to these sites of arterial injury. Third, the nature of arterial injury appears to be one of slow progression. The few sites of actual arteritis are most likely attributable to some other coinciding microbial organism not yet identified. Although the arteriopathy in Whipple's disease is seen mainly in small arteries (the aorta is a notable exception), their significance can be illustrated by consideration of this fact as it applies to the coronary circulation (and probably the arteries of all other organs). In the heart these small arteries comprise almost the entire collateral circulation, the principal blood supply to each component of the conduction system, and most pragmatically, these small arteries represent the terminal distribution of every larger epicardial artery. Small arteries are important. The "cardiomyopathy" so often a feature of Whipple's disease (very much including his original case) is most logically attributable to recurring bouts of focal ischemia and subsequent focal fibrosis ending in myocardial incompetence. However, direct bacillary invasion of cardiac myocytes (22) also occurs. In lamina propria of jejunum, there is also arteriopathy, as there is in brain, lung, kidney, spleen, liver, gall bladder, rectum, stomach, lymph nodes and testis. It is likely that no organ in the body is spared. There is growing evidence that a wide variety of chronic infections (occurring concomitantly or sequentially) may participate in the early pathogenesis of human arterial disease, including atherosclerosis. Given that the coronary plaque represents the cumulative end result of countless earlier injuries and responses, the plaque is not the site to seek evidence of initial pathogenesis although understanding the behavior of coronary plaques is eventually of considerable clinical importance. In the context of original events in pathogenesis, the Whipple bacillus now deserves inclusion in the "total pathogen burden" concept, as it relates not only to coronary disease but to all aspects of atherosclerosis and even other forms of arteriopathy.
Knowledge about the arterial abnormalities in Whipple's disease can be useful for our better understanding of both Whipple's disease and the more general question of pathogenesis of atherosclerosis. There are several notable morphological features of Whipple's arteriopathy. First, it appears to involve primarily arteries one millimeter or less in diameter. Second, there is very little evidence of inflammation accompanying invasion of any or all three layers of the walls of affected arteries, and there is almost no evidence of local attraction of platelets to these sites of arterial injury. Third, the nature of arterial injury appears to be one of slow progression. The few sites of actual arteritis are most likely attributable to some other coinciding microbial organism not yet identified. Although the arteriopathy in Whipple's disease is seen mainly in small arteries (the aorta is a notable exception), their significance can be illustrated by consideration of this fact as it applies to the coronary circulation (and probably the arteries of all other organs). In the heart these small arteries comprise almost the entire collateral circulation, the principal blood supply to each component of the conduction system, and most pragmatically, these small arteries represent the terminal distribution of every larger epicardial artery. Small arteries are important. The "cardiomyopathy" so often a feature of Whipple's disease (very much including his original case) is most logically attributable to recurring bouts of focal ischemia and subsequent focal fibrosis ending in myocardial incompetence. However, direct bacillary invasion of cardiac myocytes (22) also occurs. In lamina propria of jejunum, there is also arteriopathy, as there is in brain, lung, kidney, spleen, liver, gall bladder, rectum, stomach, lymph nodes and testis. It is likely that no organ in the body is spared. There is growing evidence that a wide variety of chronic infections (occurring concomitantly or sequentially) may participate in the early pathogenesis of human arterial disease, including atherosclerosis. Given that the coronary plaque represents the cumulative end result of countless earlier injuries and responses, the plaque is not the site to seek evidence of initial pathogenesis although understanding the behavior of coronary plaques is eventually of considerable clinical importance. In the context of original events in pathogenesis, the Whipple bacillus now deserves inclusion in the "total pathogen burden" concept, as it relates not only to coronary disease but to all aspects of atherosclerosis and even other forms of arteriopathy.


Related Concept Videos
 01:24
Chronic Pancreatitis I: Introduction
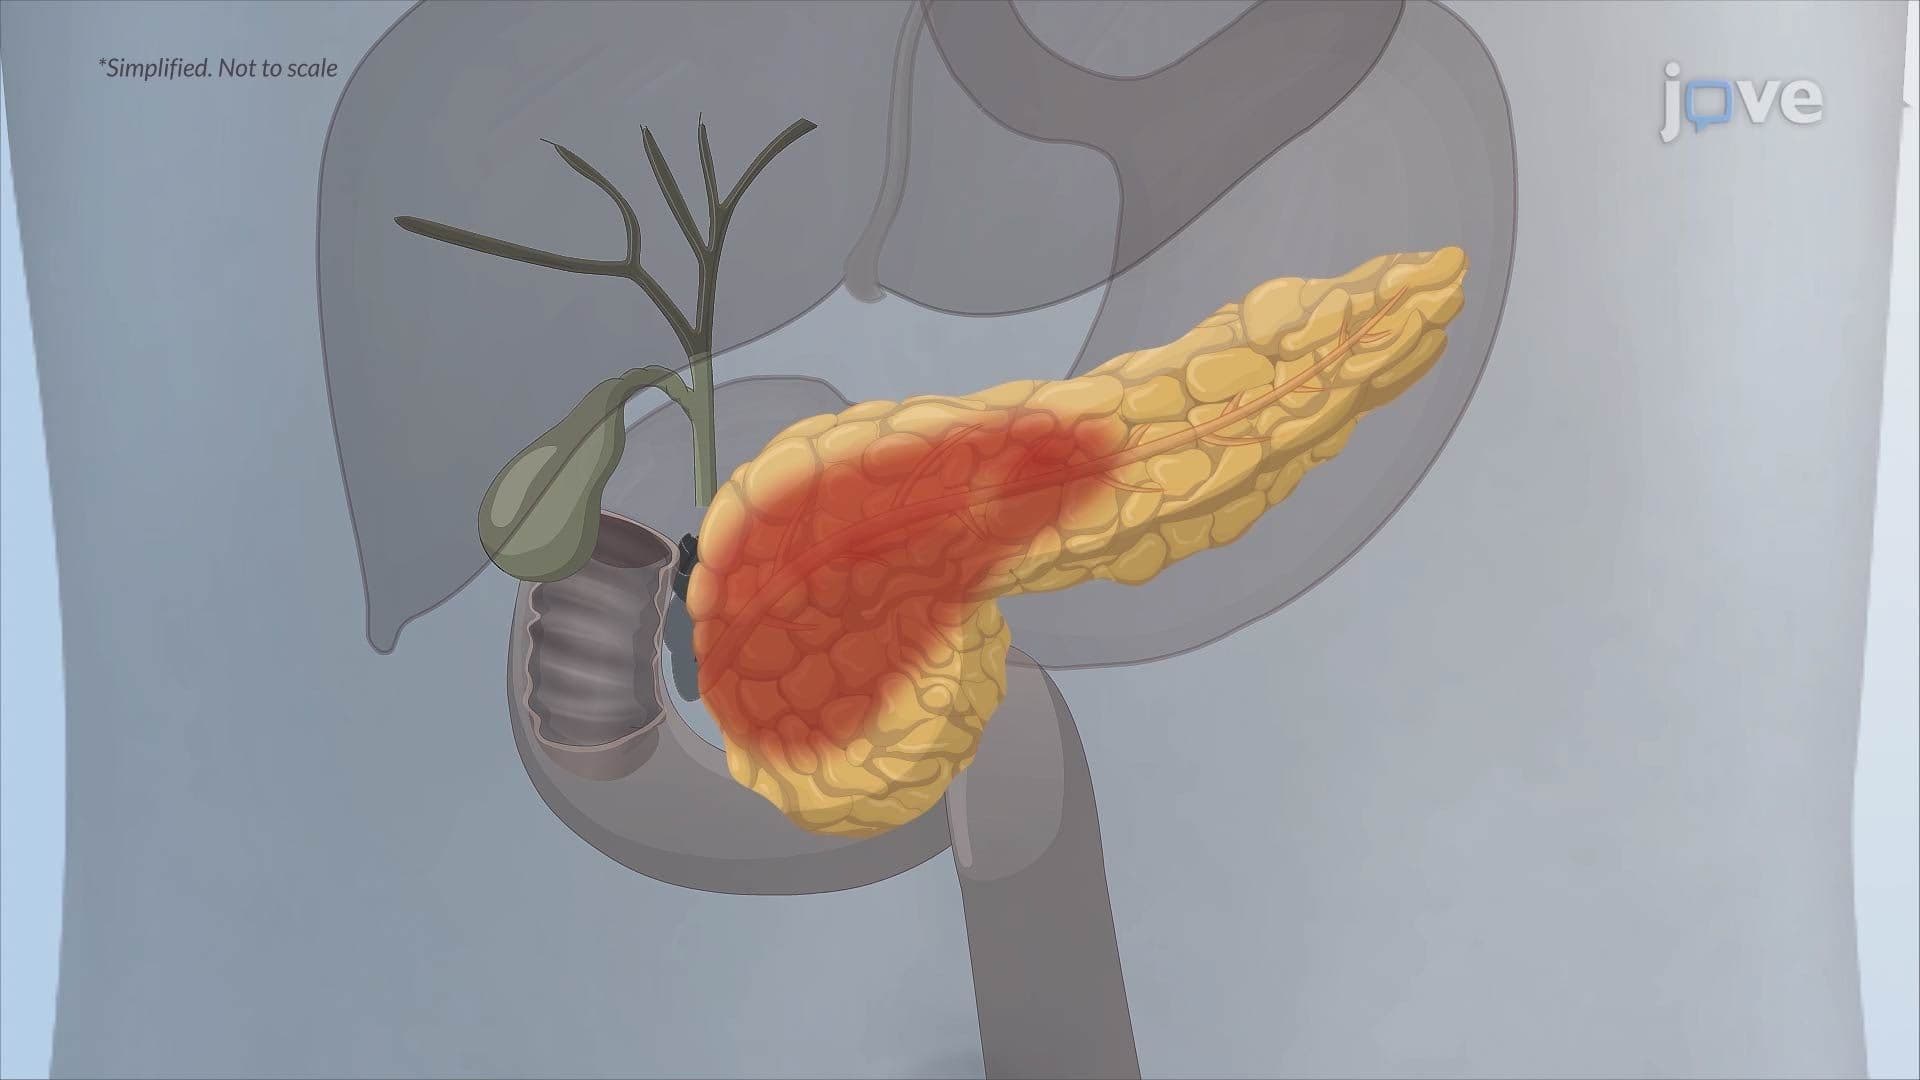
Pancreatitis is the inflammation of the pancreas, which occurs when the immune system becomes active and causes swelling, pain, and disruptions in organ function. Pancreatitis can manifest as either an acute or chronic condition.
Acute pancreatitis arises suddenly and lasts for a brief duration, while chronic pancreatitis is a long-term affliction...
 01:23
Rheumatic Heart Disease I: Introduction
 01:30
Peripheral Artery Disease I: Introduction
 01:25
Inflammatory Bowel Disease III: Crohn's Disease
 01:25
Chronic Pancreatitis I: Introduction
 01:21
Chronic Pancreatitis II: Pathophysiology