Newer neuromuscular blocking agents: how do they compare with established agents?
Related Experiment Video
Updated: Oct 5, 2026

Stimulated Single Fiber Electromyography (SFEMG) for Assessing Neuromuscular Junction Transmission in Rodent Models
Published on: March 8, 2024
H J Sparr1, T M Beaufort, T Fuchs-Buder
1Department of Anaesthesiology and Critical Care Medicine, The Leopold-Franzens-University of Innsbruck, Austria. harald.j.sparr@uibk.ac.at

Abstract:
Rapacuronium bromide (rapacuronium; ORG-9487) is a nondepolarising muscle relaxant (NMBA) with a low potency [90% effective dose (ED90) 1 mg/kg], which to some extent is responsible for its rapid onset of action. Because of the high plasma clearance (5.3 to 11.1 mg/kg/min) of rapacuronium, its clinical duration of action following single bolus doses up to 2 mg/kg in adults is short (i.e. <20 minutes). Rapacuronium forms a pharmacologically active 3-desacetyl metabolite, ORG-9488, which may contribute to a delay in spontaneous recovery after repeat bolus doses or infusions. After rapacuronium 1.5 mg/kg clinically acceptable intubating conditions are achieved within 60 to 90 seconds in the majority of adult and elderly patients undergoing elective anaesthesia. However, in a rapid-sequence setting. intubating conditions are less favourable after rapacuronium 1.5 to 2.5 mg/kg than after succinylcholine. The most prominent adverse effects of rapacuronium (tachycardia, hypotension and bronchospasm) are dose-related, and in particular pulmonary adverse effects are observed more frequently under conditions of a rapid-sequence induction in adults. Therefore, it seems worthwhile to consider only doses of rapacuronium < or = 1.5 mg/kg to facilitate rapid tracheal intubation, and to use succinylcholine or rocuronium rather than rapacuronium in a rapid-sequence setting. Rapacuronium, however, is a suitable alternative to mivacurium chloride (mivacurium) and succinylcholine for short procedures (e.g. ambulatory anaesthesia). Rocuronium bromide (rocuronium) is a relatively low-potent, intermediateacting NMBA. Its main advantage is the rapid onset of neuromuscular block whereby good or excellent intubating conditions are achieved within 60 to 90 seconds after rocuronium 0.6 mg/kg (2 x ED95), and within 60 to 180 seconds after smaller doses (1 to 1.5 x ED95). Larger doses of rocuronium (> or = 1 mg/kg) seem to be suitable for rapid-sequence induction under relatively light anaesthesia. However, it is still a matter of controversy whether, in the case of an unanticipated difficult intubation, the long duration of rocuronium administered in such large doses outweighs the many adverse effects of succinylcholine. Rocuronium has mild vagolytic effects and does not release histamine, even when administered in large doses. Rocuronium is primarily eliminated via the liver and its pharmacokinetic profile is similar to that of vecuronium bromide (vecuronium). Unlike vecuronium, rocuronium has no metabolite. Cisatracurium besilate (cisatracurium), the IR-cis, 1'R-cis isomer of atracurium besilate (atracurium) is approximately 4 times more potent than atracurium. The onset time of cisatracurium is significantly slower than after equipotent doses of atracurium. The recommended intubating dose is 0.15 to 0.2 mg/kg (3 to 4 times ED95). Over a wide range of clinically relevant doses the recovery properties of cisatracurium are affected by neither the size of the bolus dose nor by the duration of infusion. Unlike atracurium, cisatracurium does not trigger histamine release. Like atracurium, cisatracurium undergoes Hofmann elimination. In contrast to atracurium, cisatracurium does not undergo hydrolysis by nonspecific plasma esterases. Moreover, about 77% of the drug is cleared by organ-dependent mechanisms.
More Related Videos
 07:16
Methods for the Discovery of Novel Compounds Modulating a Gamma-Aminobutyric Acid Receptor Type A Neurotransmission
Published on: August 16, 2018
 07:09
Subcutaneous Administration of Muscarinic Antagonists and Triple-Immunostaining of the Levator Auris Longus Muscle in Mice
Published on: September 8, 2011
Related Concept Videos
 01:17
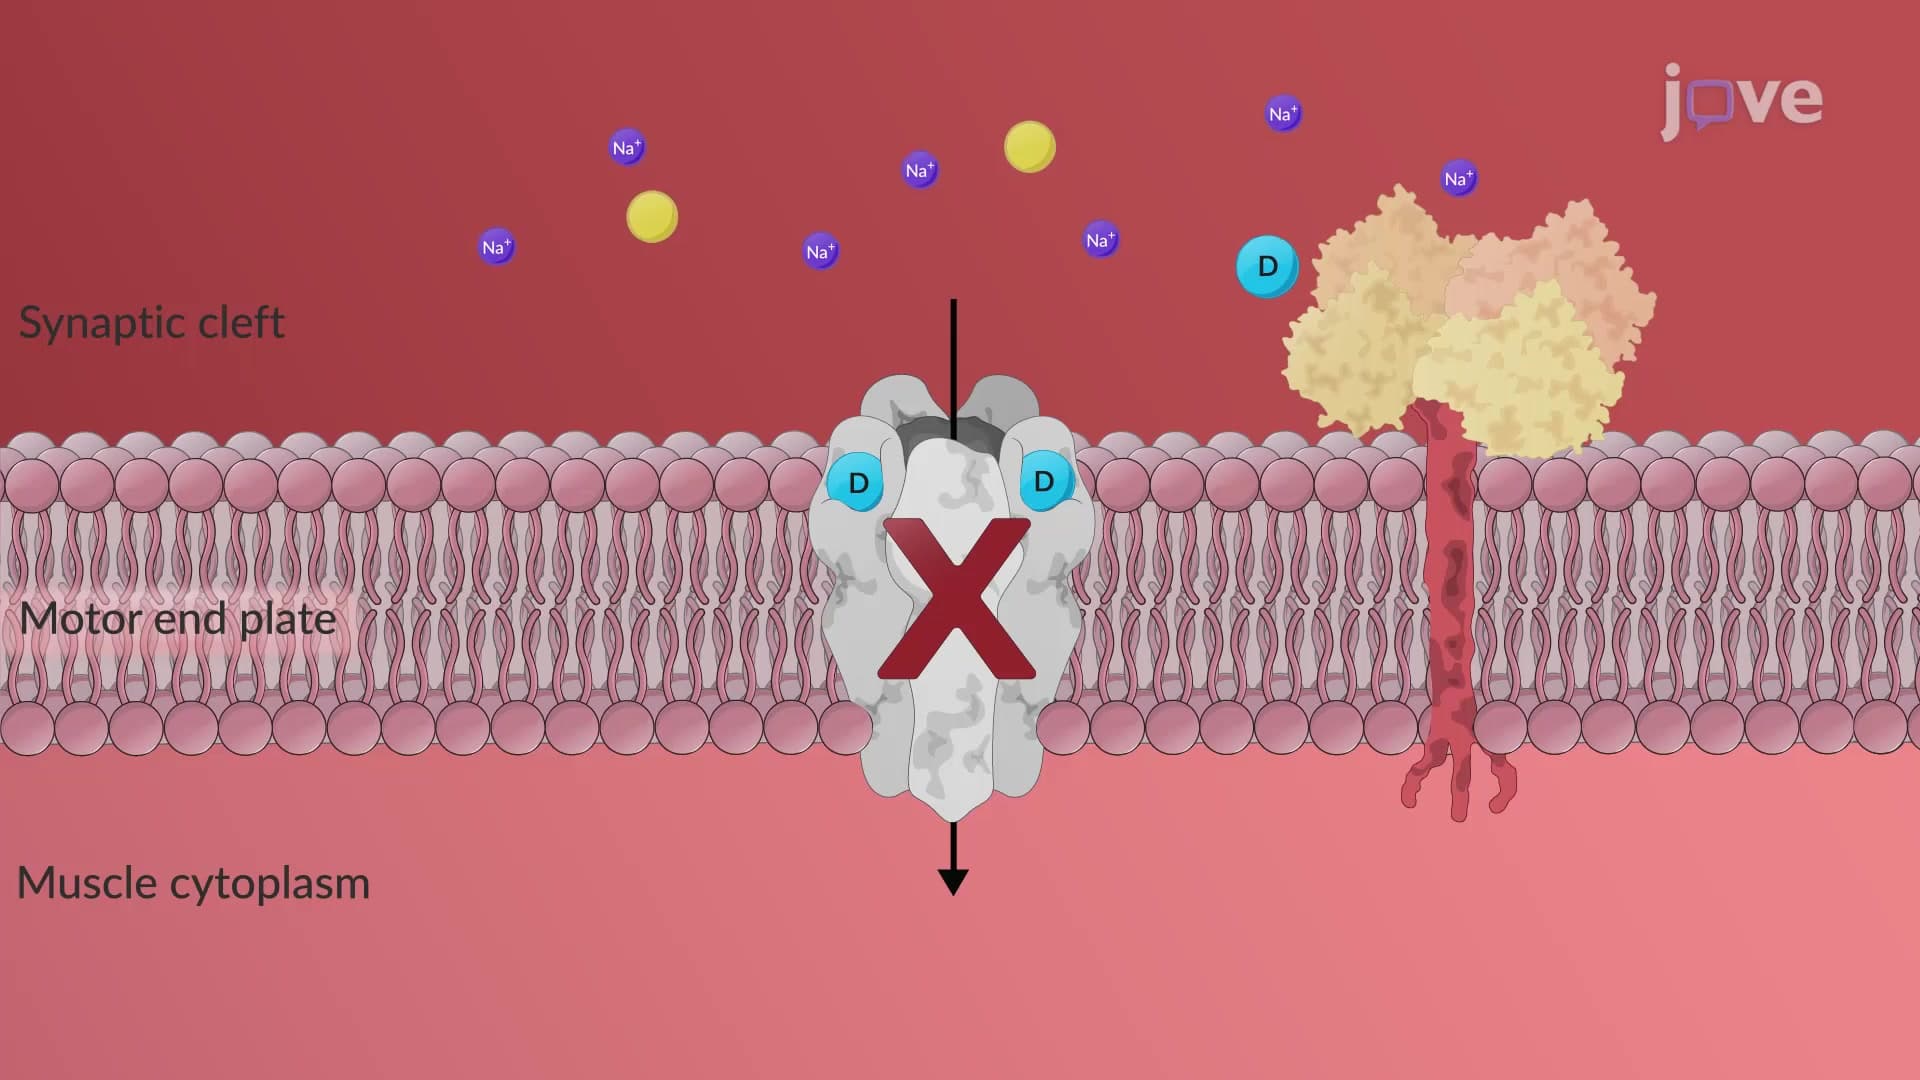
Nondepolarizing (Competitive) Neuromuscular Blockers: Mechanism of Action
Competitive antagonists prevent acetylcholine from binding to its receptor, inhibiting membrane depolarization. Without conformational changes or intrinsic...
 01:11
Nondepolarizing (Competitive) Neuromuscular Blockers: Pharmacokinetics
Instead, they are transported by the blood to different tissues. Muscles with a greater blood supply (arteries) and blood flow receive more...
 01:27
Nondepolarizing (Competitive) Neuromuscular Blockers: Pharmacological Actions
Although all competitive neuromuscular blockers are designed...
 01:28
Depolarizing Blockers: Mechanism of Action
Succinylcholine is the most commonly used depolarizing blocker. Chemically, it constitutes two molecules of acetylcholine joined together by an acetate methyl group. They act on the receptors in the same way as acetylcholine. Because succinylcholine...
 01:28
Drugs Acting on Autonomic Ganglia: Blockers
 01:28
Classification of Skeletal Muscle Relaxants
Peripherally acting skeletal muscle relaxants interfere with the neurotransmission at the neuromuscular end plate to induce paralysis during...