Related Experiment Video
Updated: Aug 23, 2026
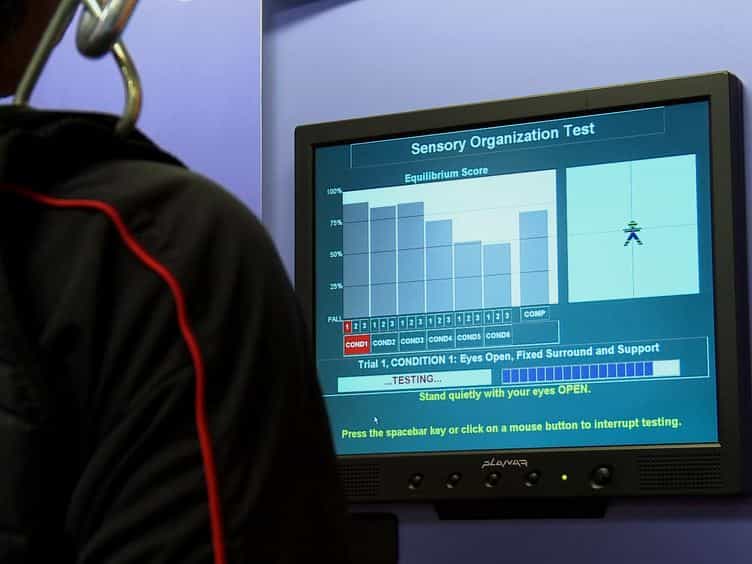

Computerized Dynamic Posturography for Postural Control Assessment in Patients with Intermittent Claudication
Published on: December 11, 2013
Intermittent claudication: magnitude of the problem, patient evaluation, and therapeutic strategies
1Department of Surgery, Temple University School of Medicine, Temple University Hospital, Philadelphia, Pennsylvania 19140, USA.

Abstract:
Intermittent claudication (IC), the symptom of exercise-induced muscle ischemia of peripheral arterial disease (PAD), afflicts and limits the activities of a significant number of patients. Incidence and prevalence of IC depends on the population studied and the diagnostic instruments used. In large studies, prevalence has ranged from 3% to 10%, with a sharp increase in those aged > or =70 years. Over the next 20 years, the total number of patients affected is expected to increase significantly due to anticipated demographic changes. Analysis of the natural history of IC demonstrates that the risk of cardiovascular morbidity and mortality far exceeds that of severe limb ischemia or limb loss. In fact, only 2% to 4% of all patients with IC will require a major amputation in their lifetime. However, life expectancy is approximately 10 years less than that of an age-matched cohort. By now, PAD is well recognized as a marker of systemic atherosclerosis. The cornerstone of patient evaluation is a history and physical examination, including a detailed atherosclerotic risk-factor assessment. In the differential diagnosis of IC, clinicians should consider etiologies such as arthritis, spinal stenosis, radiculopathy, venous claudication, or inflammatory processes. In >80% of all patients, it is possible to locate the responsible arterial segment by combining the location and severity of pain with a pulse examination. Noninvasive diagnostic studies help determine the level of disease, may unmask a hemodynamically significant stenosis, and are useful in follow-up. Arteriography is reserved for patients in whom the decision for revascularization has been made. Knowing the anatomic detail of a lesion allows the clinician to determine whether and what type of intervention is feasible. Standard therapy for all patients should be directed at both peripheral and systemic atherosclerosis, beginning with risk-factor modification in the form of smoking cessation, optimal diabetes control, and lipid normalization. The benefits of supervised exercise rehabilitation include significantly increased walking distance and enhanced quality of life. Platelet inhibition has been shown to reduce the risk of ischemic stroke, myocardial infarction, and vascular death and should be prescribed for all but those in whom it is medically contraindicated. Symptom-specific pharmacotherapy with a broad range of medications has yielded disappointing results in the past. However, recent studies have demonstrated that patients receiving the novel agent cilostazol experienced increases in walking distance and improvements in quality of life.
More Related Videos
 07:48
Assessing Therapeutic Angiogenesis in a Murine Model of Hindlimb Ischemia
Published on: June 8, 2019
 13:48
Reduction of Radiation Exposure during Endovascular Treatment of Peripheral Arterial Disease Combining Fiber Optic RealShape Technology and Intravascular Ultrasound
Published on: April 21, 2023
Related Concept Videos
 01:26
Atherosclerosis III: Management
 01:21
Peripheral Arterial Disease II: Clinical Manifestations and Diagnostic Evaluation
 01:27
Peripheral Artery Disease III: Interprofessional Care
 01:26
Peripheral Artery Disease IV: Nursing Management
 01:23
Peripheral Artery Disease V: Postoperative Nursing Management
 01:26
Varicose Veins II: Diagnostic Studies and Interprofessional Care