Related Experiment Video
Updated: Aug 12, 2026


Measuring the 50% Haemolytic Complement (CH50) Activity of Serum
Published on: March 29, 2010
Hemolytic-uremic syndrome and complement factor H deficiency: clinical aspects
1Department of Nephrology, The Birmingham Children's Hospital, United Kingdom. cm.taylor@bhamchildrens.wmids.nhs.uk

A subgroup of patients with hemolytic-uremic syndrome (HUS) has emerged with complement factor H deficiency. These have come to light because of persistent hypocomplementemia, although the molecular finding by Warwicker et al in one pedigree suggests that not all cases exhibit systemic hypocomplementemia. These patients have an atypical presentation in that they do not consistently have a prodrome of enterocolitis although precipitating factors may include infections of various kinds. Patients usually have severe hypertension early in the course of their illness, tend to relapse, and have a poor prognosis. The age of onset varies from neonates to adults. Plasma exchange and replacement with a plasma product containing factor H seem a reasonable option in the absence of better evidence. Kidney transplantation can meet with recurrence of HUS, but the risk of grafting has yet to be established, and a strategy to overcome graft recurrence is needed. Because of the great rarity of this disorder, a strong case can be made for international registries of atypical HUS cases so that clinical and laboratory investigation is promoted.
A subgroup of patients with hemolytic-uremic syndrome (HUS) has emerged with complement factor H deficiency. These have come to light because of persistent hypocomplementemia, although the molecular finding by Warwicker et al in one pedigree suggests that not all cases exhibit systemic hypocomplementemia. These patients have an atypical presentation in that they do not consistently have a prodrome of enterocolitis although precipitating factors may include infections of various kinds. Patients usually have severe hypertension early in the course of their illness, tend to relapse, and have a poor prognosis. The age of onset varies from neonates to adults. Plasma exchange and replacement with a plasma product containing factor H seem a reasonable option in the absence of better evidence. Kidney transplantation can meet with recurrence of HUS, but the risk of grafting has yet to be established, and a strategy to overcome graft recurrence is needed. Because of the great rarity of this disorder, a strong case can be made for international registries of atypical HUS cases so that clinical and laboratory investigation is promoted.

Related Concept Videos
 01:36
Humoral Immune Responses
 01:27
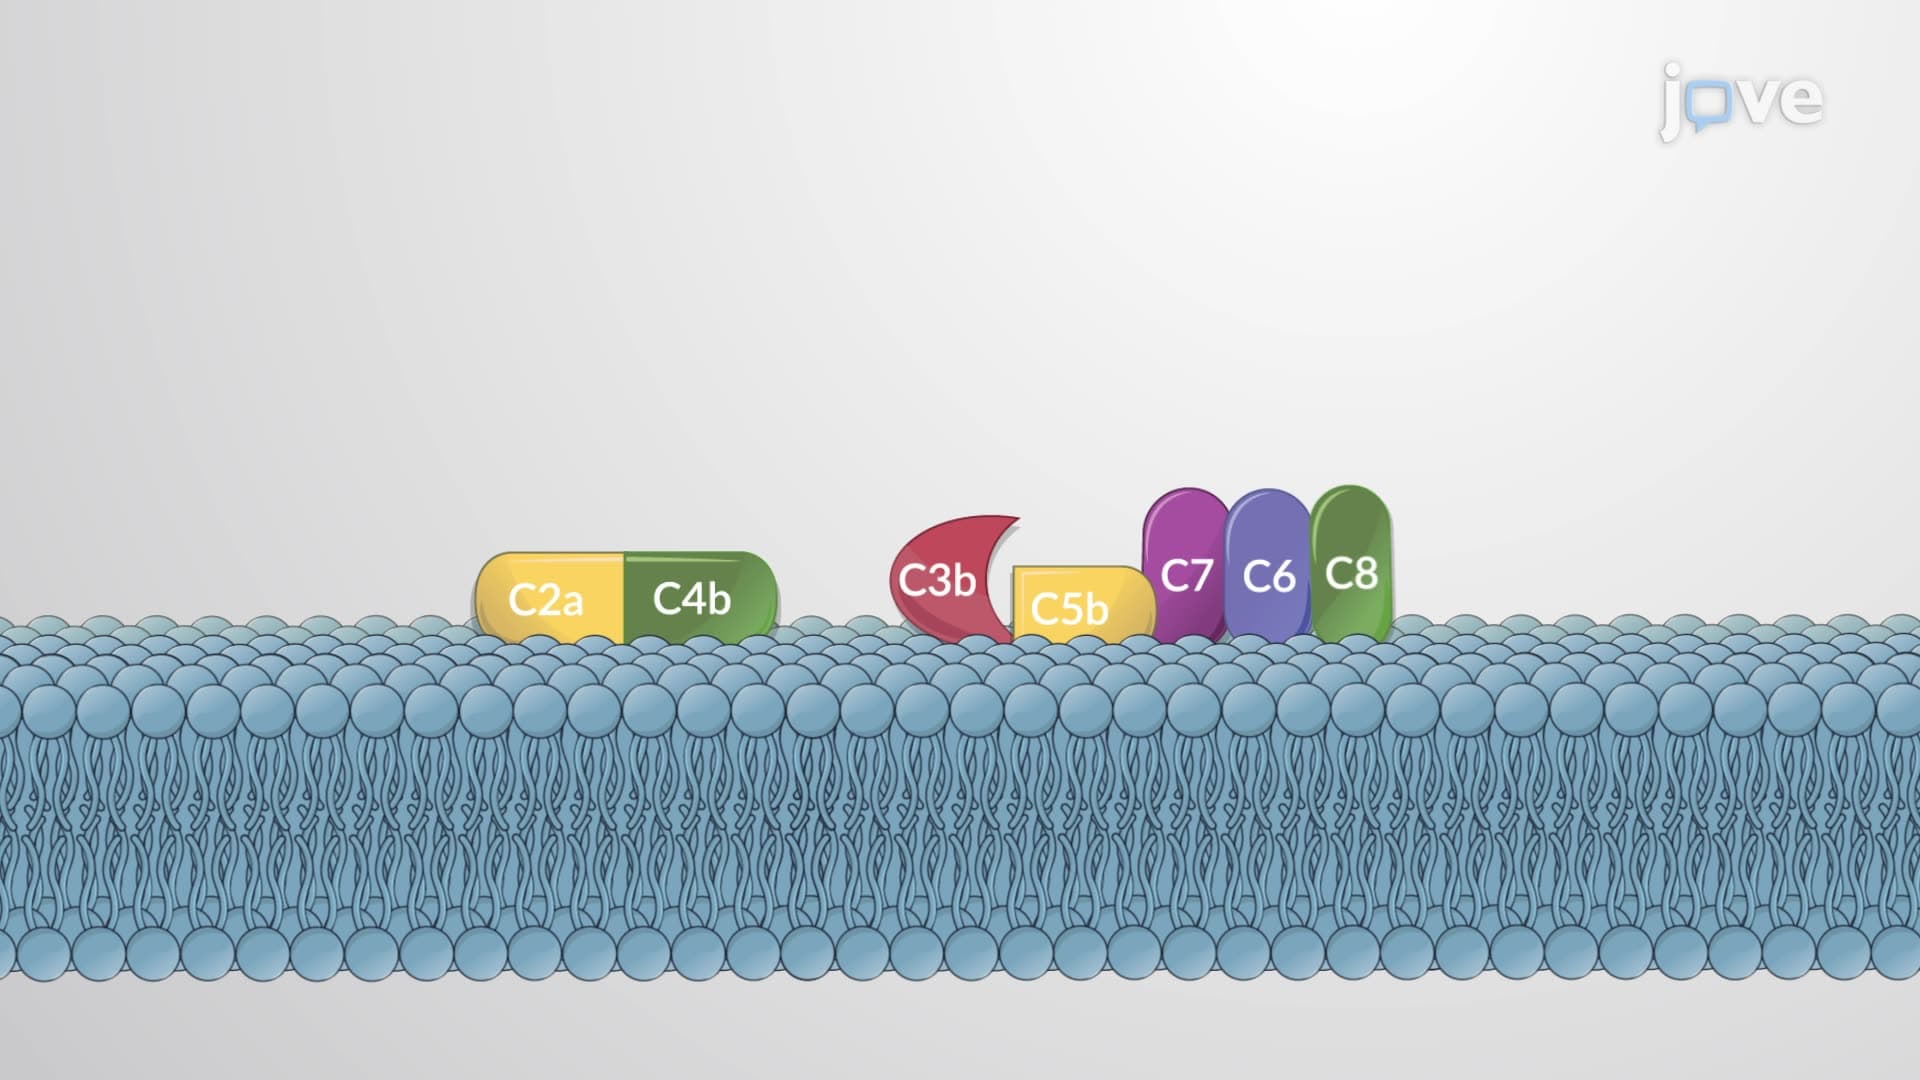
Complement System
 01:01
Hypersensitivity Reactions: Cytolytic Reactions
 01:24
Nephrotic Syndrome I : Introduction
 01:24
Chronic Kidney Disease II: Clinical Manifestations
 01:19
Hypersensitivity Reactions: Immune-Complex Reactions