Related Experiment Video
Updated: Jul 17, 2026


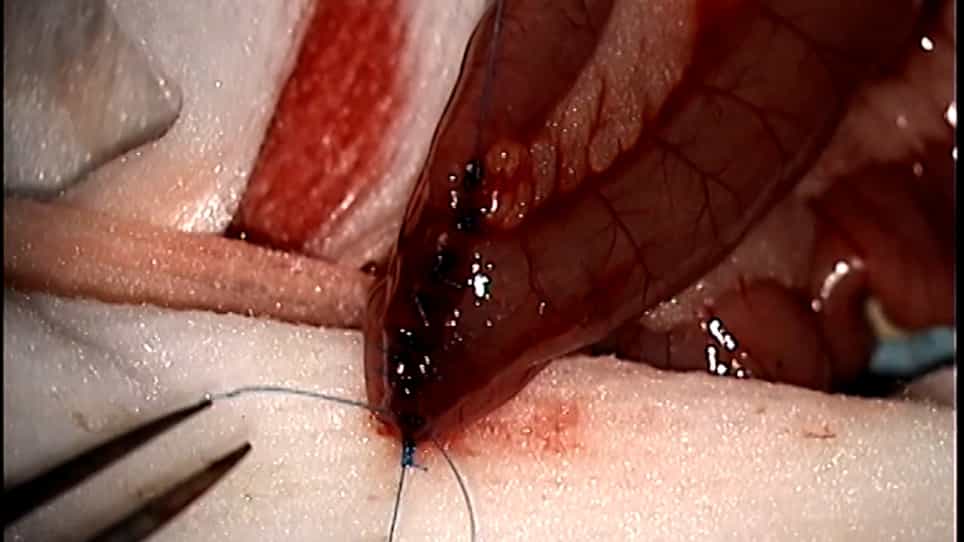
Roux-en-Y Gastric Bypass Operation in Rats
Published on: June 11, 2012
Risks and benefits of gastric bypass in morbidly obese patients with severe venous stasis disease
H J Sugerman1, E L Sugerman, L Wolfe
1General/Trauma Surgery Division, Medical College of Virginia, Virginia Commonwealth University, Richmond, USA. hsugerma@hsc.vcu.edu

Objective:
To determine the risks and benefits of gastric bypass-induced weight loss on severe venous stasis disease in morbid obesity.
Summary Background Data:
Severe obesity is associated with a risk of lower extremity venous stasis disease, pretibial ulceration, cellulitis, and bronze edema.
Methods:
The GBP database was queried for venous stasis disease including pretibial venous stasis ulcers, bronze edema, and cellulitis.
Results:
Of 1,976 patients undergoing GBP, 64 (45% female) met the criteria. Mean age was 44 +/- 10 years. Thirty-seven patients had pretibial venous stasis ulcers, 4 had bronze edema, 23 had both, and 17 had recurrent cellulitis. All had 2 to 4+ pitting pretibial edema. Mean preoperative body mass index (BMI) was 61 +/- 12 kg/m(2) and weight was 179 +/- 39 kg (270 +/- 51% ideal body weight), significantly greater than in patients who underwent GBP without venous stasis disease. Two patients had a pulmonary embolus and four had Greenfield filters in the remote past. Additional comorbidities included obesity hypoventilation syndrome, sleep apnea syndrome, hypertension, gastroesophageal reflux, degenerative joint disease symptoms, type 2 diabetes mellitus, pseudotumor cerebri, and urinary incontinence. Comorbidities were significantly more frequent in the patients with venous stasis disease than for those without. At 3.9 +/- 4 years after surgery, patients lost 55 +/- 21 % of excess weight, 62 +/- 33 kg, reaching 40 +/- 9 kg/m(2) BMI or 176 +/- 41% ideal body weight. Venous stasis ulcers resolved in all but three patients. Complications included anastomotic leaks with peritonitis and death, fatal pulmonary embolism, fatal respiratory arrest, wound infections or seromas, staple line disruptions, marginal ulcerations treated with acid suppression, stomal stenoses treated with endoscopic dilatation, late small bowel obstructions, and incisional hernias. There were six other late deaths.
Conclusions:
Severe venous stasis disease was associated with a significantly greater weight, BMI, male sex, age, comorbidity, and surgical risk (pulmonary embolus, leak, death, incisional hernia) than in other patients who underwent GBP. Surgically induced weight loss corrected the venous stasis disease in almost all patients as well as their other obesity-related problems.

Related Concept Videos
 01:24
Esophageal Varices-I: Introduction
 01:28
Esophageal Varices-II: Clinical Features and Management
In the initial assessment, a thorough review of the patient's medical history is vital to identify risk factors such as liver disease, alcohol abuse, or...
 01:25
Peptic Ulcer Disease V: Surgical Management and Nursing Care
Surgical Interventions for Peptic Ulcer Disease
 01:23
Peripheral Artery Disease V: Postoperative Nursing Management
 01:26
Varicose Veins II: Diagnostic Studies and Interprofessional Care