Related Experiment Video
Updated: Oct 5, 2026

Mouse- and Human-derived Primary Gastric Epithelial Monolayer Culture for the Study of Regeneration
Published on: May 7, 2018
[Atypical regenerative changes, dysplasia, and carcinoma in situ in chronic gastritis associated with Helicobacter
F Martínez-Madrigal1, C Ortiz-Hidalgo, C Torres-Vega
1Centro de Investigación Biomédica del Estado de Michoacán y Departamento de Anatomía Patológica, Hospital Regional de Zona No. 1, IMSS, Av. Hérves de Nocupétaro S/N Morelia, Mich., C.P. 58000.

Abstract:
In the present work we study the association between chronic active gastritis (CAG), atypical regeneration and dysplasia and gastric Helicobacter pylori (HP) infection. We study two groups of endoscopic biopsies. Regenerative changes and dysplasia were evaluated according to Gandur-Maymneh et al. classification which was simplified in typical and atypical regeneration, and mild and severe dysplasia. The group I included 94 patients with CAG, 9 with chronic non active gastritis (CNAG) and 2 with normal gastric mucosa. CAG was graded according to activity in; severe 28 patients; moderate 54 patients and; mild 12 patients. HP association in these cases was 100%, 77% and 25%. In cases of CNAG HP was present in 22%, there were not HP in normal gastric mucosa. There were atypical regeneration in 25% of moderate CAG and in 42% of severe CAG. Mild dysplasia was present in 7.5 and 25% in cases of moderate and severe CAG. Two biopsies showed severe dysplasia. In addition, intestinal metaplasia was found in 15% of CAG, the metaplasia was present in 25% of cases with CAG and atypical regeneration; in 54% of cases with mild dysplasia and; in 100% on cases with severe dysplasia. The group II included 9 cases of gastric cancer of intestinal type, 7 cases of diffuse type, and 4 cases of mixed type. In all these cases there was viewed CAG associated to HP infection in non-neoplastic mucosa. In 75% of cases there were showed atypical regeneration and 60% presented some type of dysplasia. There was transition between atypical regeneration and dysplasia in 6 cases of intestinal gastric cancer and in 3 cases of mixed type. We found relationship between the intensity of CAG and HP colonization, and the association with atypical regeneration and dysplasia.

Related Concept Videos
 01:26
Gastritis II: Pathophysiology
 01:24
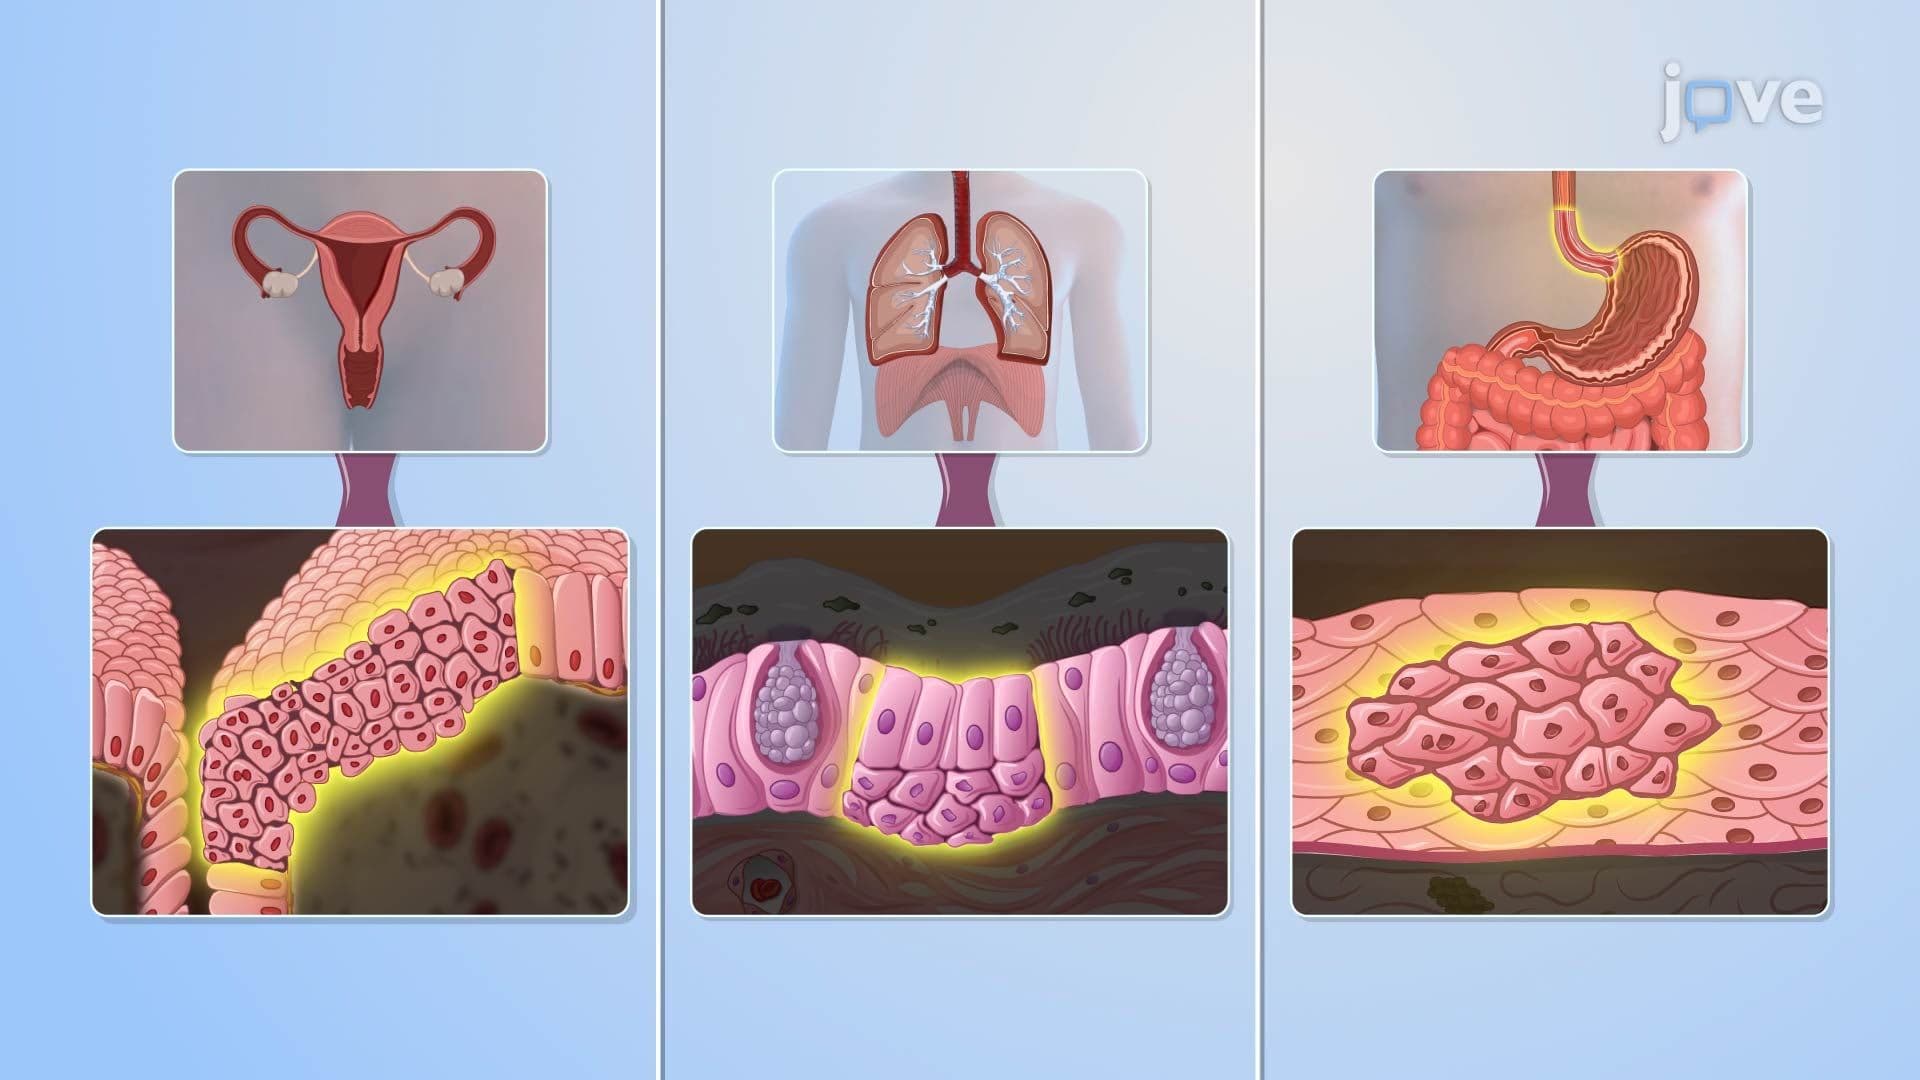
Cellular Adaptation IV: Dysplasia and Metaplasia
 01:17
Gastritis-II: Pathophysiology
In acute gastritis, the gastric mucosa becomes swollen and red and undergoes superficial erosion. Superficial ulceration may lead to bleeding.
In chronic gastritis, persistent or repeated insults lead to chronic inflammatory changes and, eventually, thinning or atrophy of the gastric tissue.
Gastritis can stem from various causes, each...
 01:30
Peptic Ulcer Disease I: Introduction
An acute ulcer, marked by superficial erosion and minimal inflammation, swiftly resolves upon identifying and addressing the underlying cause. In contrast, a chronic ulcer persists, potentially eroding through the muscular wall and forming fibrous tissue.
Peptic ulcers can also be...
 01:25
Peptic Ulcer Disease I: Introduction
 01:21
Barrett Esophagus-I: Introduction
This constant acid exposure transforms the esophagus's pink mucosal lining (stratified squamous epithelium) into a type of lining more similar...