Related Experiment Video
Updated: Oct 5, 2026


Preparing a Mice Model of Severe Acute Pancreatitis via a Combination of Caerulein and Lipopolysaccharide Intraperitoneal Injection
Published on: May 10, 2024
Hemoconcentration: an early marker of severe and/or necrotizing pancreatitis? A critical appraisal
P G Lankisch1, R Mahlke, T Blum
1Department of Internal Medicine, Municipal Clinic of Lüneburg, Germany.

Objective:
A study was designed to reevaluate hemoconcentration as an early marker of severe and/or necrotizing pancreatitis and compare it against contrast-enhanced CT, the gold standard to diagnose acute necrotizing pancreatitis.
Methods:
This prospective study covers the years 1988-1999 for 316 patients (202 male, 114 female) with a first attack of acute pancreatitis. The role of the hematocrit as an early marker of severe and/or necrotizing pancreatitis has been retrospectively evaluated against the prospectively obtained data. They all underwent a CT within 72 h after admission. In addition to the CT-controlled diagnosis of interstitial/necrotizing pancreatitis, the following variables were used to assess severity: initial organ failure according to the Atlanta classification; indication for artificial ventilation and/or dialysis; Ranson score adjusted for etiology; Imrie score; Balthazar score; length of stay in intensive care unit (ICU); total hospital stay; development of pancreatic pseudocysts; indication for operation (necrosectomy); and mortality. Hemoconcentration on admission was defined as a hematocrit level >43.0% for male and >39.6% for female patients. Logistic regression was used to assess the correlation between hemoconcentration and the severity of variables.
Results:
Hematocrit, as a single parameter measured on admission, had the same sensitivity and negative predictive value as the more complicated Ranson and Imrie scores obtained only after 48 h. However, its specificity, positive predictive value, and total accuracy were lower. Hemoconcentration significantly correlated with the Balthazar score (differential diagnosis between interstitial and necrotizing pancreatitis), stay in ICU, and total hospital stay. Sensitivity and specificity of the hematocrit cut-off level of 43.0% for male and 39.6% for female patients to detect necrotizing pancreatitis were 74% and 45%, respectively. The positive predictive value was 24% and the negative predictive value 88%. Receiver operation characteristics (ROC) curve values for several cut-offs did not result in more ideal levels.
Conclusion:
Hemoconcentration does not significantly correlate with important clinical outcome variables of acute pancreatitis including organ failure and mortality rate. Its prognostic value is comparable to the more complicated Ranson and Imrie scores obtained only after 48 h. The major value of this single easily obtainable and cheap parameter on admission lies in its high negative predictive value. In the absence of hemoconcentration, contrast-enhanced CT may be unnecessary on admission unless the patient does not improve.

Related Concept Videos
 01:30
Acute Pancreatitis II: Clinical Manifestations and Management
 01:25
Acute Pancreatitis I: Introduction
 01:27
Acute Pancreatitis I: Introduction
Acute pancreatitis is characterized by rapid inflammation of the pancreas, often caused by factors like gallstone blockage or excessive alcohol consumption. Chronic pancreatitis, on the other hand, is a slow, progressive inflammation that may result from long-term alcohol abuse, obstructions in the pancreatic duct, or genetic factors.
The causes of acute pancreatitis include:
 01:21
Acute Pancreatitis II: Pathophysiology
 01:24
Chronic Pancreatitis I: Introduction
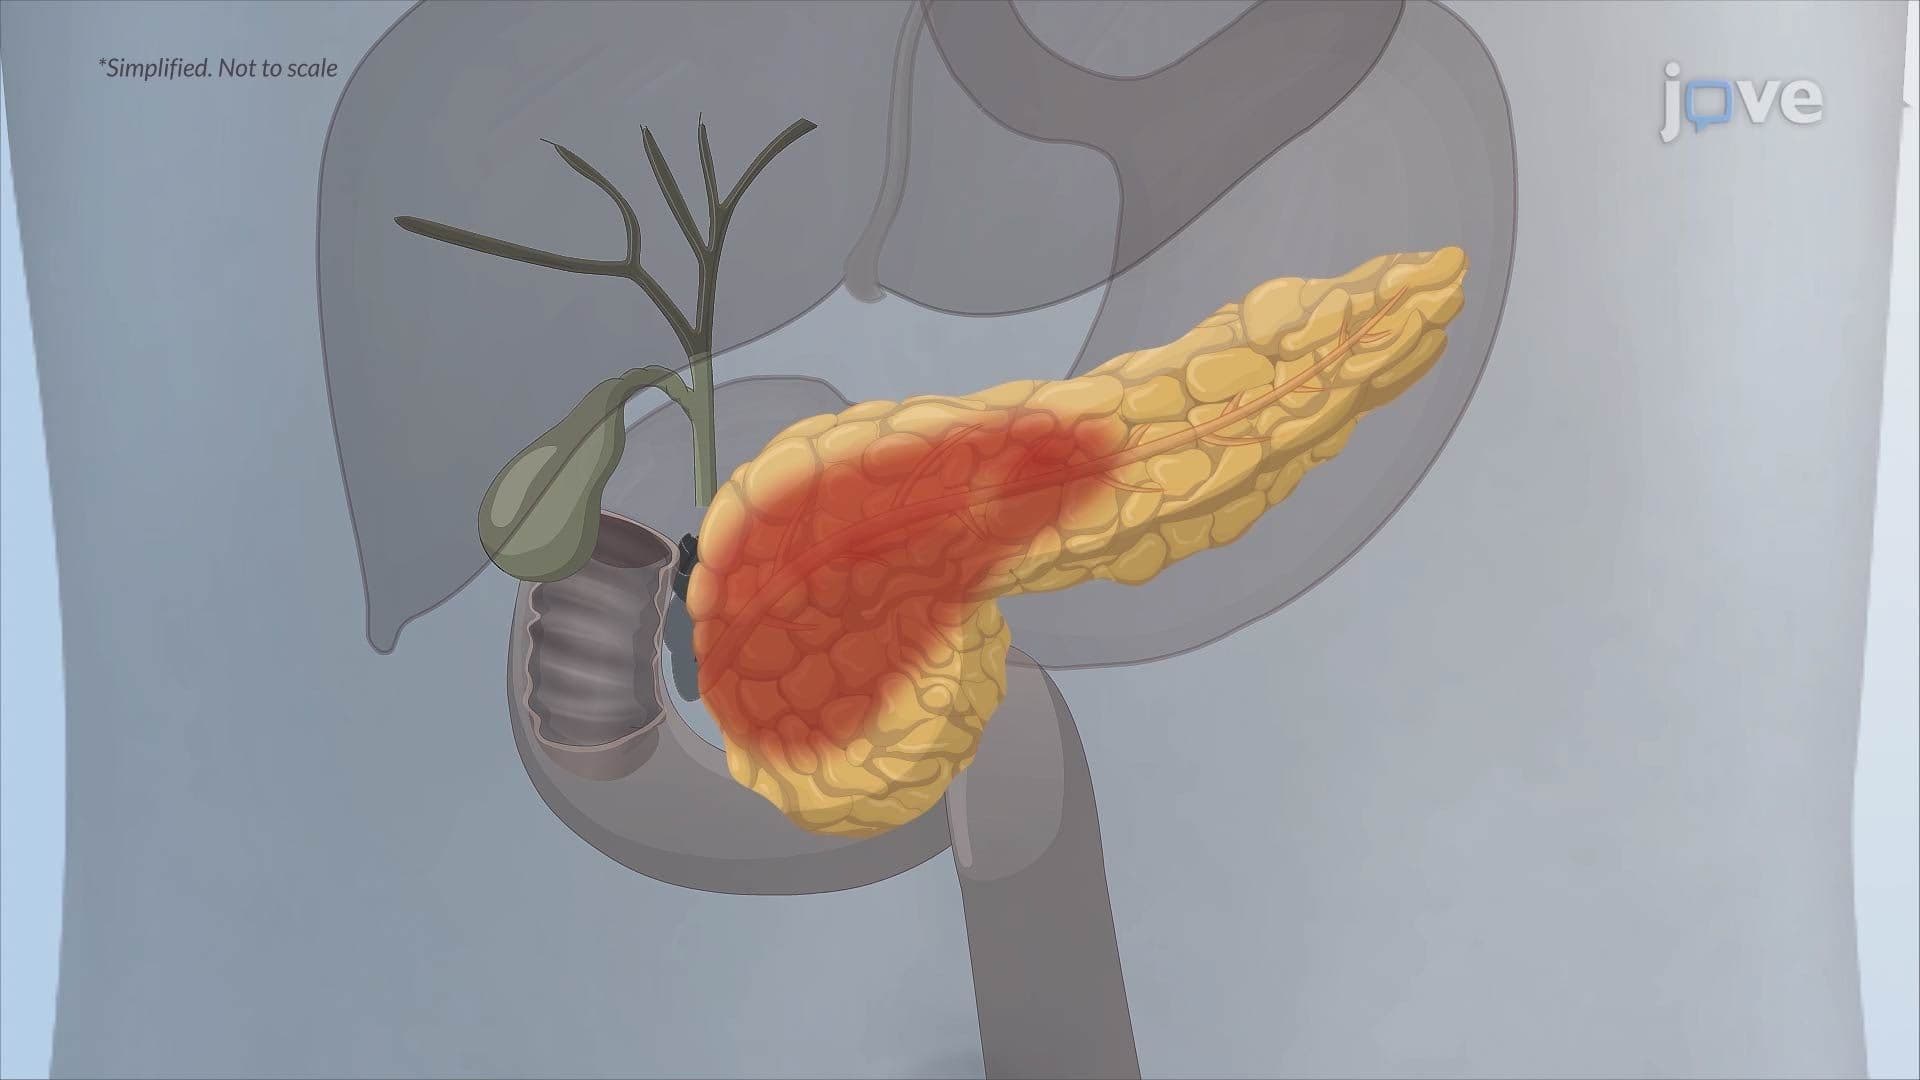
Pancreatitis is the inflammation of the pancreas, which occurs when the immune system becomes active and causes swelling, pain, and disruptions in organ function. Pancreatitis can manifest as either an acute or chronic condition.
Acute pancreatitis arises suddenly and lasts for a brief duration, while chronic pancreatitis is a long-term affliction...
 01:25
Chronic Pancreatitis I: Introduction