Related Experiment Video
Updated: Jul 18, 2026

In vitro Functional Characterization of Mouse Colorectal Afferent Endings
Published on: January 21, 2015
Rectal compliance, capacity, and rectoanal sensation in fecal incontinence
B Salvioli1, A E Bharucha, D Rath-Harvey
1Gastroenterology Research Unit and Division of Colorectal Surgery, Mayo Clinic and Mayo Medical School, Rochester, Minnesota 55905, USA.

Objective:
Assessments of the pathophysiology of fecal incontinence are skewed toward anal sphincter function; however, rectal compliance, rectoanal sensation and capacity may also be relevant. The aim of this study was to evaluate the usual and some novel diagnostic approaches in fecal incontinence.
Methods:
In 22 unselected patients with fecal incontinence (21 F, 33-75 yr), we quantified: 1) symptoms, anorectal manometry, and anal ultrasound; 2) anal perception of temperature and light touch; 3) rectal sensitivity and compliance to distension; and 4) rectal reservoir function. Control values were obtained from two groups of 11 (seven F, 32-53 yr), and 32 (18 F, 19-44 yr) volunteers.
Results:
Patients had urge (14), passive (four), or combined (four) fecal incontinence; symptoms were mild in three, moderate in nine, and severe in 10 patients. Most had low sphincteric pressures and ultrasonic abnormalities. Temperature perception was impaired (p < 0.05) in incontinent patients, to a greater extent in the proximal anal canal and in patients with passive, as opposed to urge, incontinence. Intraluminal pressures for sensations of rectal distension were lower in incontinent patients (p = 0.02). Artificial stools elicited sensations of rectal filling at lower volumes than did a barostat bag, and in patients with urge, as opposed to passive, incontinence. In patients and controls, the sensation of urgency was associated (r2 = 0.2, p < 0.01) with rectal compliance.
Conclusions:
We confirm that temperature sensation is impaired, and perception of rectal distension is not always reduced in fecal incontinence. Artificial stool tended to induce sensations at lower volumes than did balloon inflation. Altered sensory mechanisms may contribute to the pathophysiology of fecal incontinence.
More Related Videos


Related Concept Videos
 01:27
Assessing Body Temperature - Rectal
Follow these steps for rectal temperature assessment:
Step 1: Perform hand hygiene and don clean gloves to prevent cross-infection.
Step 2: Position the patient in a side-lying position to better visualize the rectal...
 01:26
Muscles of the Pelvic Floor and Perineum
Perineal Layer
The perineum is a diamond-shaped area below the pelvic diaphragm, divided into an anterior urogenital triangle that contains the external genitals and a posterior anal triangle housing the anus. The urogenital...
 01:09
Large Intestine
The ileocecal sphincter, a mucous membrane fold, guards the opening from the ileum to the large intestine. This valve permits material from the small intestine to pass into the large intestine. Attached to the ileocecal valve is the cecum. This small pouch, approximately 6 cm long, has a twisted, coiled tube known as...
 01:26
Feces Formation and Defecation
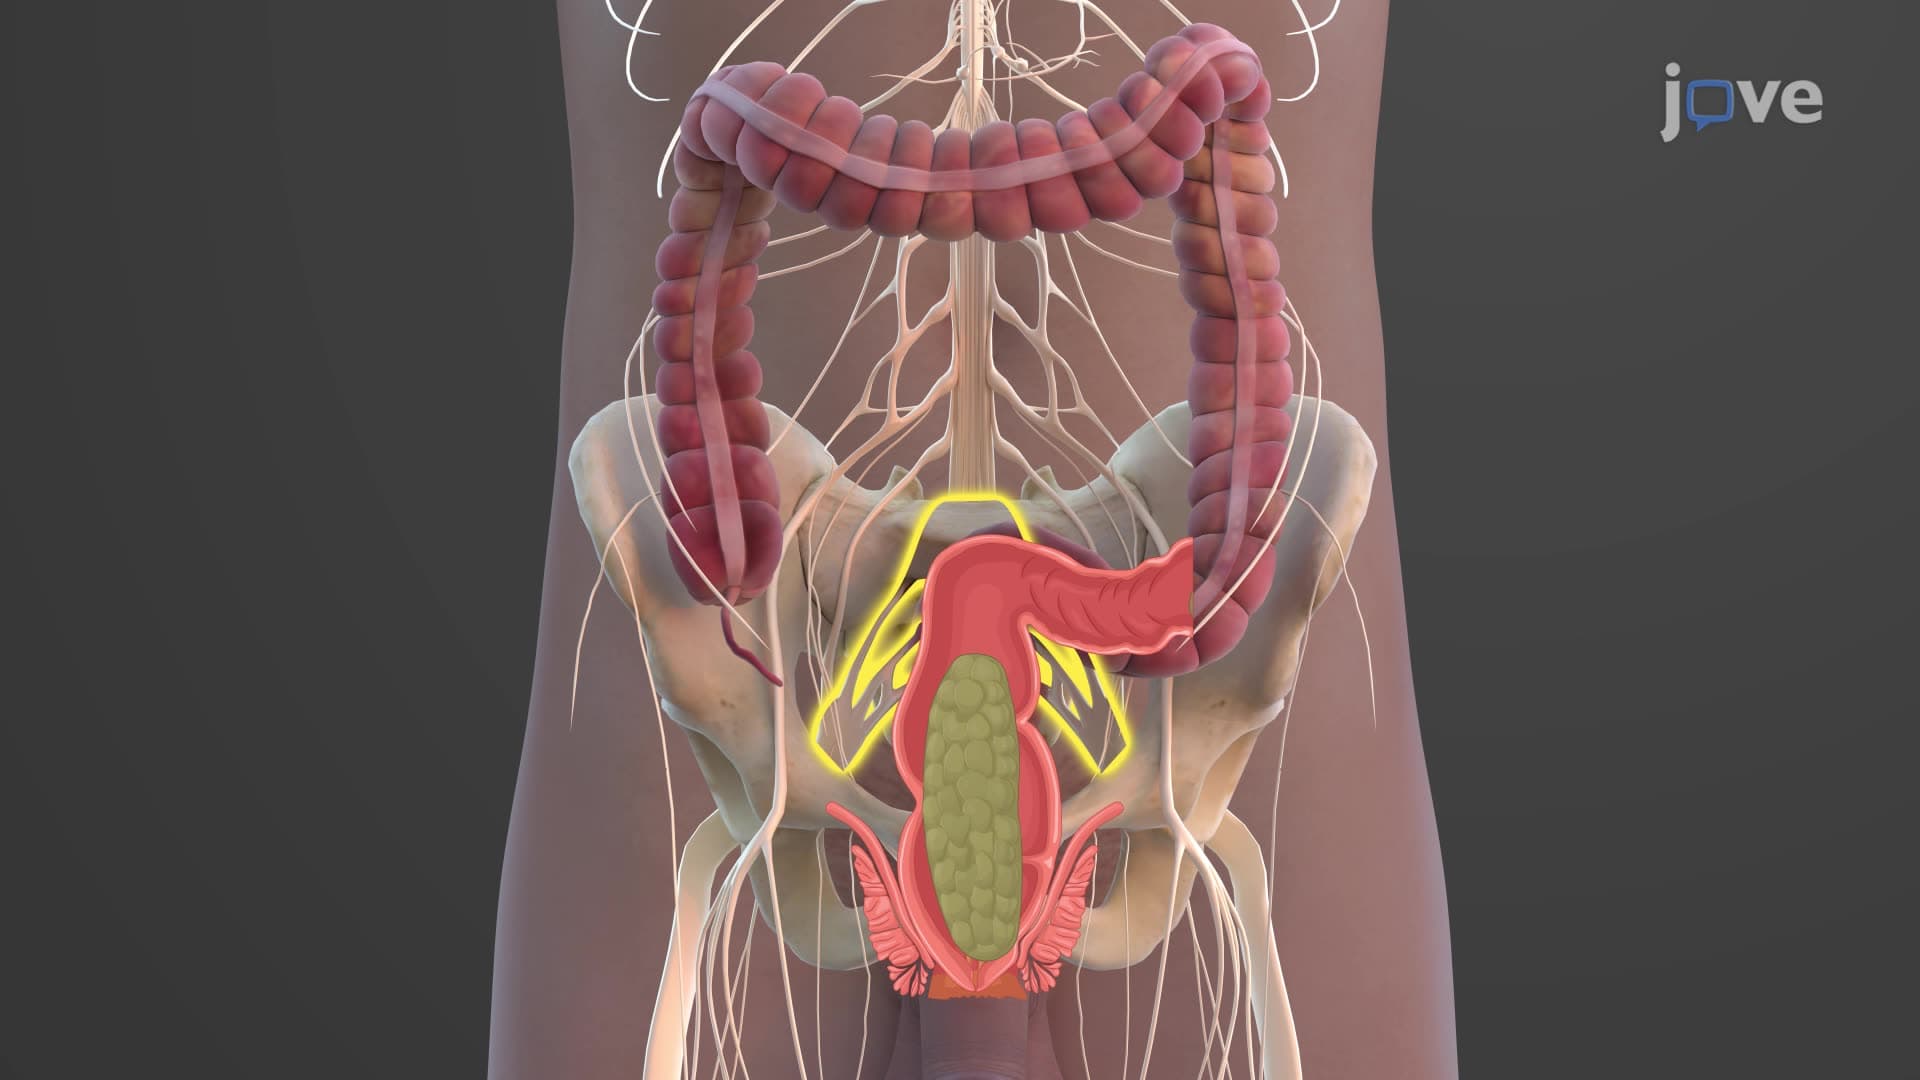
The mass peristalsis then pushes the feces into the rectum, which stretches the rectal walls to activate...
 01:25
Assessment of the Rectum and Anus
Rectal Inspection
Begin by inspecting the perianal and anal areas for color, texture, rashes,...
 01:21
Inflammatory Bowel Disease V: Surgical Management
Here are some common surgical interventions for IBD: