Related Experiment Video
Updated: Sep 30, 2026

Homogeneous Time-resolved Förster Resonance Energy Transfer-based Assay for Detection of Insulin Secretion
Published on: May 10, 2018
Pulmonary insulin administration using the AERx system: physiological and physicochemical factors influencing insulin
S J Farr1, A McElduff, L E Mather
1Aradigm Corporation, Hayward, California 94545, USA. farrs@aradigm.com

Background:
Orally inhaled insulin may provide a convenient and effective therapy for prandial glucose control in patients with diabetes. This study evaluated the influence of formulation pH and concentration and different respiratory maneuvers on pharmacokinetic and pharmacodynamic properties of inhaled insulin.
Methods:
Three, open-label crossover studies in a total of 23 healthy subjects were conducted in which the safety, pharmacokinetics, and pharmacodynamics of insulin inhalation were compared to subcutaneous (SC) injection into the abdomen of commercially available regular insulin. A novel, aerosol generating system (AERx Diabetes Management System, Aradigm Corporation, Hayward, CA) was used to deliver aqueous insulin bolus aerosols to the lower respiratory tract from formulations at pH 3.5 or 7.4 and concentrations of U250 (250 U/mL) or U500 (500 U/mL).
Results:
Time to maximum insulin concentration in serum (Tmax) after SC dosing occurred approximately 50-60 minutes with the time to minimum plasma glucose concentration (i.e., maximum hypoglycemic effect), (TGmin), occurring later, at around 100-120 minutes. In contrast, pulmonary delivery led to a significantly earlier Tmax (7-20 minutes) and TGmin (60-70 minutes), parameters that were shown to be largely unaffected by changing the pH or concentration of the insulin. However, investigation of changes in inhaled volume (achieved by different programming of the AERx system) for administration of the same sized aerosol bolus revealed significant effects. Significantly slower absorption and time to peak hypoglycemic activity occurred when aerosol delivery of insulin occurred during a shallow (approximately 40% vital capacity) as opposed to a deep (approximately 80% vital capacity) inspiration. In addition, it was shown that serum concentration of insulin increased immediately after a series of forced expiraratory maneuvers 30 minutes after inhaled delivery.
Conclusions:
Pulmonary delivery of aqueous bolus aerosols of insulin in healthy subjects resulted in rapid absorption with an associated hypoglycemic effect quicker than is achieved after subcutaneous dosing of regular insulin. Inhaled insulin pharmacokinetics and pharmacodynamics were independent of formulation variables (pH, concentration) but affected by certain respiratory maneuvers.
More Related Videos
 08:04
Human Pseudoislet System for Synchronous Assessment of Fluorescent Biosensor Dynamics and Hormone Secretory Profiles
Published on: November 3, 2023
 06:13
Randomized Controlled Trial to Study the Acute Effects of Strength Exercise on Insulin Sensitivity in Obese Adults
Published on: December 1, 2023
Related Concept Videos
 01:27
Glucose Homeostasis: Pancreatic Islets and Insulin Secretion
Insulin and C-peptide are co-secreted in...
 01:25
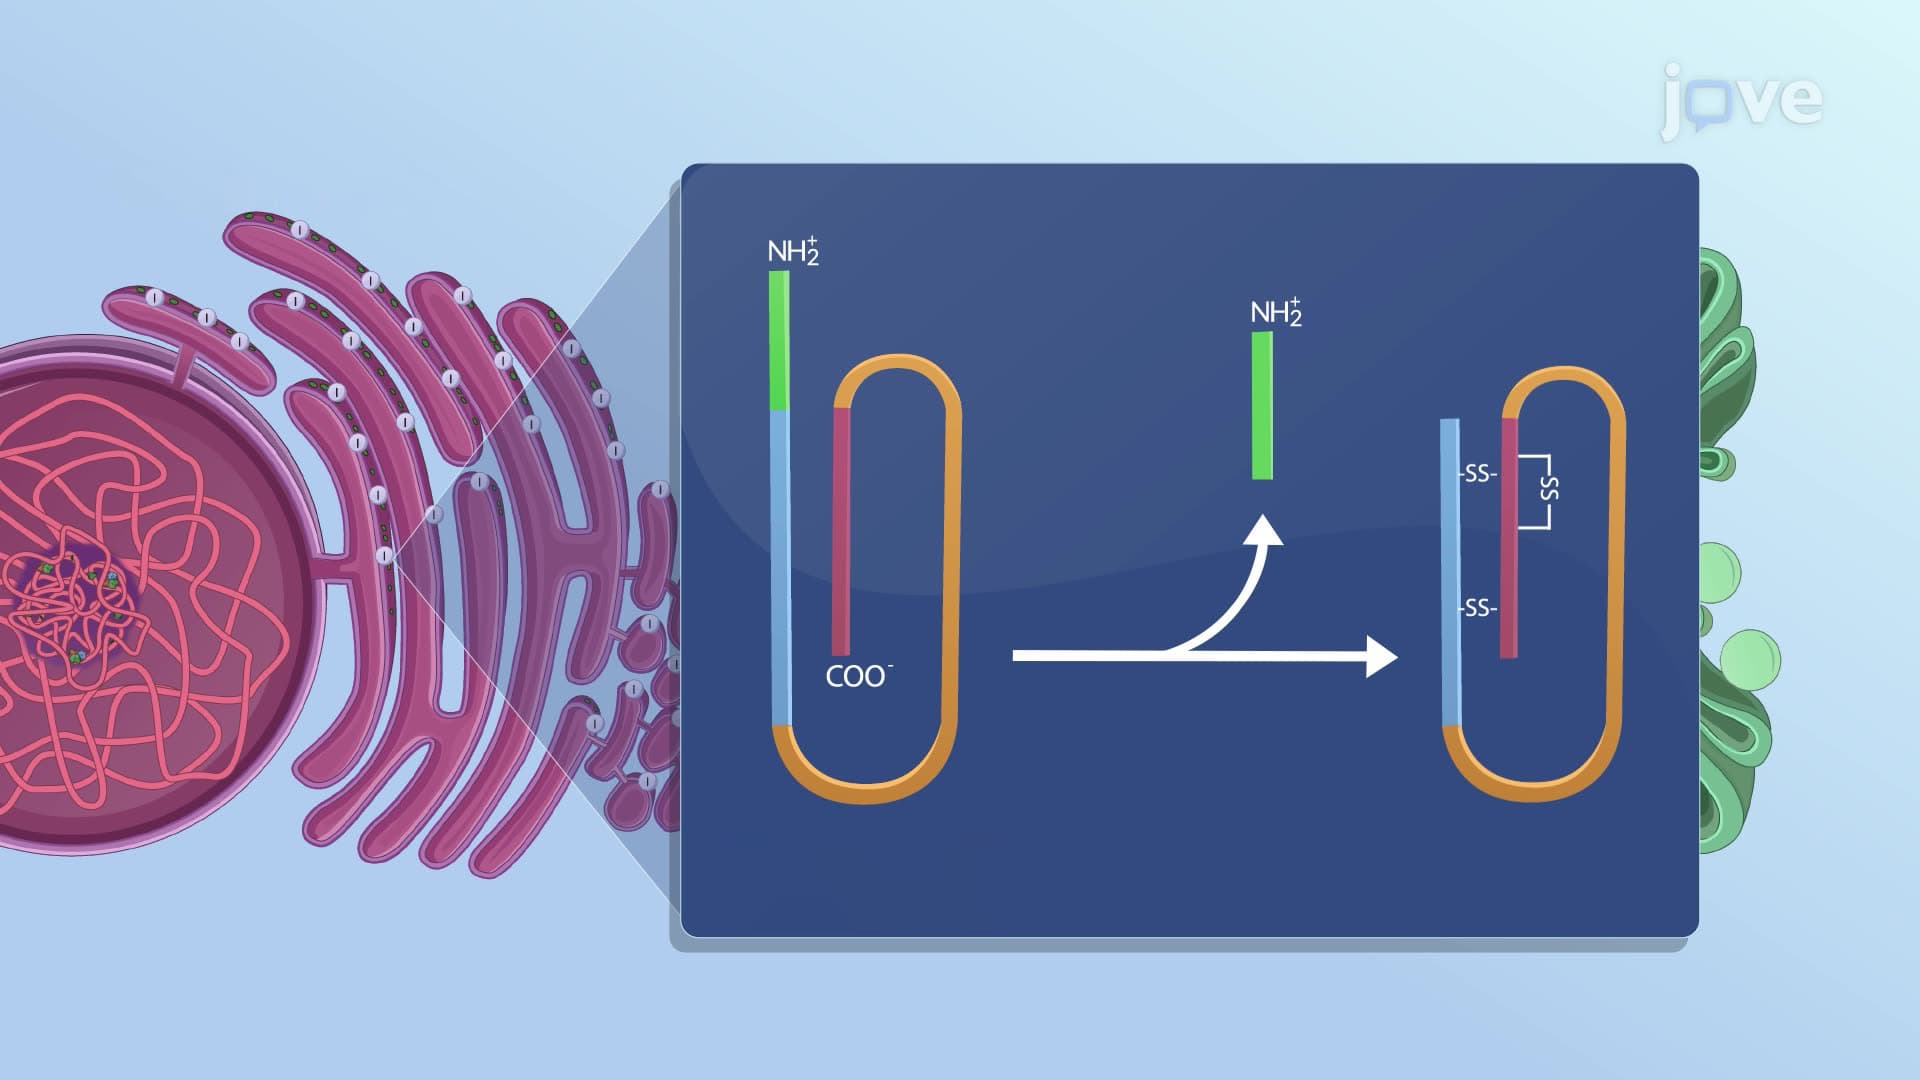
Insulin: Biosynthesis, Chemistry, and Preparation
Damage or functional impairment of β-cells inhibits insulin production, leading to diabetes. Diabetes treatment primarily uses...
 01:27
Insulin Formulations: Types and Delivery
Short-acting insulins are divided into rapid-acting...
 01:16
Insulin: Dosing Regimen and Adverse Effects
The basal dose constitutes about 40%-50% of the total daily dose, with the rest as premeal insulin. The mealtime insulin dose should mirror...
 01:24
Glucagon-like Receptor Agonists
GLP-1, when administered in high doses intravenously, triggers insulin secretion, inhibits glucagon release, slows gastric emptying, reduces food intake, and restores normal insulin secretion. However, its rapid inactivation by the...
 01:23
Dipeptidyl Peptidase 4 Inhibitors