Related Experiment Video
Updated: Jul 28, 2026

Murine Isolated Heart Model of Myocardial Stunning Associated with Cardioplegic Arrest
Published on: August 6, 2015
Adrenergic blockade reduces skeletal muscle glycolysis and Na(+), K(+)-ATPase activity during hemorrhage
F D McCarter1, J H James, F A Luchette
1Division of Trauma and Surgical Critical Care, University of Cincinnati College of Medicine and Shriners Hospitals for Children, Cincinnati, OH 45267, USA.

Background:
Recent evidence suggests that hyperlactatemia in shock may reflect accelerated aerobic glycolysis linked to activity of the Na(+), K(+)-ATPase rather than hypoxia. Epinephrine stimulates glycolysis in resting muscle largely by stimulating Na(+), K(+)-ATPase activity. This study evaluates the effects of hemorrhagic shock, with and without combined alpha- and beta-adrenergic receptor blockade, on lactate production, glycogenolysis, Na(+)-K(+) pump activity, and high-energy phosphates in rat skeletal muscle.
Methods:
Male Sprague-Dawley rats in four treatment groups were studied: unhemorrhaged control not receiving blockers (CN), controls receiving blockers (CB), shocked animals not receiving blockers (SN), and shocked rats receiving blockers (SB). Shocked rats (SN and SB) were bled to a MAP of 40 mm Hg, maintained for 60 min. Blocker groups (CB and SB) received propranolol and phenoxybenzamine. Arterial blood was drawn for plasma lactate, epinephrine, norepinephrine, and gas analysis. Lactate, glycogen, glucose 6-phosphate, ATP, phosphocreatine, and intracellular Na(+) and K(+) were determined in extensor digitorum longus and soleus muscles. For comparison, muscles were exposed to epinephrine and/or ouabain in vitro.
Results:
With the exception of P(a)CO(2), HCO(3), and base excess in the SN group, no significant differences in arterial blood gas parameters were noted. Adrenergic blockade significantly reduced plasma lactate concentration. In shocked rats, adrenergic blockade significantly reduced muscle lactate and glucose 6-phosphate accumulation. Intracellular Na(+):K(+) ratio was decreased in SN rats, implying increased Na(+)-K(+) pump activity. Adrenergic blockade raised the intracellular Na(+):K(+) ratio in shocked animals, implying decreased pump activity. Epinephrine exposure in vitro stimulated muscle lactate production, raised glucose 6-phosphate content, and significantly reduced soleus phosphocreatine stores.
Conclusions:
Neither hypoxia nor defective oxidative metabolism appeared responsible for increased glycolysis during hemorrhagic shock. Adrenergic blockade concurrently reduced plasma lactate, muscle levels of lactate and glucose 6-phosphate, and muscle Na(+)-K(+) pump activity during shock. Rapid skeletal muscle aerobic glycolysis in response to increased plasma epinephrine levels may be an important contributor to increased glycolysis in muscle and increased plasma lactate during hemorrhagic shock.
More Related Videos
 09:04
Skeletal Muscle Neurovascular Coupling, Oxidative Capacity, and Microvascular Function with 'One Stop Shop' Near-infrared Spectroscopy
Published on: February 20, 2018
 10:28
A Semi-High-Throughput Adaptation of the NADH-Coupled ATPase Assay for Screening Small Molecule Inhibitors
Published on: August 17, 2019
Related Concept Videos
 01:28
Drugs Acting on Autonomic Ganglia: Blockers
 01:22
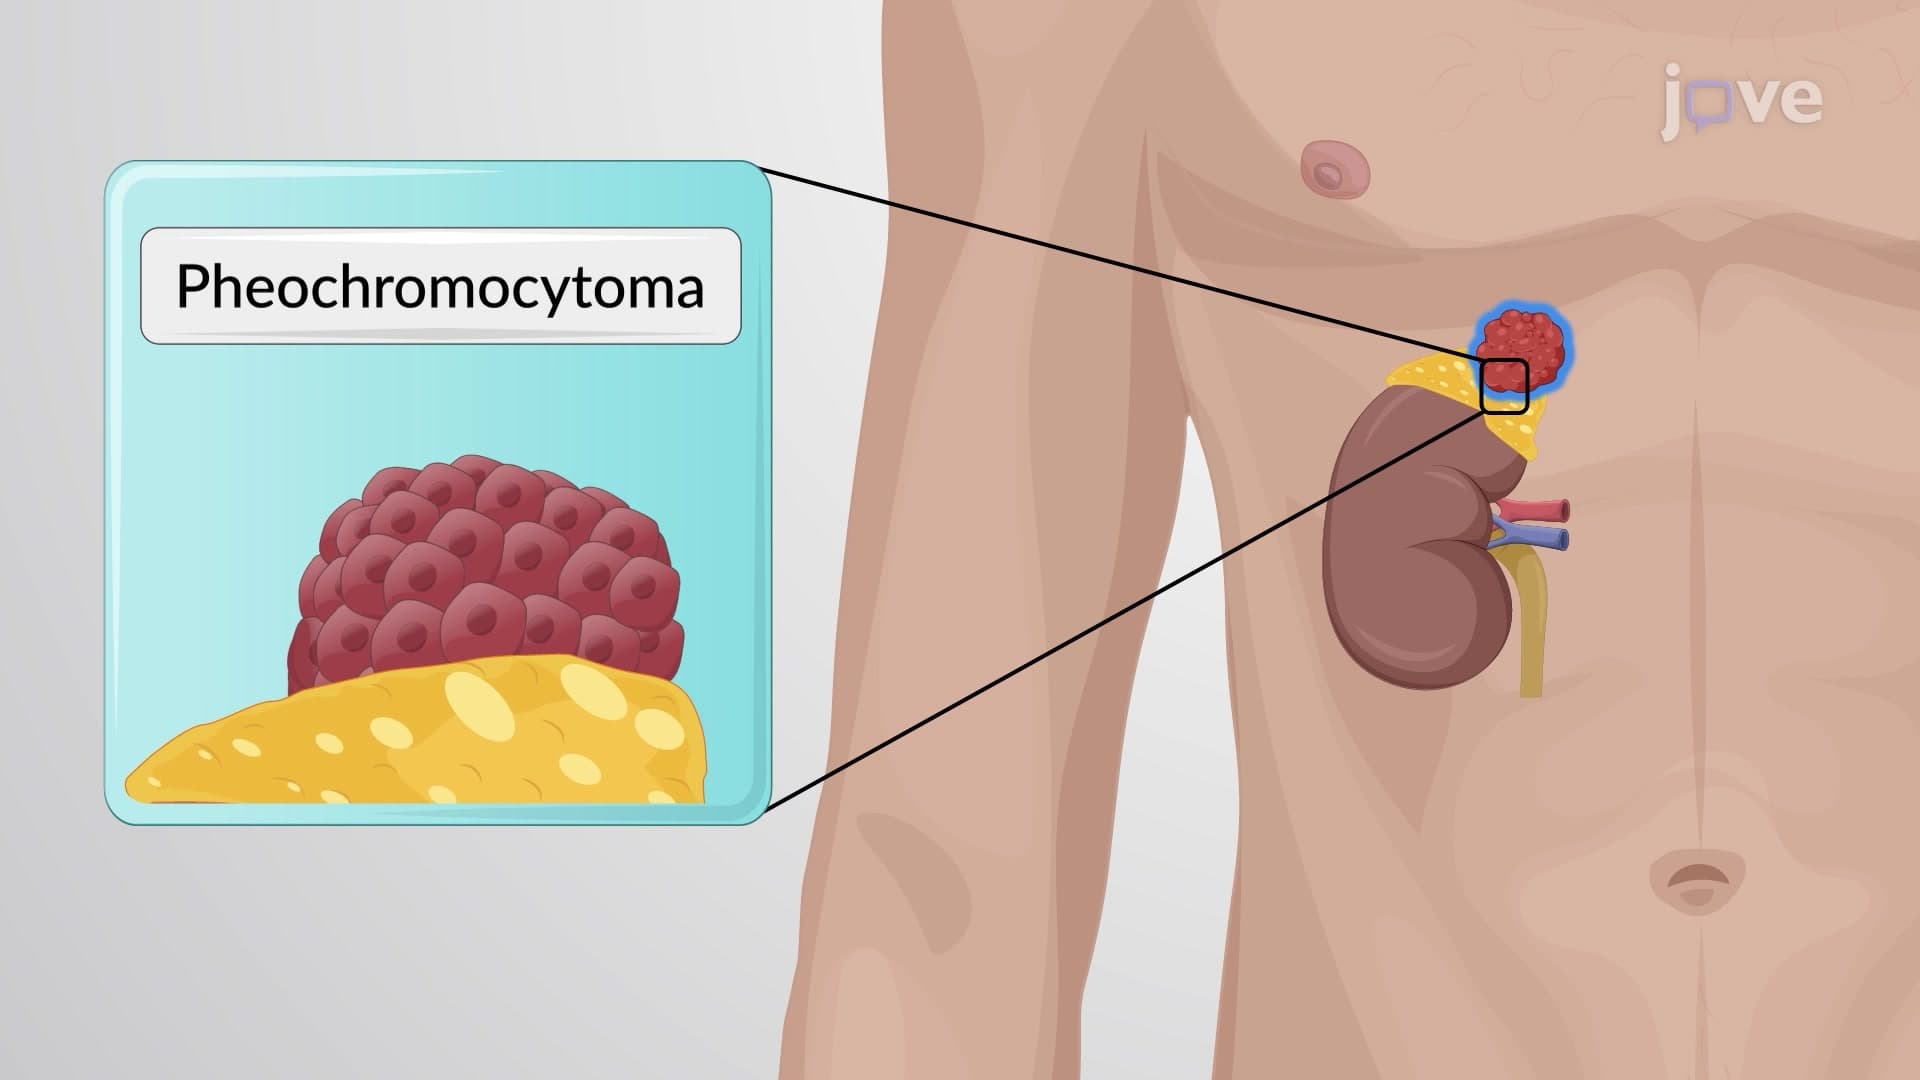
Adrenergic Antagonists: Pharmacological Actions of ɑ-Receptor Blockers
α1-blockers: These drugs inhibit α1-adrenoceptors on smooth muscle cells, resulting in vasodilation. This vasodilation lowers blood pressure, making α1-blockers valuable in treating hypertension. Additionally, α1-blockers effectively address urinary obstruction...
 01:31
Adrenergic Antagonists: ɑ and β-Receptor Blockers
 01:27
Nondepolarizing (Competitive) Neuromuscular Blockers: Pharmacological Actions
Although all competitive neuromuscular blockers are designed...
 01:28
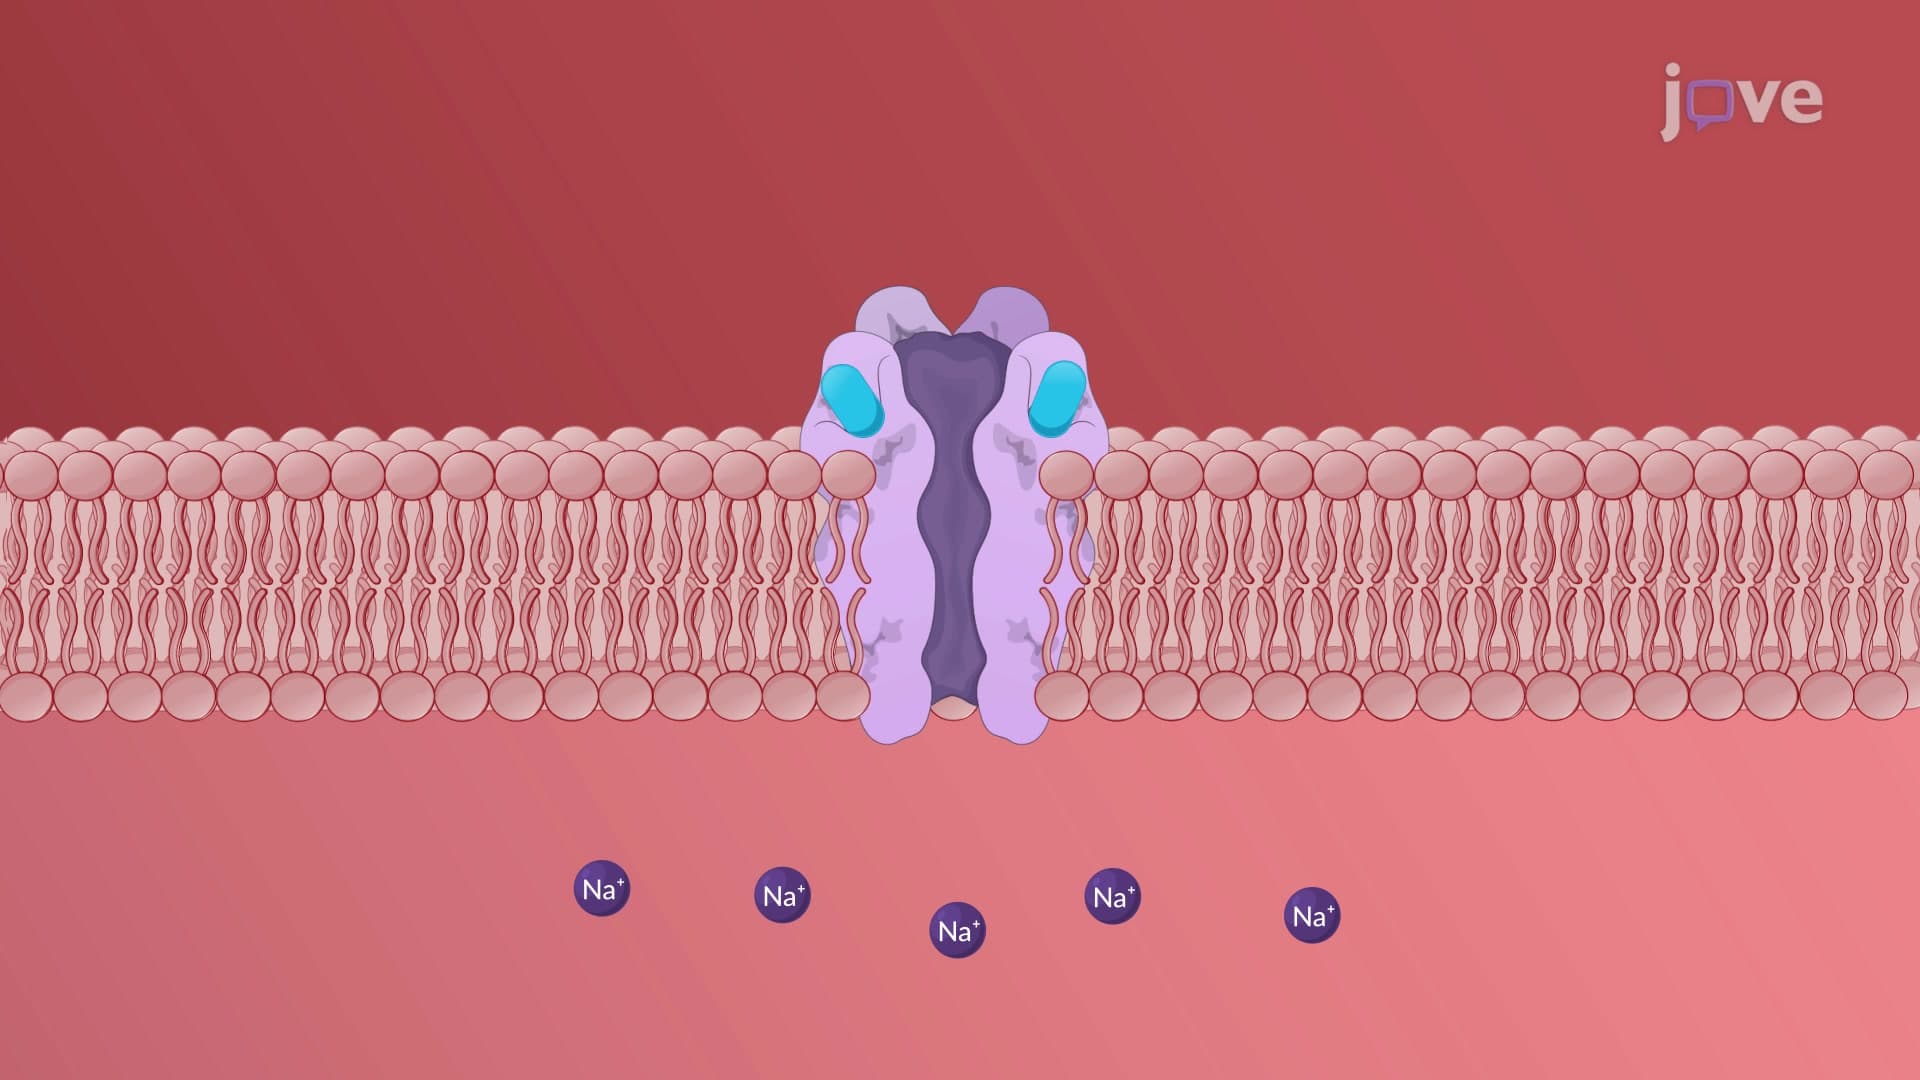
Depolarizing Blockers: Mechanism of Action
Succinylcholine is the most commonly used depolarizing blocker. Chemically, it constitutes two molecules of acetylcholine joined together by an acetate methyl group. They act on the receptors in the same way as acetylcholine. Because succinylcholine...
 01:21
Skeletal Muscle Relaxants: Adverse Effects
Unlike...