Related Experiment Video
Updated: Oct 5, 2026

Closure of a Patent Foramen Ovale (PFO): An Intervention Sequence
Published on: December 23, 2022
Patent foramen ovale and cryptogenic cerebral infarction
1Department of Medicine, Monash University and Monash Medical Centre, Melbourne, Victoria, Australia. David.McGaw@med.monash.edu.au

Insights
Patent foramen ovale (PFO) is linked to cryptogenic stroke. Further research is needed to compare PFO closure devices and medical treatments for optimal patient outcomes.
Area of Science:
- Cardiology
- Neurology
- Vascular Medicine
Background:
- Patent foramen ovale (PFO) is increasingly recognized as a cause of stroke, especially in younger individuals with cryptogenic stroke.
- The primary mechanism involves paradoxical embolism, where venous clots pass through the PFO into the arterial circulation, leading to cerebral embolism.
- Current management for cryptogenic stroke with PFO includes lifelong anticoagulation or antiplatelet therapy, with surgical PFO closure being a less common option.
Purpose of the Study:
- To address the need for comparative data on emerging percutaneous PFO closure devices versus traditional medical therapies.
- To highlight the critical need to differentiate between causative PFOs, innocent PFOs, and cryptogenic strokes with alternative etiologies.
- To emphasize the necessity of determining the risk-benefit profile of various treatment modalities for distinct patient subgroups.
Main Methods:
- Review of current literature and clinical practices regarding PFO and cryptogenic stroke.
- Discussion of the diagnostic challenges in identifying the etiological role of PFO in stroke.
- Analysis of the evolving treatment landscape, including percutaneous closure devices and medical management.
Main Results:
- The study identifies two key unresolved issues: accurate patient stratification and the risk-benefit assessment of treatment options.
- Percutaneous PFO closure devices offer a non-surgical alternative to traditional therapies.
- Clear distinctions between causative, innocent, and incidental PFOs are crucial for guiding treatment decisions.
Conclusions:
- Rational, evidence-based treatment for cryptogenic stroke with PFO requires further comparative studies.
- Patient selection and risk stratification are paramount for optimizing therapeutic strategies.
- The development of PFO closure devices necessitates a re-evaluation of treatment algorithms for cryptogenic stroke.
Abstract:
The patent foramen ovale (PFO) has been increasingly implicated in the aetiology of stroke, particularly in young patients with no other identifiable cause (cryptogenic stroke). The mechanism is by the passage of venous clots through the patent foramen into the arterial circulation, enabling cerebral embolism. Such patients with cryptogenic stroke and PFO are often treated with life-long anticoagulants or antiplatelet agents in an attempt to decrease the risk of a recurrence. Less commonly, surgical closure of the PFO has been undertaken in these patients. However, the recent evolution of closure devices that are delivered percutaneously by standard cardiac catheter techniques now offer an alternative non-surgical option. These alternative therapies are yet to be compared adequately. Two issues remain to be resolved. First, in determining appropriate therapy, patients with cryptogenic stroke may be divided into three groups: those with no PFO but an alternative unrecognized aetiology, those with an 'innocent' PFO and an alternative unrecognized aetiology and those with a causative PFO. The distinction between these groups clearly has important treatment implications. Second, the risk versus benefit of each available treatment modality must be determined for these different patient subgroups. These two issues require resolution before rational evidence-based treatment can be prescribed for patients with PFO and cryptogenic stroke.

Related Concept Videos
 01:15
Ischemic Stroke ll: Pathophysiology
 01:15
Ischemic Stroke l: Introduction
 01:29
Hemorrhagic Stroke ll: Pathophysiology
 01:22
Cerebral Edema ll: Pathophysiology
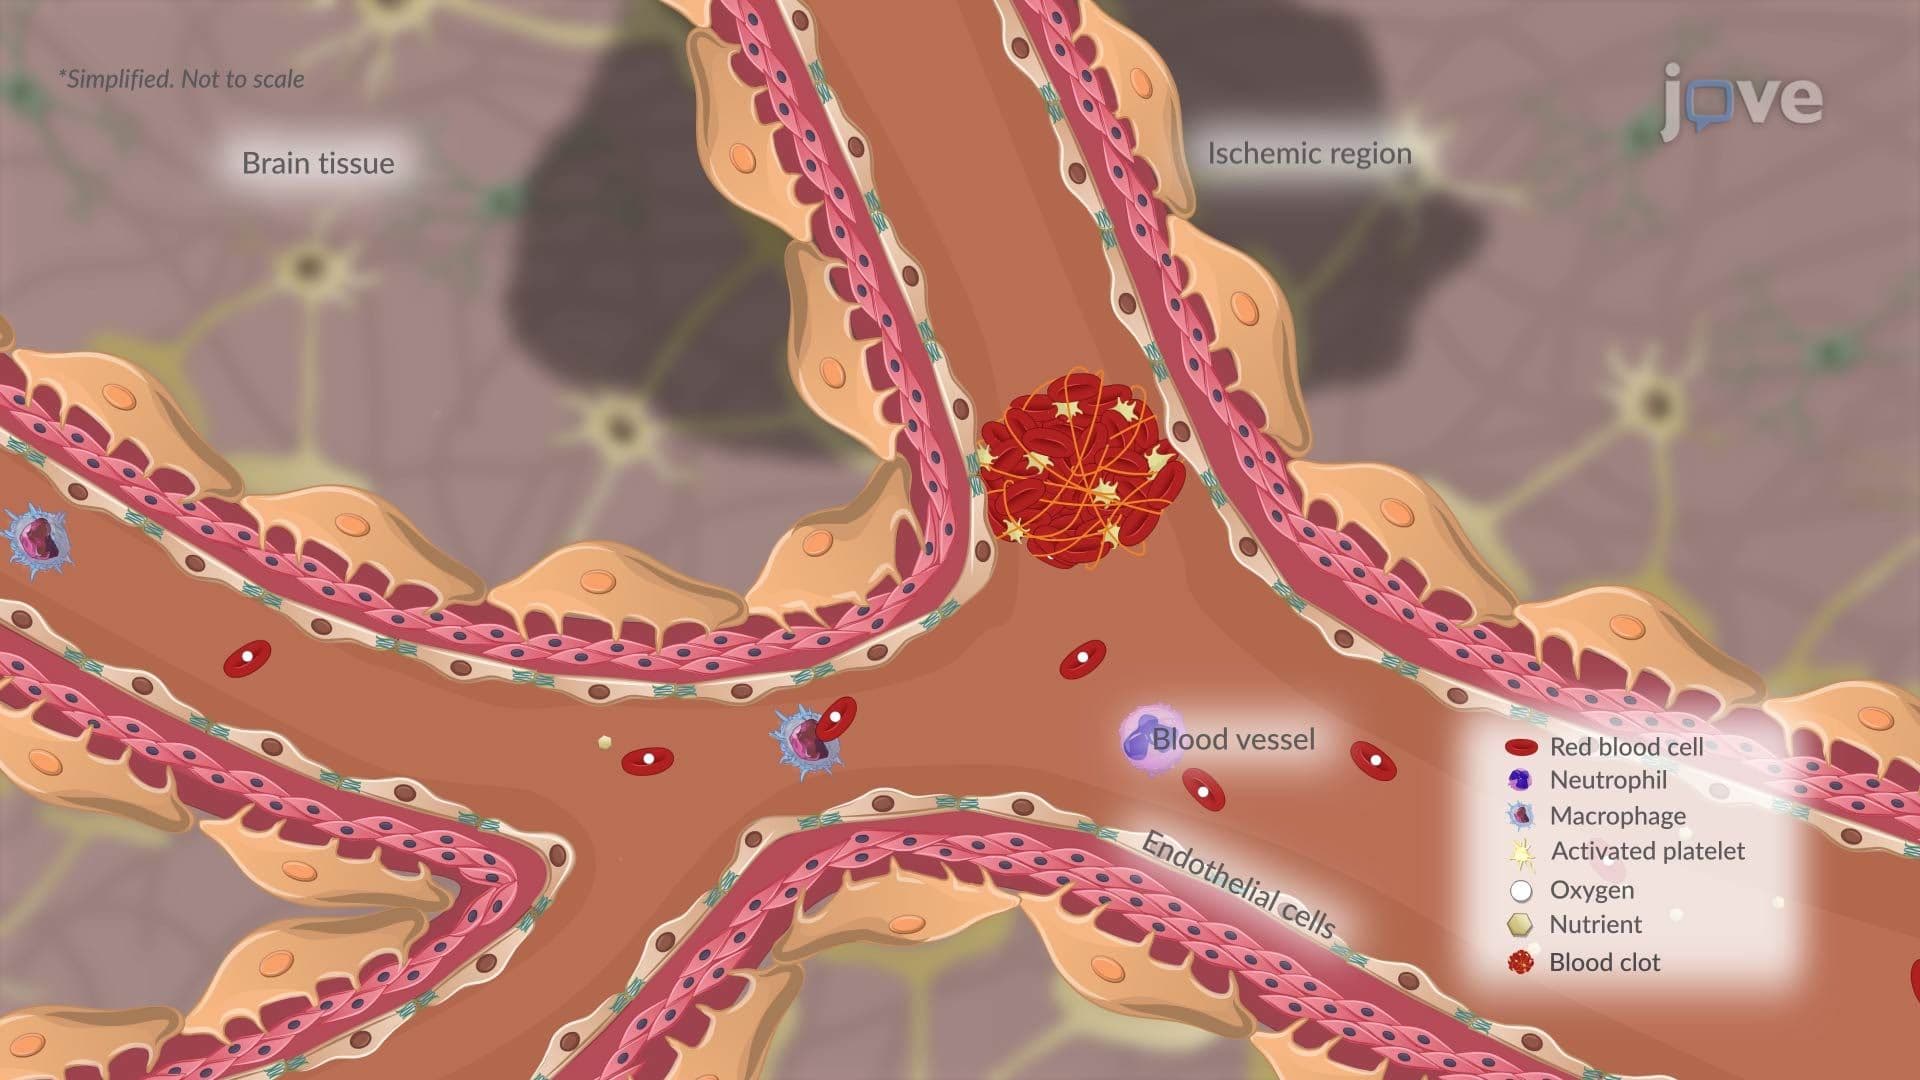 01:26
Transient Ischemic Attack l: Introduction
 01:10
The Arch of Aorta
Encircling the heart, the coronary arteries form a ring-like structure before...