Related Experiment Video
Updated: Oct 5, 2026
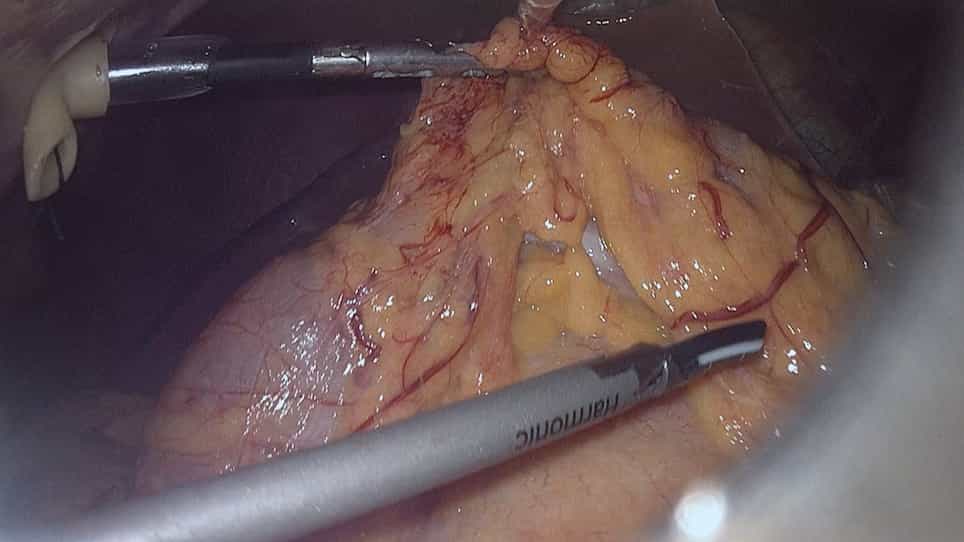
Laparoscopic Pancreatoduodenectomy for Pancreatic Cancer Using In-Situ No-Touch Isolation Technique
Published on: February 2, 2022
Right hepatic artery interruption and prostaglandin E1 in total or proximal pancreatectomy for pancreatobiliary
T Yoshida1, M Aramaki, T Matsumoto
1Department of Surgery I, Oita Medical University, 1-1 Idaigaoka, Hasama, Oita 879-5593, Japan.

Background/Aims:
Advanced hepato-biliary-pancreatic malignancy can frequently involve the hepatic artery. We evaluated the use of prostaglandin E1 in total or proximal pancreatectomy with the right hepatic artery interruption.
Methodology:
A Consecutive seven of 117 patients (6.0%) in whom the right hepatic artery was interrupted and not reconstructed were reviewed retrospectively. Four of them received prostaglandin E1 (10-20 ng/kg/min) until the fifth postoperative day, while, the remaining three did not. The effect of prostaglandin E1 was compared concerning complication and hepatic function.
Results:
The right hepatic artery was intentionally resected because of cancer invasion in five patients with biliary tract carcinoma, while, accidentally transected in two with pancreatic carcinoma. Operative deaths did not occur. The biliary leakage was identified in one patient treated without prostaglandin E1. Although a marked rise in glutamic oxaloacetic transaminase, glutamic pyruvic transaminase, and lactate dehydrogenase levels was observed, hepatic dysfunction was successfully treated conservatively in all patients. The glutamic oxaloacetic transaminase and lactate dehydrogenase values were significantly lower (P < 0.05) in patients treated with prostaglandin E1 compared with those without prostaglandin E1.
Conclusions:
The prostaglandin E1 infusion can be helpful for biliary anastomosis and hepatic function in radical hepato-biliary-pancreatic surgery with the right hepatic artery interruption.
