Related Experiment Video
Updated: Oct 5, 2026
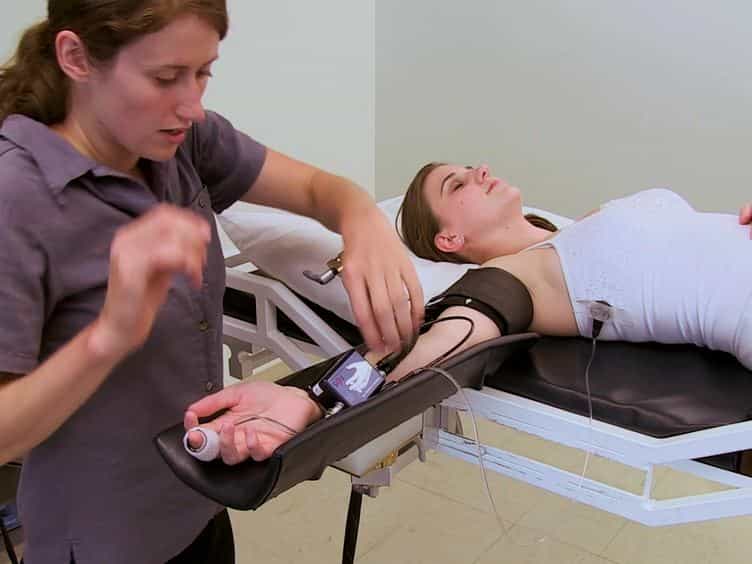
Tilt Testing with Combined Lower Body Negative Pressure: a "Gold Standard" for Measuring Orthostatic Tolerance
Published on: March 21, 2013
Diagnostic patterns and temporal trends in the evaluation of adult patients hospitalized with syncope
L A Pires1, J R Ganji, R Jarandila
1Department of Medicine, St John Hospital and Medical Center, 22101 Moross, Detroit, MI 48236, USA. luis.pires@stjohn.org

Background:
Syncope is a common clinical problem that is often difficult and expensive to diagnose. We examined diagnostic patterns and trends and use of specialty consultations in the evaluation of syncope.
Methods:
We retrospectively reviewed the medical records of consecutive adult patients hospitalized with the principal diagnosis of syncope (International Classification of Diseases, Ninth Revision, code 780.2) during 1994 and 1998 at 2 community teaching hospitals.
Results:
A total of 649 patients (57% female) with a mean (+/-SD) age of 68 +/- 15 years were identified in 1994 (n = 451) and 1998 (n = 198). Three hundred forty-one patients (53%) underwent at least 1 neurologic test, including brain computed tomographic (CT) scan (n = 283), electroencephalography (n = 253), carotid Doppler echocardiography (n = 185), and brain magnetic resonance imaging (n = 10). Only brain CT scan and electroencephalography yielded diagnoses in 5 (2%) and 6 patients (2%), respectively with history consistent with seizures or stroke. Cardiovascular tests providing the highest diagnostic yields (postural blood pressure check in 52 [30%], head-up tilt-table test in 32 [24%], and electrophysiologic study in 5 [16%]) were used in 176 (27%), 132 (20%), and 31 patients (5%), respectively. Differences in the use of some tests were noted at the participating hospitals and over time (1994 vs 1998). The total number of diagnosed cases was similar for patients undergoing evaluation by primary care physicians alone (65/103 [63%]), compared with cardiology (48/85 [56%]), neurology (29/48 [60%]), or both (81/141 [57%]). After a mean (+/-SD) length of stay of 5 +/- 4 days, 320 (49%) of 649 cases remained undiagnosed.
Conclusions:
Despite a reduction in the use of some tests (eg, brain CT scan and carotid Doppler) over time, lower-yield neurologic tests were overused and higher-yield cardiovascular tests were likely underused. The untargeted, seemingly random use of specialty evaluations did not seem to contribute to an increase in the overall number of diagnosed cases. Increased use of specific tests directed by history and results of physical examination may improve diagnostic yield and decrease the cost of evaluating syncope.
Related Concept Videos
 01:30
Dysrhythmias V: Evaluating Dysrhythmias
 01:30
Pulse rhythm
Conversely, an irregular pulse pattern is termed dysrhythmia, stemming from disruptions in cardiac muscle...
 01:30
Acute Coronary Syndrome III: Diagnostic Studies
 01:23
Assessment of the Cardiovascular System I: Subjective Data
Initial Enquiry
Ask the patient about their primary concern and thoroughly explore all reported symptoms.
Medical History
Investigate past illnesses affecting the cardiovascular system, such as angina, anemia, rheumatic fever, congenital heart disease, stroke, thrombophlebitis, dysrhythmias, varicosities
Inquire about symptoms...
 01:30
Heart Failure IV: Classification and Diagnostic Evaluation
 01:21
Peripheral Arterial Disease II: Clinical Manifestations and Diagnostic Evaluation