Related Experiment Video
Updated: May 25, 2026

Tilt Testing with Combined Lower Body Negative Pressure: a "Gold Standard" for Measuring Orthostatic Tolerance
Published on: March 21, 2013
Urinary and serum electrolyte changes in athletes during periodic and continuous hypokinetic and ambulatory
Y G Zorbas1, V J Kakurin, S D Denogratov
1Hypokinetic Physiology Laboratory, Athens, Greece.

Abstract:
Hypokinesia (HK) (diminished movement) induces significant electrolyte changes, but little is known about the effect of periodic hypokinesia (PHK) on minerals. The aim of this study was to measure the effect of PHK and continuous hypokinesia (CHK) on urinary and serum electrolytes. Studies were done during a 30-d period of prehypokinesia (HK) and during 364 d of PHK and CHK periods. Thirty male athletes aged 24.6 +/- 7.7 yr were chosen as subjects. They were equally divided into three groups: unrestricted ambulatory control subjects (UACS), continuously hypokinetic subjects (CHKS), and periodically hypokinetic subjects (PHKS). The UACS group experienced no changes in the daily activities and regular training and they were maintained under an average running distance of 11.7 km/d. The CHKS group was limited to an average walking distance of 0.7 km/d; and the PHKS group was limited to an average walking distance of 0.7 and running distance of 11.7 km/d for 5 d and 2 d/wk, respectively, for a period of 364 d. Urinary and serum phosphate (P), calcium (Ca), sodium (Na) and potassium (K), serum intact parathyroid hormone (iPTH), calcitonin (CT), plasma renin activity (PRA) and aldosterone (PA) levels, food and water intakes, and physical characteristics were measured. Urinary P, Ca, Na, and K loss, serum Ca, P, Na, and K, and PRA and PA values increased significantly (p < or = 0.01), whereas serum iPTH and CT levels decreased significantly (p < or = 0.01) in the PHKS and CHKS groups when compared with the UACS group. However, significant (p < or = 0.01) differences were observed between PHKS and CHKS groups regarding urinary and serum electrolytes, serum and plasma hormones. Food and water intakes, body weight, body fat, and peak oxygen uptake decreased significantly (p < or = 0.01) in the CHKS group when compared with PHKS and UACS groups. Food and fluid intakes, body fat, and body weight increased significantly (p < or = 0.01), whereas peak oxygen uptake remained significantly (p < or = 0.01) higher in the PHKS group when compared with the CHKS group. Serum and urinary minerals, serum hormones, food and fluid intakes, and physical characteristics did not change significantly (p > 0.01) in the UACS group when compared with their baseline control values. It was shown that both PHK and CHK induce significant serum and urinary electrolyte changes. However, urinary and serum electrolyte changes were significantly (p < or = 0.01) greater during PHK than CHK. It was concluded that the greater the stability of muscular activity, the smaller the serum and urinary electrolyte changes during prolonged HK.
More Related Videos
 06:52
An Inertial Measurement Unit Based Method to Estimate Hip and Knee Joint Kinematics in Team Sport Athletes on the Field
Published on: May 26, 2020
 10:21
Evaluation of Hydration Status by Bioelectrical Impedance Vector Analysis in Patients with Ischemic Heart Disease Undergoing Exercise Stress Test
Published on: September 22, 2023
Related Concept Videos
 01:24
Renal Tubule and Collecting Duct
Proximal Convoluted Tubule (PCT):
The PCT is the initial segment of the renal tubule, extending from the Bowman's capsule that encloses the glomerulus. Its convoluted structure and microvilli-lined cells increase the surface area for reabsorption. The PCT reabsorbs glucose, amino acids, sodium, and water from the filtrate, ensuring essential...
 01:24
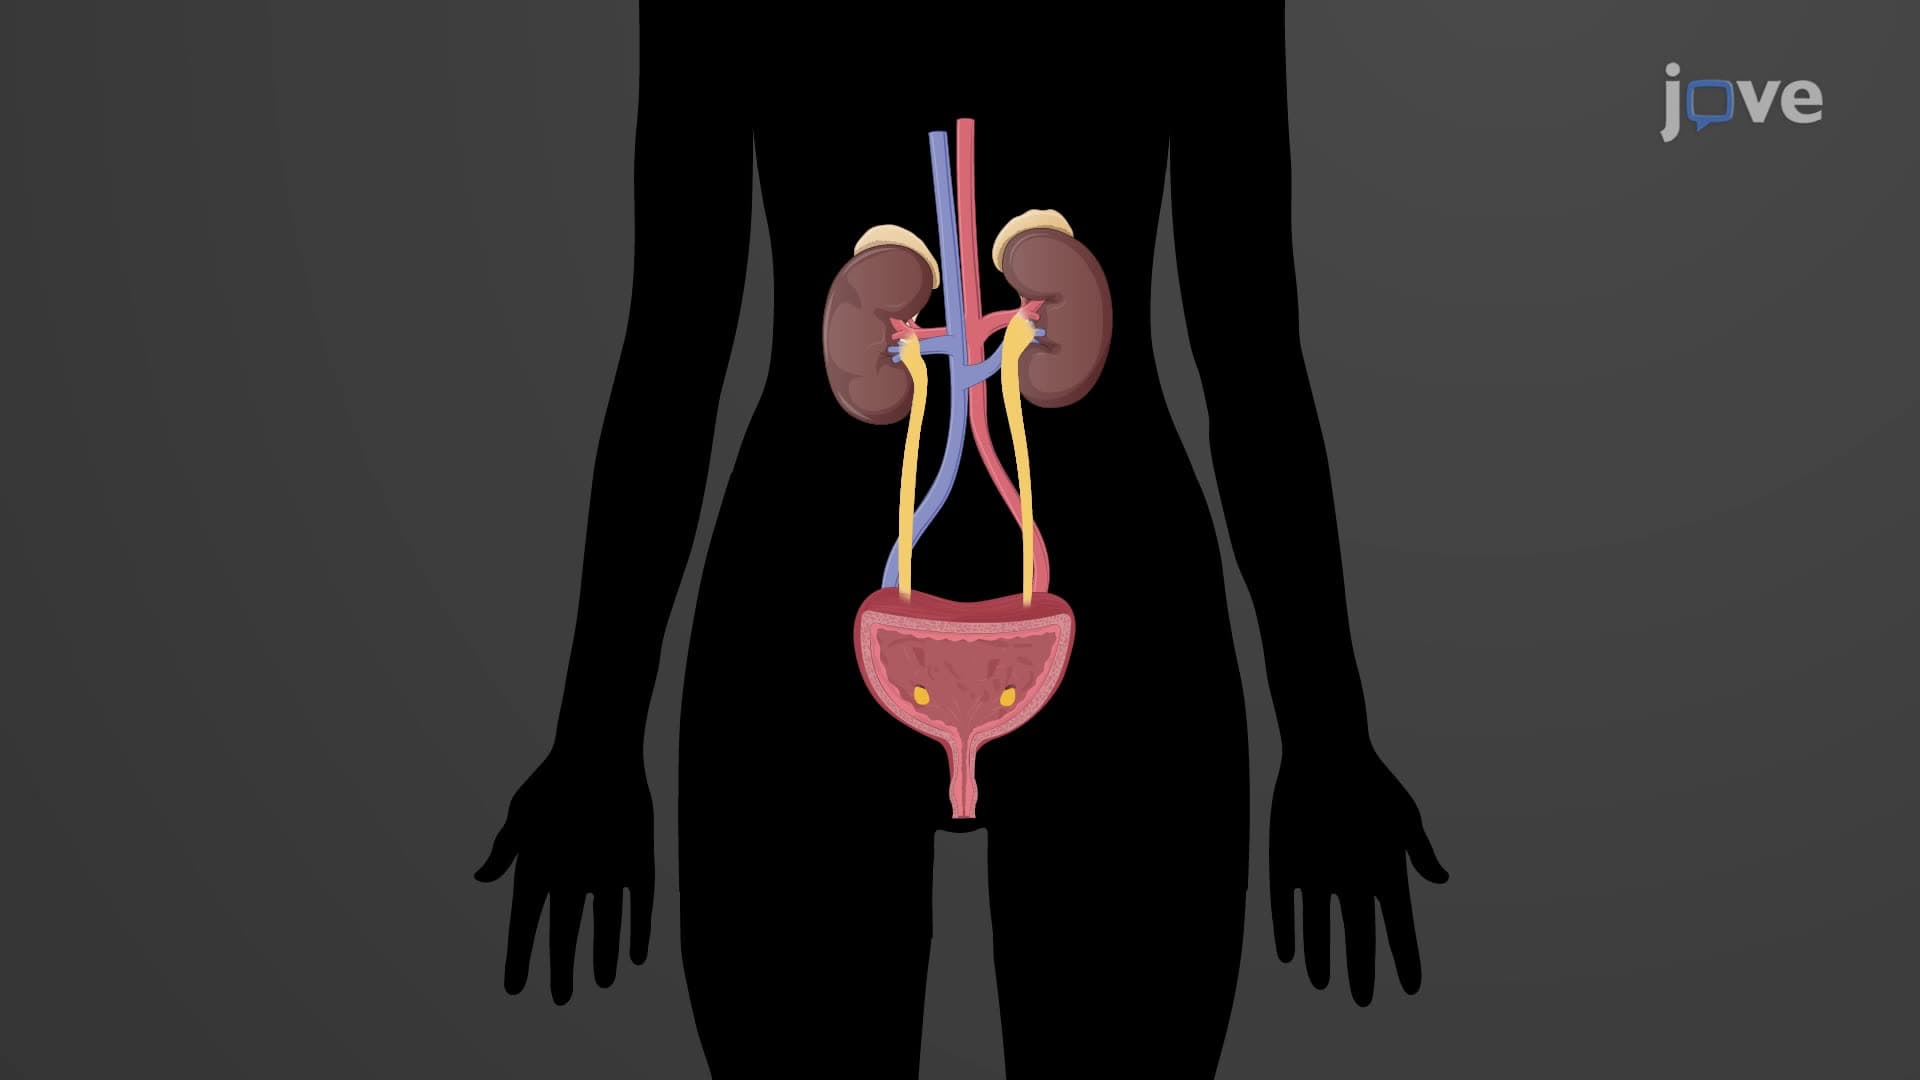
Physiology of Urine Formation
Glomerular Filtration
The first stage in urine formation is glomerular filtration. Each kidney contains approximately 1 million nephrons, the functional units of filtration, with a...
 01:25
Regulation of Water Intake
 01:20
Physiology of the Genitourinary System III: Urine Concentration and Dilution
 01:29
Acute Kidney Injury III: Clinical Manifestations
 01:22
Acute Kidney Injury VI: Nursing Management