
Pulmonary atresia with ventricular septal defect, extremely hypoplastic pulmonary arteries, major aorto-pulmonary
D Metras1, P Chetaille, B Kreitmann
1Cardio-thoracic Unit, Children's Hospital La Timone, Marseille, France. dmetras@ap-hm.fr

Objective:
Among 63 patients with pulmonary atresia and ventricular septal defect (VSD), 10 patients with extreme hypoplasia of the pulmonary arteries (PA) (mean Nakata index 20.6 mm(2)/m(2)), but with confluent arteries and a diminutive main PA, and major aorto-pulmonary collaterals (MAPCAS), have been submitted to a 'rehabilitation' of the PA with several stages: (i) connection between RV and PAs, (ii) interventional catheterizations, (iii) complete correction with or without unifocalisation. We report here the results of this approach.
Methods:
The RV-PA connection was direct (nine cases) or with an homograft conduit (one case), done under normothermic cardiopulmonary by-pass in patients aged 4.9 months (range 0.1-18 months). Subsequently, six underwent interventional catheterizations (dilations and stents in the PA, MAPCAS occlusion by coils). Complete correction was done in seven patients (mean age 30 months, range 8-49). One patient is awaiting correction.
Results:
One patient died after the first stage. All patients having had the third stage had a satisfactory development of the PA, had a complete closure of the VSD and a satisfactory reconstruction of the PA bifurcation. There was one death of severe pulmonary infection 6 months after repair. All other patients have been followed by catheterization and/or echocardiograms. With a follow-up of 83+/-65 months, all patients are improved, 50% have no cardiac medications, none has residual shunt, RV/LV pressure ratio is 0.6 (range 0.3-1).
Conclusions:
The strategy of 'rehabilitation' of PA allowing: (i) antegrade flow in the PA, (ii) interventional catheterizations, (iii) growth of the PA with possible angiogenesis, (iv) complete correction, is a logical approach to be undertaken in the young patient and is a valid alternative to strategies relying more on MAPCAS for pulmonary vascular supply. The therapeutic sequences depend upon the individual anatomy.

Related Concept Videos
 01:14
Fetal Circulation
Two umbilical arteries transport blood from the fetus to the placenta. At the placenta, the blood absorbs oxygen and nutrients while simultaneously eliminating waste products. This oxygen-enriched and nutrient-rich blood then returns to the fetus through one...
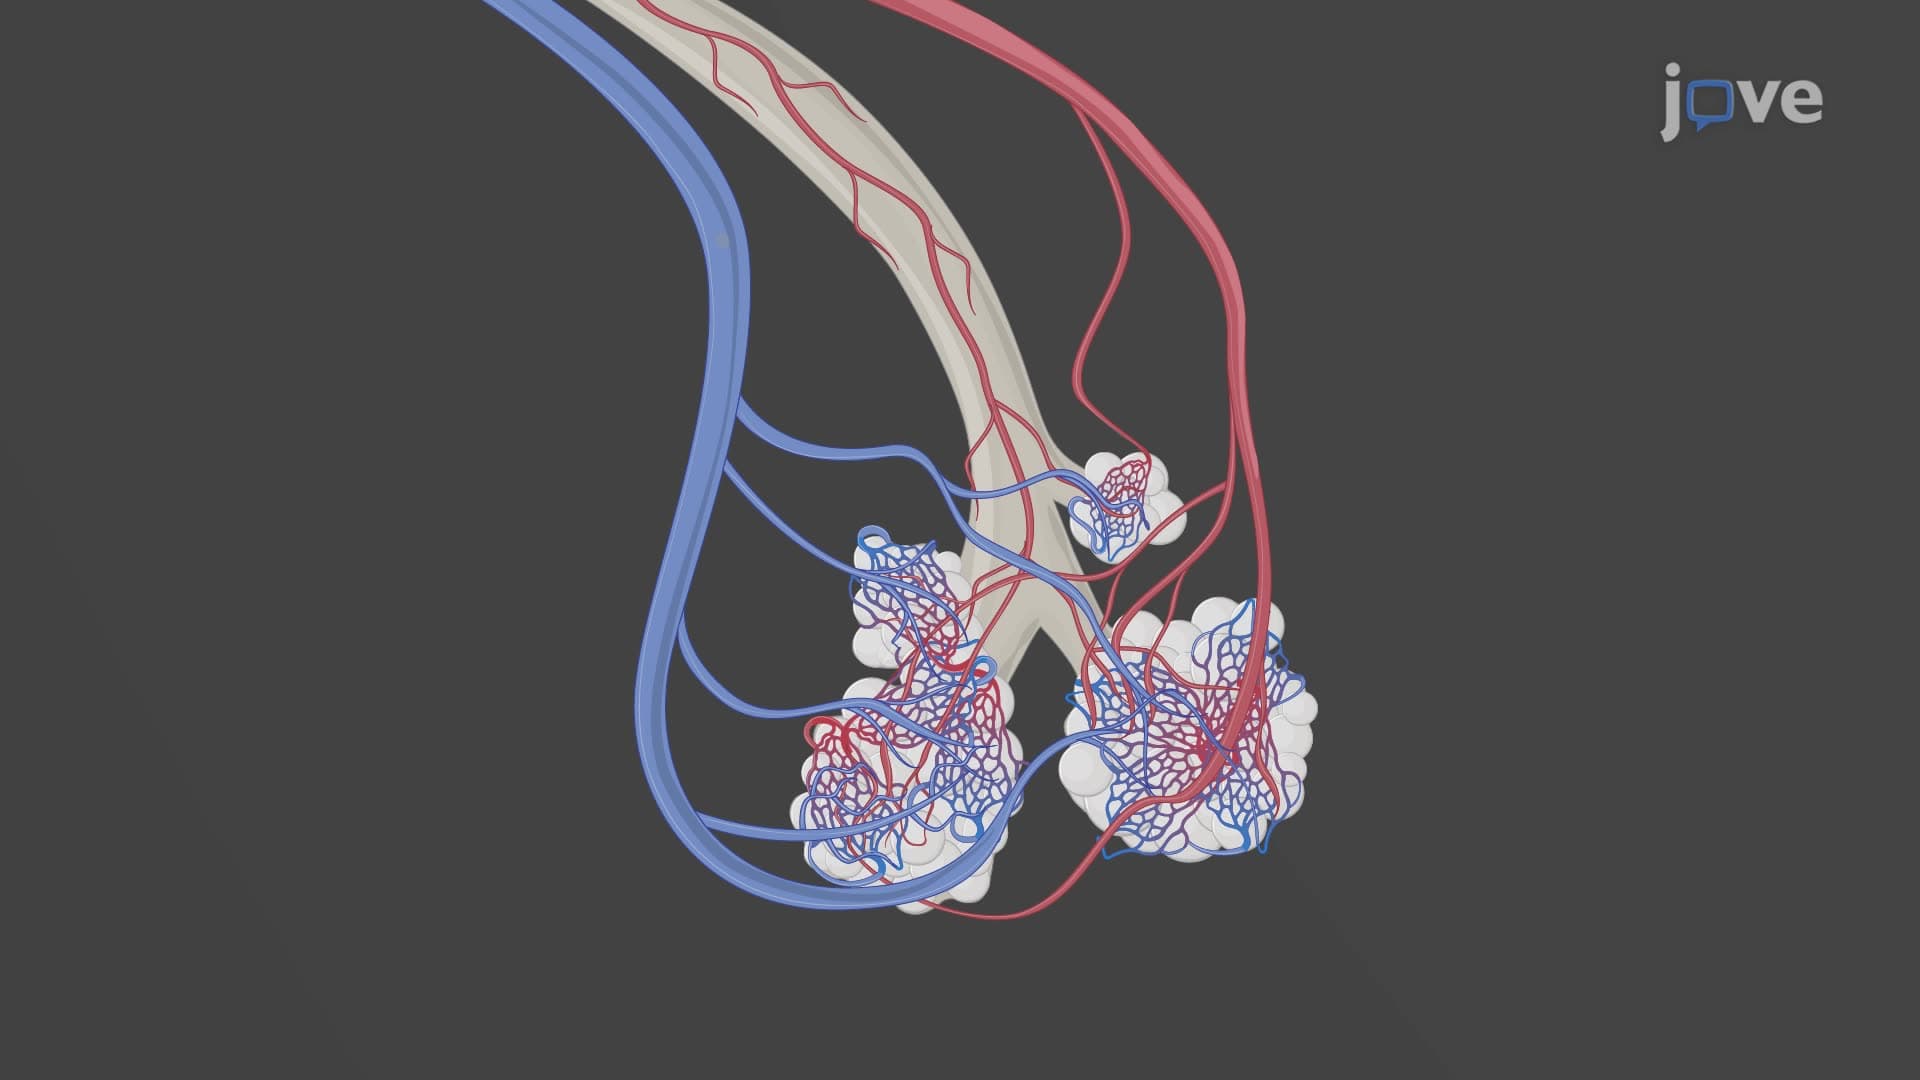 01:19
Overview of Pulmonary Circulation
The process begins with the right ventricle of the heart pumping deoxygenated blood into the pulmonary trunk. This large vessel extends about 5 centimeters before splitting into the left and right pulmonary arteries. These arteries...
 01:30
Pulmonary Hypertension: Classification and Pathogenesis
There are various classifications for PH, each relating to different underlying causes and also...
 01:15
Thoracic Aorta
 01:10
Atelectasis II: Pathophysiology
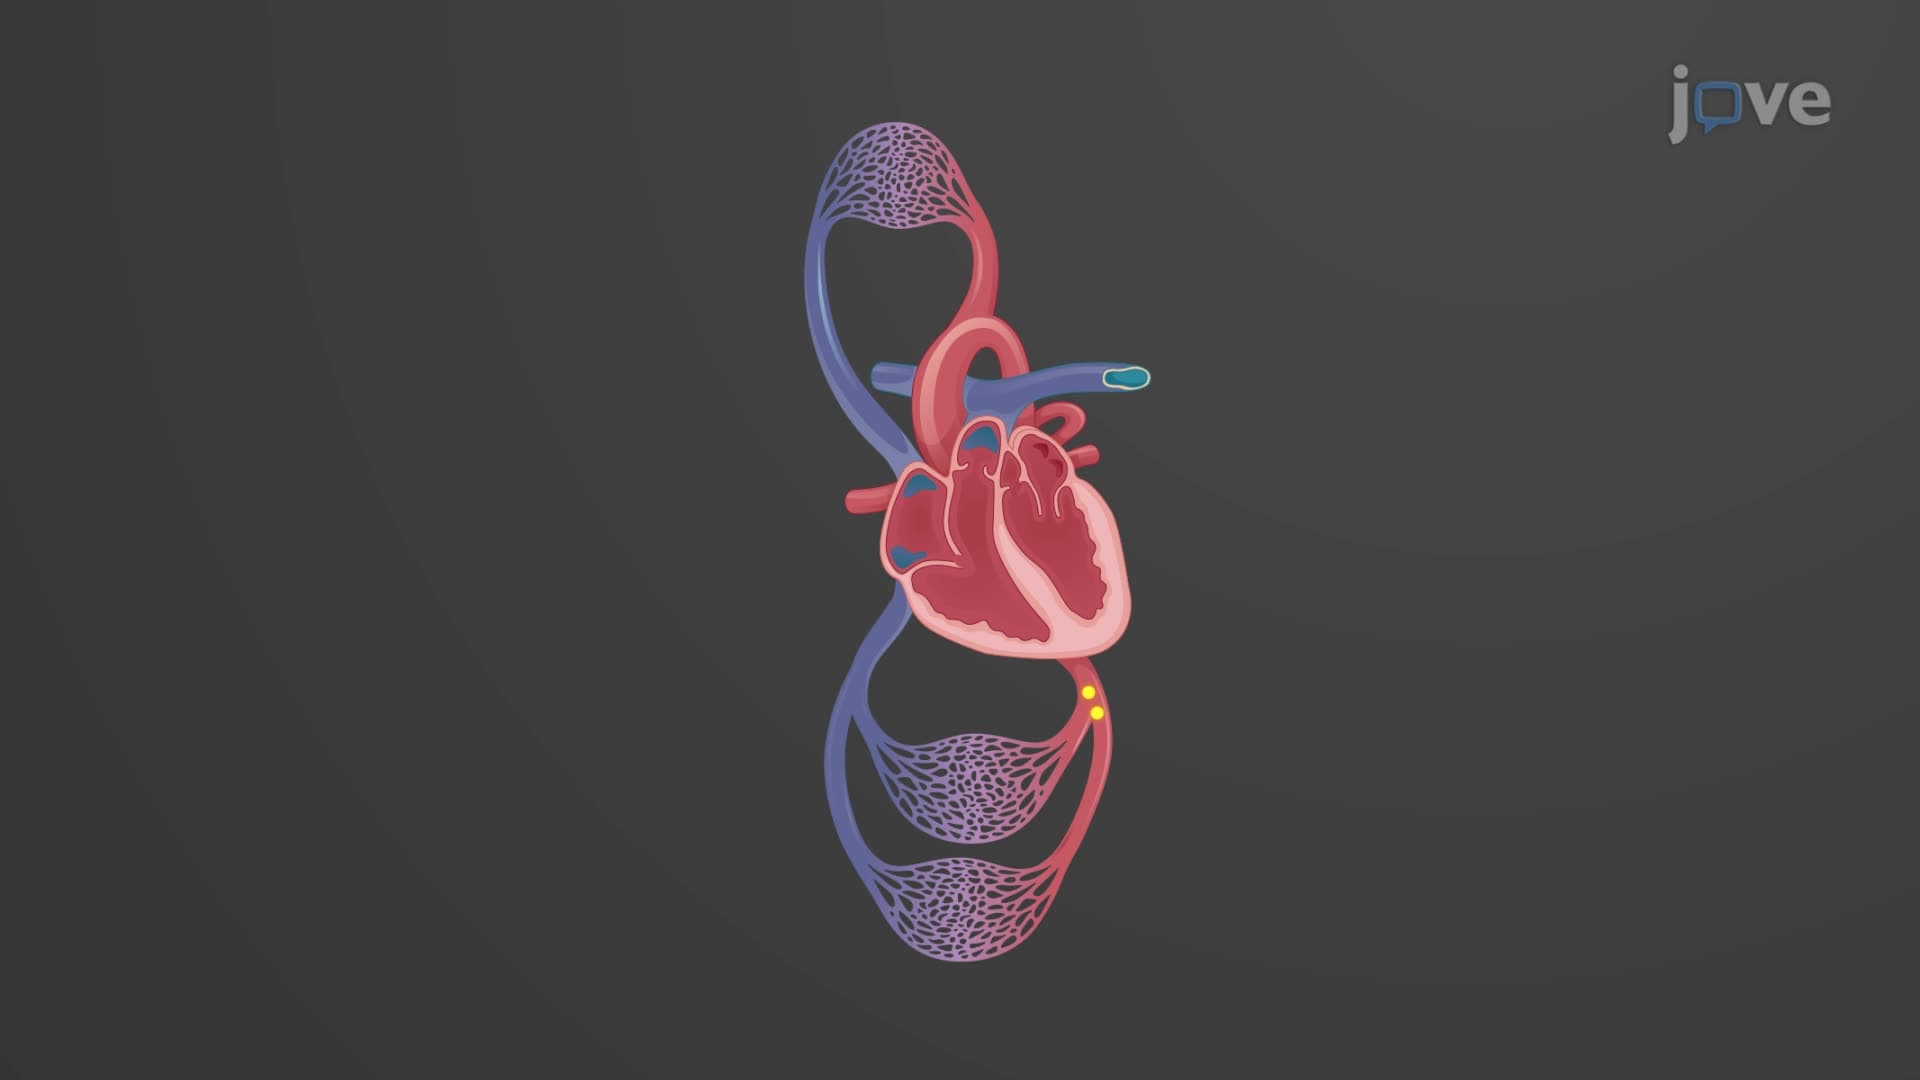 01:15
Overview of Systemic and Pulmonary Circulation
The oxygenated blood is sent...