Related Experiment Video
Updated: Oct 4, 2026

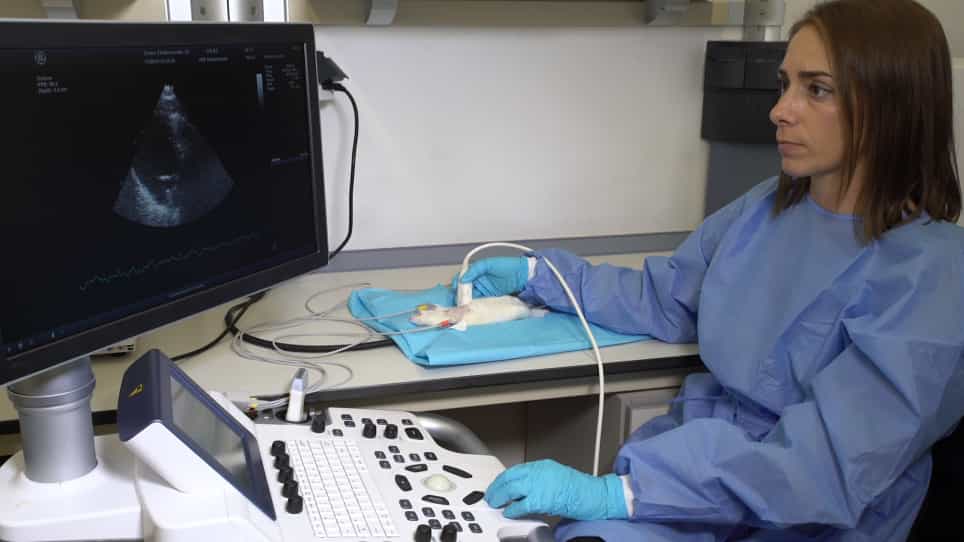
Pulsed Wave Doppler Assessment of Diastolic Dysfunction in the ZSF-1 Rat Model of Pulmonary Hypertension Due to Left Heart Disease
Published on: May 22, 2026
Effect of regression of left ventricular hypertrophy from systemic hypertension on systolic function assessed by
M Zabalgoitia1, S N Rahman, W E Haley
1Department of Medicine/Division of Cardiology, The University of Texas Health Science Center at San Antonio, San Antonio, Texas 78229-3900, USA. Zabalgoitia@uthscsa.edu

Insights
Midwall shortening, a key indicator of heart function in hypertensive patients with left ventricular hypertrophy, improved with treatment. This suggests midwall shortening is a sensitive measure for identifying high-risk individuals who may benefit from aggressive antihypertensive therapy.
Area of Science:
- Cardiology
- Hypertension Research
- Echocardiography
Background:
- Depressed midwall shortening predicts cardiovascular events in hypertensive patients with left ventricular (LV) hypertrophy, even with normal endocardial function.
- The impact of LV mass changes on midwall shortening in hypertension remains unclear.
Observation:
- A prospective study of 508 hypertensive patients (Hypertension Optimal Treatment study) using serial echocardiography.
- Patients received antihypertensive treatment to target diastolic blood pressure.
- Measurements included body mass index, blood pressure, LV mass index, endocardial fractional shortening, and midwall shortening.
Findings:
- Despite unchanged body mass index, significant reductions in systolic and diastolic blood pressure and LV mass index were observed.
- Endocardial fractional shortening remained unchanged.
- Midwall shortening showed significant improvement over the study period.
Implications:
- Midwall shortening is a more sensitive index of systolic function in pressure-overload hypertrophy.
- It can identify high-risk hypertensive patients who may benefit from more aggressive treatment.
- The observed disparity suggests impaired myofibril function in hypertension-induced LV hypertrophy.
Abstract:
Depressed midwall shortening has been shown to be an independent predictor of cardiovascular morbid events in hypertensive patients with left ventricular (LV) hypertrophy despite normal endocardial fractional shortening. The effects of LV mass changes in hypertensive patients on midwall shortening are unclear. To determine the impact of LV hypertrophy regression on LV systolic function assessed at the endocardium and the midwall level, 508 patients (58% men, 57% Caucasians, mean age 60 +/- 7 years) participating in the Hypertension Optimal Treatment study were prospectively studied by serial echocardiography at baseline, year 1, year 2, and at the end of the study. The Hypertension Optimal Treatment study was designed to challenge the existence of the J-curve phenomenon in hypertension. This study enrolled men and women between 50 and 80 years of age with mild to moderate hypertension. Patients were treated with a regimen based on felodipine with the addition of other antihypertensive drug classes as needed to reduce the diastolic blood pressure to a predefined target of < or =80, < or =85, or < or =90 mm Hg. From baseline to year 1, year 2, and end of the study, body mass index was unchanged (30.4, 30.1, 30.2, and 30.5 kg/m(2)); however, diastolic blood pressure was significantly reduced (99, 83, 80, and 80 mm Hg, p <0.0001), as was systolic blood pressure (161, 139, 137, and 134 mm Hg, p <0.0001) and LV mass index (117, 119, 107, and 106 g/m(2), p <0.0001). Over the same period of observation the endocardial fractional shortening did not change significantly (40%, 42%, 43%, and 44%); however, shortening at the midwall level showed improvement (20%, 21%, 22%, and 30%, p <0.001). In conclusion, midwall shortening is a more sensitive index of systolic function in subjects with pressure-overload hypertrophy, and it identifies high-risk patients who may benefit from a more aggressive antihypertensive program. The disparity between midwall and endocardial shortening suggests reduced myofibril function in patients with hypertension-induced hypertrophy.
Related Concept Videos
 01:20
Mitral Regurgitation I: Introduction
 01:29
Heart Failure II: Pathophysiology
 01:22
Mitral Stenosis I: Introduction
 01:29
Cardiomyopathy III: Hypertrophic Cardiomyopathy