Related Experiment Video
Updated: Oct 4, 2026

08:45
Echocardiographic Assessment Using Subxiphoid-Only Examination for Hypotensive Patients
Published on: April 18, 2025
Clinical prediction of fluid responsiveness in acute circulatory failure related to sepsis
Intensive Care Medicine
|September 6, 2001

Abstract
No abstract available in PubMed .
Related Concept Videos
 01:29
Heart Failure II: Pathophysiology
Systolic Heart Failure and Compensatory MechanismsSystolic heart failure (also termed HFrEF, Heart Failure with Reduced Ejection Fraction) is the most prevalent type of heart filure. It results in a decreased volume of blood being pumped from the ventricle. The aortic arch and carotid sinuses have baroreceptors that detect reduced blood pressure, triggering the sympathetic nervous system (SNS) to release epinephrine and norepinephrine. Initially, this response aims to boost heart rate and...
 01:22
Acute Kidney Injury VI: Nursing Management
Acute Kidney Injury (AKI) results in an inability to maintain fluid, electrolyte, and acid-base balance. Effective nursing management is critical in improving patient outcomes and includes comprehensive patient assessment and targeted interventions.Comprehensive Patient AssessmentA detailed history collection is essential, focusing on any recent infections, nephrotoxic medication use, or chronic conditions such as hypertension and diabetes that may contribute to AKI. During the physical...
 01:30
Heart Failure VII: Nursing Interventions
The first step in nursing management of a patient with heart failure involves thoroughly assessing the patient's medical history.Subjective Data: Obtain the patient's medical history of coronary artery disease, hypertension, myocardial infarction, and symptoms like dyspnea, orthopnea, and paroxysmal nocturnal dyspnea.Objective Data: Conduct a physical examination to identify findings such as jugular vein distention, pulmonary crackles, tachycardia, murmurs, peripheral edema, and vital signs,...
 01:29
Acute Respiratory Failure-V
The treatment for acute respiratory failure varies based on factors like the underlying cause, overall health, and severity. A collaborative healthcare team is essential for early detection, often through arterial blood gas analysis. Identifying the cause is the primary goal, with treatment strategies adjusted for ventilation/perfusion (V/Q) mismatch, shunting, or diffusion impairment.
Ensure that patients are monitored continuously for their response to therapy, including changes in...
Ensure that patients are monitored continuously for their response to therapy, including changes in...
 01:29
Acute Kidney Injury III: Clinical Manifestations
Acute Kidney Injury (AKI) progresses through distinct clinical phases: the oliguric, diuretic, and recovery phases, each marked by unique manifestations and challenges.Oliguric Phase:The oliguric phase is the initial stage of AKI, typically lasting 10 to 14 days. This phase is marked by a significant reduction in urine output, usually less than 400 mL per day, indicating decreased kidney function. Fluid retention is a prominent feature, leading to symptoms such as edema, hypertension, and...
 01:18
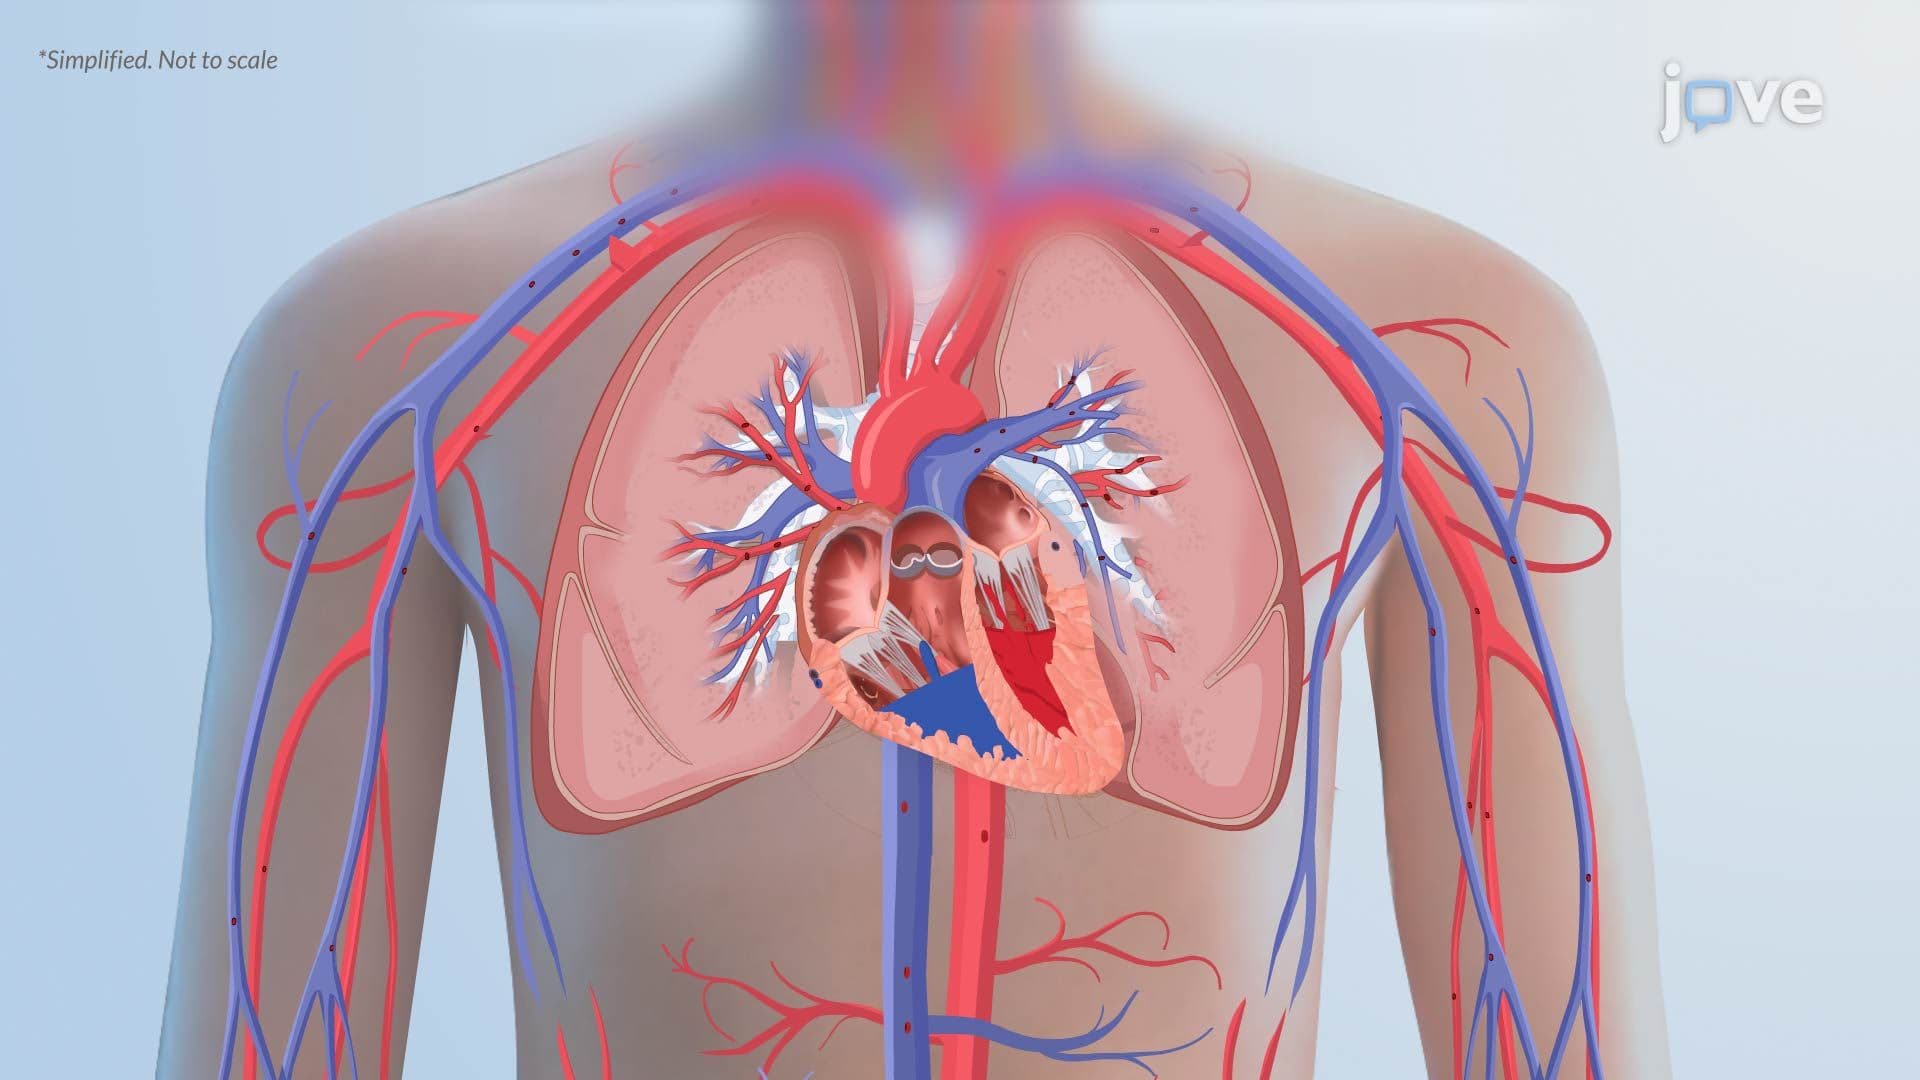
Pulmonary Edema II: Pathophysiology
Pulmonary edema is the accumulation of fluid in the interstitial and alveolar spaces of the lungs, impairing gas exchange and oxygen delivery. It may be cardiogenic or noncardiogenic, but both reduce oxygenation and lung compliance.Cardiogenic Pulmonary EdemaCardiogenic edema results from increased hydrostatic pressure in pulmonary capillaries, usually due to left ventricular dysfunction from myocardial infarction, heart failure, or valvular disease. Ineffective cardiac pumping causes blood to...